



To evaluate and compare the manifestations of IgG4-RD in patients≤25 years of age (pediatric, adolescents and young adults) and those≥50 years of age.
Materials and methodsA retrospective descriptive study of 64 patients diagnosed with IgG4-RD based on the Umehara 2011/2020 criteria and the ACR/EULAR 2019 classification criteria, covering the period from 2014 to 2023. The medical records of these two age groups were reviewed.
ResultsOf the 64 patients, 7 were ≤25 years old (11%) and 35 were ≥50 years old (54.7%). Among patients≤25 years old, 6 were female, with a mean age at consultation of 21.3 years (± 5.06). Five (71%) had single-organ involvement, while two presented with multi-organ involvement. In the ≥50 years group, females also predominated (57%), with a mean age at consultation of 60 years (± 7.4) and more constitutional symptoms were observed, multi-organ involvement (p=0.009), asthenia (p=0.047), lymph nodes (p=0.047), submandibular gland involvement (p=0.009), lung involvement (p=0.013) and parotidomegaly (p=0.097). Ocular involvement was more frequent in those under 25 years of age; however, in those over 50 years of age, this involvement was mostly bilateral (p=0.011). There were no statistically significant differences in laboratory variables between both groups. There was a predominance of lymphoplasmacytic infiltrate in the majority of the biopsies performed. In cases of ocular involvement, histopathological analysis revealed lymphoplasmacytic infiltrate with no differences in the presence of storiform fibrosis, obliterative phlebitis, or eosinophilic infiltrate. However, the latter was more frequent in older patients.
ConclusionReviewing the literature and describing our data on IgG4-RD in children is crucial, as pediatric physicians often overlook this condition. This fact, as in adult cases, could help prevent unnecessary surgeries and irreversible organ damage.
Evaluar y comparar las manifestaciones de la ER-IgG4 en los pacientes ≤25 años (pediátrica, adolescentes y adultos jóvenes), y aquellos con ≥50 años.
Materiales y métodosEstudio retrospectivo descriptivo de 64 pacientes con ER-IgG4 con criterios Umehara 2011/2020 y ACR/EULAR 2019, desde 2014 a 2023.
ResultadosDe 64 pacientes, 7 tenían ≤25 años (11%) y 35 ≥50 años (54,7%). De los pacientes ≤25 años, 6 resultaron mujeres, edad de consulta de 21,3 años (±5,06). Cinco (71%) presentaron compromiso monorgánico y 2, compromiso multiorgánico. En los ≥50 años, predominó el sexo femenino (57%), edad de consulta de 60 años (±7,4), observándose más síntomas constitucionales, compromiso multiorgánico (p=0,009), astenia (p=0,047), ganglios linfáticos (p=0,047), glándula submaxilar (p=0,009), pulmón (p=0,013) y parotidomegalia (p=0,097). El compromiso ocular resultó más frecuente en los menores de 25 años, sin embargo, en los mayores de 50 años, este compromiso fue mayormente bilateral (p=0,011). No hubo diferencias estadísticamente significativas en las variables de laboratorio en ambos grupos. Existió un predominó de infiltrado linfoplasmocitario en todas las biopsias realizadas. La anatomía patológica del compromiso ocular, mostró presencia de infiltrado linfoplasmocitario, sin diferencias en la fibrosis estoriforme, flebitis obliterativa e infiltrado de eosinófilos, si bien este último fue mayor en los pacientes de edad avanzada.
ConclusiónEs importante revisar la literatura y describir nuestros datos de la ER-IgG4 en ≤25 años, dado que esta enfermedad no es muy tenida en cuenta por los médicos pediatras. Este hecho, al igual que en los adultos, podría evitar cirugías innecesarias y daño orgánico irreversible.
IgG4-related disease (IgG4-RD) is a clinical entity characterized by elevated serum IgG4 concentrations and swelling or tissue infiltration by IgG4-positive plasma cells. This condition can manifest in a certain proportion of patients with a wide range of diseases, including Mikulicz's disease, autoimmune pancreatitis, hypophysitis, Riedel's thyroiditis, interstitial pneumonitis, interstitial nephritis, prostatitis, lymphadenopathy, retroperitoneal fibrosis, inflammatory aortic aneurysm and inflammatory pseudotumors. It primarily affects middle-aged to elderly men.1
Several studies have been published on the differences in this disease between elderly patients and children, particularly in terms of gender distribution, the number of affected organs and the types of organs involved—internal organs in adults versus superficial organs in children.2–6
This study aimed to evaluate these differences in our population of 64 patients with IgG4-RD, analyzing the characteristics of the disease in children, adolescents and young adults compared to older patients.
Materials and methodsA retrospective descriptive study was conducted on a cohort of 64 patients, 49 of whom belonged to the Rheumatology Service of Hospital J.M. Cullen, Santa Fe, and 15 to the Rheumatology Service of Hospital Central de Reconquista, with a diagnosis of IgG4-RD from 2014 to December 2023. We defined pediatric, adolescent and young adult IgG4-RD as encompassing all patients≤25 years of age, based on two publications that use this age cut-off. This allowed us to compare our patients with those in the published series and with patients who had IgG4-RD and were ≥50 years of age.5,6
All patients were assessed using the Umehara 2011 comprehensive diagnostic criteria and/or its 2020 revision (definite, probable, and possible), as well as the ACR/EULAR 2019 classification criteria, from 2014 to December 2023.7–9 Data that were analyzed include sex, age at diagnosis, history of asthma, clinical manifestations, laboratory results, histopathological and imaging findings (CT, MRI with contrast, PET/CT), treatments, and outcomes.
Laboratory tests evaluated included: haemogram, eosinophils, erythrocyte sedimentation rate (ESR), quantitative C-reactive protein (CRP), serum concentrations of IgE, IgA, IgM, and IgG along with their subtypes, RF, ANA (HEp-2), C3, and C4. Cut-off points: anemia (Hb<12g/l in women and <13g/l in men), leukopenia (WBC<4000/μL), lymphopenia (lymphocytes<1500/μL), eosinophilia (eosinophils>500/μL), IgG4≥135mg/dl. Serum IgG4≥2.8g/l and IgG2≥5.3g/l were considered significant in assessing their relationship with organ involvement,7,8 ANA (Hep-2) positive (≥1/160), RF>14IU/ml, CRP>5mg/l, and for ESR, the upper limit was based on age and sex: age in years/2 for males and (age in years+10)/2 for females.10–12 No genetic studies were performed in patients≤25 years of age.
Biopsies were performed using either incisional or excisional techniques. The histopathological samples were not stained for elastin. Immunohistochemistry was carried out, with the analysis considering the number of IgG4-positive cells per HPF≥10 and the IgG4/IgG ratio≥40%.
Statistical methodData were analyzed using SPSS Statistics 19 software. Categorical variables were presented as frequencies and percentages, while continuous variables were presented as means with their standard deviation (SD) if normally distributed, and as medians with interquartile ranges if not. Comparisons of proportions were performed using the chi-square test or Fisher's exact test, and comparisons of means and medians were conducted using the T-test or non-parametric tests. Statistical significance was defined as a p-value of ≤0.05.
Participants gave informed consent for data collection and publication. The study was approved by the Ethics Committee of the institution.
ResultsOut of our series of 64 patients, 7 (11%) were 25 years old or younger, and 35 (54.7%) were 50 years old or older.
Of the 7 patients, six were female, with a mean age at consultation of 21.3 years (± 5.06), a mean age at symptom onset of 19 years (± 6.5, range 8–25) and a disease follow-up time of 28.5 months (3.5–91.8). Five patients (71%) had single-organ involvement: 2 with unilateral ocular involvement, 2 with pancreatic–hepatic–biliary involvement and 1 with adenopathy. The patients with multi-organ involvement presented unilateral ocular involvement, one of them was associated with mastoiditis and central nervous system involvement (pachymeningitis) and the other with kidney involvement. Five patients underwent audiometry tests, with three showing sensorineural hypoacusis.
Regarding laboratory data, 2 patients had elevated ESR and 3 had elevated CRP levels. Additionally, 3 patients had increased serum levels of IgE, IgG1and IgG4. Patients with multi-organ involvement showed a statistical trend toward serum IgG4 values≥2.8g/l, consistent with previous findings. None of the patients≤25 years presented a decrease in C3 levels.
All patients underwent biopsies in various organs. Anatomopathological findings revealed lymphoplasmacytic infiltrate in 6 out of 7 patients (87.5%), storiform fibrosis in 2 out of 7 (28.6%), obliterative phlebitis in 2 out of 7 (28.6%) and eosinophilic infiltrate in 3 out of 7 (42.9%). Immunohistochemical studies were performed on six patients; five had IgG4 cells≥10 per high-power field, while two patients lacked data. The IgG4/IgG ratio was >40% in 3 patients and <40% in 1 patient, with 3 patients having no data. All patients received glucocorticoid therapy, 5 of whom also received methotrexate and 4 were treated with rituximab.
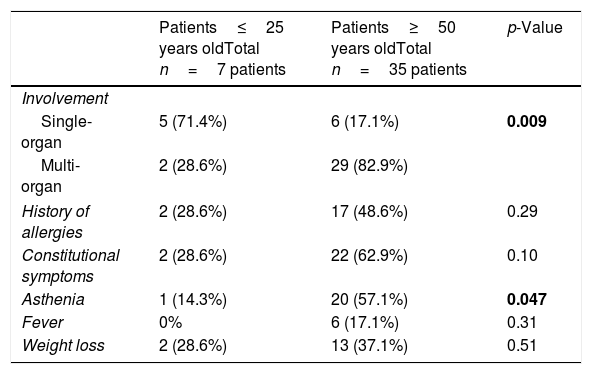
The group of patients aged≥50 years was predominantly female (57%), with a mean age of 60 years (± 7.4). A comparative analysis between patients≤25 years of age and those ≥50 years of age revealed that the younger group mostly had single-organ involvement (71.4%). In contrast, the older group exhibited a higher prevalence of constitutional symptoms (63% vs. 27%) and, significantly, multi-organ involvement (82.9%, p=0.009) and asthenia (57.1%, p=0.047) (Table 1).
Comparative results of conditions between patients≤25 years old and those≥50 years old (total n=42 patients).
| Patients≤25 years oldTotal n=7 patients | Patients≥50 years oldTotal n=35 patients | p-Value | |
|---|---|---|---|
| Involvement | |||
| Single-organ | 5 (71.4%) | 6 (17.1%) | 0.009 |
| Multi-organ | 2 (28.6%) | 29 (82.9%) | |
| History of allergies | 2 (28.6%) | 17 (48.6%) | 0.29 |
| Constitutional symptoms | 2 (28.6%) | 22 (62.9%) | 0.10 |
| Asthenia | 1 (14.3%) | 20 (57.1%) | 0.047 |
| Fever | 0% | 6 (17.1%) | 0.31 |
| Weight loss | 2 (28.6%) | 13 (37.1%) | 0.51 |
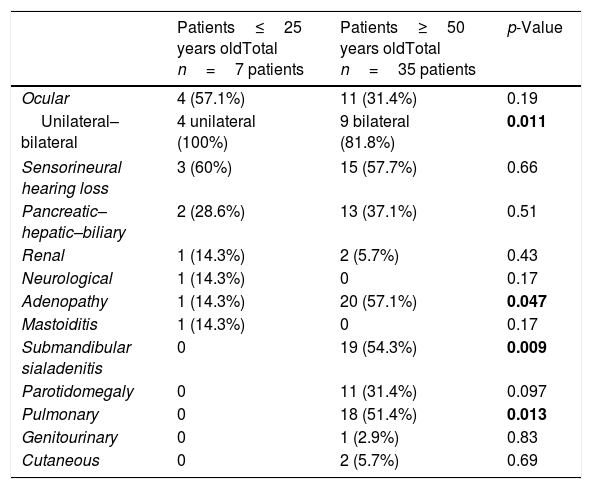
In terms of organ involvement, patients≥50 years old showed statistically significant differences, with greater involvement of lymph nodes (57.1%, p=0.047), submaxillary glands (54.3%, p=0.009), lungs (51.4%, p=0.013) and a statistical trend for parotidomegaly (31.4%, p=0.097). Ocular involvement was more frequent among those under 25 years of age, but without statistical significance (57.1% vs. 31.4%, p=0.19). However, in patients over 50 years old, ocular involvement was predominantly bilateral and statistically significant (p=0.011), with no differences noted regarding the site of involvement (muscles, sclera, glands, conjunctivae, or eyelids) (Table 2).
Comparative results of conditions between patients≤25 years old and those≥50 years old (total n=42 patients).
| Patients≤25 years oldTotal n=7 patients | Patients≥50 years oldTotal n=35 patients | p-Value | |
|---|---|---|---|
| Ocular | 4 (57.1%) | 11 (31.4%) | 0.19 |
| Unilateral–bilateral | 4 unilateral (100%) | 9 bilateral (81.8%) | 0.011 |
| Sensorineural hearing loss | 3 (60%) | 15 (57.7%) | 0.66 |
| Pancreatic–hepatic–biliary | 2 (28.6%) | 13 (37.1%) | 0.51 |
| Renal | 1 (14.3%) | 2 (5.7%) | 0.43 |
| Neurological | 1 (14.3%) | 0 | 0.17 |
| Adenopathy | 1 (14.3%) | 20 (57.1%) | 0.047 |
| Mastoiditis | 1 (14.3%) | 0 | 0.17 |
| Submandibular sialadenitis | 0 | 19 (54.3%) | 0.009 |
| Parotidomegaly | 0 | 11 (31.4%) | 0.097 |
| Pulmonary | 0 | 18 (51.4%) | 0.013 |
| Genitourinary | 0 | 1 (2.9%) | 0.83 |
| Cutaneous | 0 | 2 (5.7%) | 0.69 |
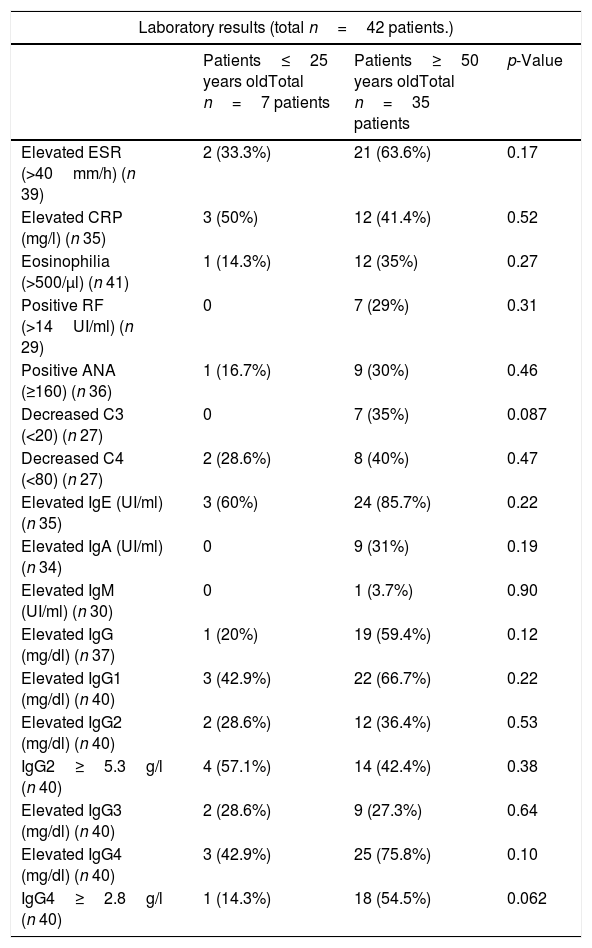
The laboratory data analyzed did not reveal statistically significant differences. However, older patients exhibited higher elevations in ESR, IgE, IgG and the IgG1 and IgG4 subtypes, with the latter showing a statistical trend (p=0.062) toward values≥2.8g/l in this group. Complement levels, particularly C3, were more frequently decreased in patients over 50 years old, also showing a statistical trend. Notably, none of the patients≤25 years showed a decrease in C3 and only 2 patients presented a decrease in C4 (Table 3).
Comparative results of laboratory results between patients≤25 years old and those≥50 years old (total n=42 patients).
| Laboratory results (total n=42 patients.) | |||
|---|---|---|---|
| Patients≤25 years oldTotal n=7 patients | Patients≥50 years oldTotal n=35 patients | p-Value | |
| Elevated ESR (>40mm/h) (n 39) | 2 (33.3%) | 21 (63.6%) | 0.17 |
| Elevated CRP (mg/l) (n 35) | 3 (50%) | 12 (41.4%) | 0.52 |
| Eosinophilia (>500/μl) (n 41) | 1 (14.3%) | 12 (35%) | 0.27 |
| Positive RF (>14UI/ml) (n 29) | 0 | 7 (29%) | 0.31 |
| Positive ANA (≥160) (n 36) | 1 (16.7%) | 9 (30%) | 0.46 |
| Decreased C3 (<20) (n 27) | 0 | 7 (35%) | 0.087 |
| Decreased C4 (<80) (n 27) | 2 (28.6%) | 8 (40%) | 0.47 |
| Elevated IgE (UI/ml) (n 35) | 3 (60%) | 24 (85.7%) | 0.22 |
| Elevated IgA (UI/ml) (n 34) | 0 | 9 (31%) | 0.19 |
| Elevated IgM (UI/ml) (n 30) | 0 | 1 (3.7%) | 0.90 |
| Elevated IgG (mg/dl) (n 37) | 1 (20%) | 19 (59.4%) | 0.12 |
| Elevated IgG1 (mg/dl) (n 40) | 3 (42.9%) | 22 (66.7%) | 0.22 |
| Elevated IgG2 (mg/dl) (n 40) | 2 (28.6%) | 12 (36.4%) | 0.53 |
| IgG2≥5.3g/l (n 40) | 4 (57.1%) | 14 (42.4%) | 0.38 |
| Elevated IgG3 (mg/dl) (n 40) | 2 (28.6%) | 9 (27.3%) | 0.64 |
| Elevated IgG4 (mg/dl) (n 40) | 3 (42.9%) | 25 (75.8%) | 0.10 |
| IgG4≥2.8g/l (n 40) | 1 (14.3%) | 18 (54.5%) | 0.062 |
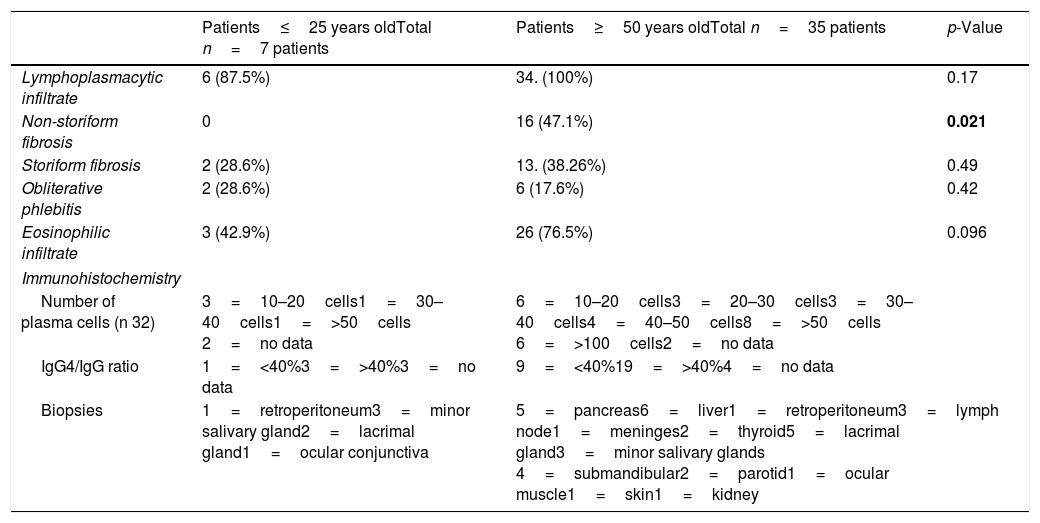
Comparing the results of the pathologic anatomy of the biopsies performed in different organs, the presence of lymphoplasmacytic infiltrate predominated in both groups. Eosinophilic infiltrate (p=0.096) and non-storiform fibrosis (p=0.021) predominated in the tissues of patients≥50 years, with the latter showing statistical significance (Table 4). Pathologic anatomy of ocular involvement in patients≤25 years (2 lacrimal glands and 1 conjunctiva) compared to patients≥50 years (5 lacrimal glands and 1 ocular muscle) showed the presence of lymphoplasmacytic infiltrate in all cases. However, there were no significant differences in stromal fibrosis or obliterative phlebitis, although eosinophilic infiltrate was higher in older patients.
Comparative results of biopsies performed between patients≤25 years old and those≥50 years old (total n=42 patients).
| Patients≤25 years oldTotal n=7 patients | Patients≥50 years oldTotal n=35 patients | p-Value | |
|---|---|---|---|
| Lymphoplasmacytic infiltrate | 6 (87.5%) | 34. (100%) | 0.17 |
| Non-storiform fibrosis | 0 | 16 (47.1%) | 0.021 |
| Storiform fibrosis | 2 (28.6%) | 13. (38.26%) | 0.49 |
| Obliterative phlebitis | 2 (28.6%) | 6 (17.6%) | 0.42 |
| Eosinophilic infiltrate | 3 (42.9%) | 26 (76.5%) | 0.096 |
| Immunohistochemistry | |||
| Number of plasma cells (n 32) | 3=10–20cells1=30–40cells1=>50cells 2=no data | 6=10–20cells3=20–30cells3=30–40cells4=40–50cells8=>50cells 6=>100cells2=no data | |
| IgG4/IgG ratio | 1=<40%3=>40%3=no data | 9=<40%19=>40%4=no data | |
| Biopsies | 1=retroperitoneum3=minor salivary gland2=lacrimal gland1=ocular conjunctiva | 5=pancreas6=liver1=retroperitoneum3=lymph node1=meninges2=thyroid5=lacrimal gland3=minor salivary glands 4=submandibular2=parotid1=ocular muscle1=skin1=kidney | |
No differences were found in the treatments administered and in the outcomes between these patient groups.
DiscussionSeveral studies have examined IgG4-RD involvement in young and pediatric patients, including case reports, systematic reviews and a few comparative analyses with older patients.2–6 It is crucial to review the existing literature and present our data on IgG4-RD in children, adolescents and young adults, as this condition is often overlooked by pediatricians. Addressing this issue, as it occurs with adult cases, could help prevent unnecessary surgeries and irreversible organ damage.
Most studies involve a small number of patients (ranging from 8 to 25), except for the systematic review by Hara et al., which includes 135 patients. Generally, these studies report a higher prevalence of the disease in women, except for the study by Lu et al., where 7 out of 10 patients were men. Notably, patients with a limited head and neck phenotype often involve younger women. Most studies indicate a predominant ocular involvement, though Lu et al. reported a predominance of Mikulicz disease and lymphadenopathy in 70% and 40% of cases, respectively. Overall, pediatric patients tend to have fewer involved organs. Serum IgG4 levels were elevated in 36–70% of cases. Histological findings most commonly include lymphoplasmacytic infiltrate and fibrosis. Treatment is generally similar to the one used for adults.2–6
As previously mentioned, Hara et al. conducted a review of 135 patients, describing their characteristics and applying both the ACR/EULAR criteria and the 2020 comprehensive diagnostic criteria.11 Among these patients, 62 were male (45.9%), 65 were female (48.1%) and sex was not reported for 8 patients. Ocular manifestations were observed in 53/135 cases (39%), with 81.5% being unilateral and 18.5% bilateral. Fever was present in 9 out of 53 patients (17%), 4 tested positive for ANCA and 1 had granulomatous vasculitis. Salivary gland involvement was less frequent in pediatric cases compared to ocular involvement, being reported in 22% of cases in this review, with 5 of these being unilateral. Viral infections, such as Epstein–Barr virus, which can cause parotitis, should be considered in these cases. Additionally, lymphadenopathy was noted in 16/34 cases (47%) exclusively in lymph nodes. Caution is advised when attributing such lymphadenopathy to IgG4-RD, as painless lymphadenopathy does not meet the comprehensive diagnostic criteria for IgG4-RD. Differential diagnoses to consider include malignant lymphoma, Castleman's disease and systemic vasculitis. Autoimmune pancreatitis (AIP) was observed in 44 cases: 5 of type 1, 12 of type 2 and 27 nonspecific cases, with type 2 being more prevalent in boys. Elevated serum IgG4 levels were found in only 19 of 39 cases of AIP. Sclerosing cholangitis, Riedel's thyroiditis and renal disease are rare in children, with low-density lesions in the renal parenchyma being typical. Central nervous system (CNS) involvement occurs in less than 2% of patients and commonly presents as hypertrophic pachymeningitis or hypophysitis, with isolated hypophysitis being described in children. While respiratory disease is very common in adults, it is rare in pediatric cases. In the younger group, rare involvement of the colon and biceps muscle was noted. Elevated serum IgG4 was observed in 73/122 patients (59.8%), but this frequency varied with the organs affected: 30 of 50 cases (60%) in ophthalmic disease, 15 of 18 cases (83.3%) with salivary gland involvement, 26 of 33 cases (78.8%) in lymphadenopathy and 16 of 39 cases (41%) in autoimmune pancreatitis. Hypocomplementemia, which is described in adults, was not reported in pediatric cases. It is important to note that a very high CRP and erythrocyte sedimentation rate in children can decrease the diagnostic likelihood of IgG4-RD.6
Of our cohort of 64 patients, only 7 (11%) were ≤25 years old, most of whom were female and had single-organ involvement. Four of the seven (57%) had unilateral ocular involvement, followed by hepato-pancreato-biliary involvement in 28.6%. One patient had renal involvement and another had pachymeningitis with mastoiditis. The otological findings in this group need further investigation, as three out of five patients who underwent audiometry exhibited sensorineural hypoacusis. Laboratory data analysis revealed that IgE and IgG2 levels≥5.3g/l were elevated in more than 50% of the patients, while serum IgG4 levels were elevated in only 3 out of 7 patients (43%). None of the patients had decreased C3 levels. Anatomopathological findings from biopsies showed lymphoplasmacytic infiltrate in 87.5%, eosinophilic infiltrate in 42.9% and storiform fibrosis and obliterative phlebitis, both present in 28.6% of cases.
Bu et al. studied patients younger than 18 years old with IgG4-RD, focusing primarily on histologic features. Histologic and immunohistochemical review for IgG4 was conducted on 20 patients over 8 years. Sixteen of these patients had few or no IgG4-positive cells, while the remaining four had a higher number of IgG4 plasma cells. Of the latter group, three had orbital involvement and all were female; the only male had soft tissue involvement of the neck. All cases exhibited a significant and dense lymphoplasmacytic infiltrate, along with perivascular non-storiform fibrosis, but without obliterative phlebitis or eosinophilic infiltrate. Three of the four patients had a histiocytic infiltrate without granuloma formation, lymphoid follicles, or germinal centers. Immunohistochemistry revealed plasma cells ranging from 60 to 110 per high-power field and an IgG4/IgG ratio between 50% and 90% in all four patients.13 These anatomopathological findings are consistent with those observed in our younger patients with ocular biopsies.
In the adult population, the frequency of ocular involvement ranges from 17% to 23%, with a higher prevalence in men. Bilateral involvement occurs in approximately 60% of cases and 70–80% of patients present with extra-ophthalmic manifestations. The lacrimal gland is commonly affected, with typical presenting symptoms including eyelid and orbital mass swelling, proptosis, pain, decreased visual acuity, diplopia and restriction of ocular mobility. Serum IgG4 levels may be normal in 30% of patients. There is a lower frequency of storiform fibrosis and obliterative phlebitis. Relapse occurs in about two-thirds of patients.14–16
As regards comparisons between adults and children, few studies in the literature specifically compare elderly patients with pediatric patients.4–6
When comparing our seven younger patients with older patients, we observed that the older group had more extensive multi-organ involvement, constitutional symptoms and significantly greater involvement of lymph nodes, submaxillary glands and lungs. Ocular involvement was more frequent in younger patients, although this difference was not statistically significant. In contrast, patients older than 50 years old had predominantly bilateral ocular involvement, which was statistically significant. We found no notable differences in laboratory data or in the pathological anatomy across different organs, where lymphoplasmacytic infiltrate was the predominant feature. However, non-storiform fibrosis showed statistical significance in the older group. Serum IgG2 levels≥5.3g/l were associated with high sensitivity and specificity for ocular involvement due to IgG4-RD compared to ocular pathology caused by other non-IgG4 diseases. In this study, more than half of the younger patients had IgG2 levels exceeding this threshold.11
Sainte Marie et al. studied 22 cases of patients under 25 years of age, including pediatric, adolescent and young adult patients. All patients met the criteria defined by the comprehensive diagnostic criteria and had an ACR/EULAR score≥20. Among the 22 cases, 12 patients (55%) were female, with a mean age of 18.4 years. The most significant involvement was observed in lymph nodes (13 patients), followed by the orbit (9 patients), pancreas (5 patients) and liver, bile duct, lung, uveitis and mastoid (3 patients each). Serum IgG4 levels were normal in 36% (8 patients) of the cases. In addition, 73% (16 patients) had involvement of more than one organ. Histologic analysis was performed in 21 patients (95%). Glucocorticoids used as a monotherapy were the most commonly prescribed treatment (68%). Seven patients (32%) had at least one ACR/EULAR exclusion criterion; however, none of them developed another disease during follow-up. These findings were compared with 87 elderly patients from the French cohort. Young patients had statistically significant differences, including a higher proportion of females, a higher incidence of fever at diagnosis, fewer organs involved and a greater need for treatment with second-line drugs. According to the authors, the strength of this study lies in its use of validated diagnostic classification criteria for IgG4-RD. Most young patients presented with clinical, biological and histological features similar to those observed in adults. Nevertheless, there was a lower frequency of involvement in retroperitoneal fibrosis, biliary tract, pancreas, aorta, salivary glands and lymph nodes.5
Karim et al., in their systematic review of the literature, describe ocular manifestations as the most frequently observed alterations in the pediatric population (44%), followed by pancreatic involvement (12%) and cholangitis and lung involvement at 8% each.2
The only study that exclusively focused on ocular involvement was conducted by Smerla et al. These authors described a case of painless swelling of the right upper eyelid, orbital involvement, and ptosis. They also reviewed the literature and identified 13 pediatric patients with ocular involvement, including 10 females and 3 males. The most common finding was unilateral inflammation or protrusion, observed in 84.6% of cases, with eyelid involvement occurring in 46.1%. Only 23% of patients had extra-ophthalmic involvement and two patients had a history of preseptal cellulitis, uveitis and retinopathy of prematurity. Elevated serum IgG4 was found in 38.5% of the patients. Imaging revealed extraocular muscle involvement in 53.8% and bone involvement in 23%. Histologically, a lymphoplasmacytic infiltrate was the predominant finding, with fibrosis present in 6/11 cases (54.5%). Storiform fibrosis was noted in only one patient and two cases exhibited obliterative phlebitis. These findings were compared with the characteristics of the adult population as described in the literature, revealing greater ophthalmic involvement in children, a distinct pattern of ocular involvement, more frequent unilateral involvement and increased involvement of extraocular muscles and orbital soft tissues. In contrast, lacrimal gland involvement and extraocular involvement were infrequent in children.17
Similar to previous studies, Hara et al. describe ocular involvement in 53 of 135 patients (39%), with 81.5% presenting unilateral compromise and a greater incidence of extraocular muscle and orbital soft tissue involvement. They also report bone, optic nerve sheath, and conjunctiva involvement. In adults, the lacrimal gland remains the most commonly affected structure.6
It is to be remarked that, when it comes to children, it is always crucial to conduct a thorough differential diagnosis and rule out other conditions, such as lymphoma, sarcoidosis, xanthogranuloma, and granulomatosis with polyangiitis, especially in cases of unilateral involvement.2,3,6
Regarding classification and diagnostic criteria, it is important to emphasize that they are intended as classification criteria rather than diagnostic criteria. Their use is primarily for scientific studies, research protocols and to assist non-specialist physicians in identifying potential cases of the disease. All seven of our patients met the aforementioned classification/diagnostic criteria.
There are widely used classification and diagnostic criteria for IgG4-RD in adult patients. The ACR/EULAR criteria were evaluated in 122 patients younger than 25 years, among which 33 (27%) cases met the exclusion criteria and only 35 (39%) of the remaining 89 cases had a score of 20 or more points on the inclusion criteria, leading to IgG4-RD classification. Similarly, the comprehensive diagnostic criteria were applied to the 122 patients: 29 cases (23.8%) were classified as definite, 20 (16.4%) as probable, 28 (23%) as possible, and 45 (36.9%) were excluded from an IgG4-RD diagnosis. These criteria may not be as effective in the pediatric population, nor was the response rate, which may not accurately reflect disease activity.6
In patients aged≤25 years, organ involvement was predominantly single-organ and mainly unilateral. Most of these patients presented with normal serum IgG4 levels. Approximately 30% of individuals with IgG4-related disease show normal serum IgG4 concentrations, particularly among those in the aforementioned group. Consequently, imaging studies are essential to rule out systemic involvement, and biopsy of the affected organ is of particular importance to evaluate histopathological and immunohistochemical findings in patients with these characteristics.
ConclusionIn our IgG4-RD database of 64 patients, we observed that 7 (11%) were aged≤25 years. The majority were women, with single-organ involvement. Four out of seven presented with unilateral ocular compromise, followed by hepato-pancreato-biliary involvement. The otological alterations found in this group warrant further investigation, as three out of five patients who underwent audiometry had sensorineural hearing loss. Regarding elevated serum IgG4 levels, only 3 out of 7 (43%) presented elevated levels, and none had decreased C3 levels. More than half of the patients had IgG2 levels≥5.3g/l. Lymphoplasmacytic infiltrate, eosinophilic infiltrate, storiform fibrosis and obliterative phlebitis were the most common findings in histopathological studies. While lymphoplasmacytic infiltrate was observed in all ocular biopsies, non-storiform fibrosis predominated in the group aged over 50 years. All patients met the classification criteria for IgG4-related disease.
When comparing this population with elderly patients, we observed that older patients exhibited significantly greater multiorgan involvement, constitutional symptoms and more pronounced involvement of lymph nodes, submandibular glands, and lungs. Ocular involvement was more frequent in younger patients, though the difference was not statistically significant; however, in patients over 50 years old, ocular involvement was bilateral, showing statistical significance. Overall, no significant differences were found between the two groups in terms of laboratory data or pathological anatomy, except for non-stromal fibrosis.
Informed consentWritten informed consent was obtained from the patients who participated in this study.
FundingNo specific funding was received from any bodies in the public, commercial or not-for-profit sectors to carry out the work described in this article.
Conflict of interestThe authors declare no conflict of interest.




