





Men with autoimmune diseases present specific pathophysiological factors such as chronic inflammation, pain, fatigue, endocrine alterations, and the effects of immunosuppressive therapy that may affect sexual function differently than in other populations. Our objective was to develop and validate a scale to measure sexual dysfunction in men with autoimmune diseases.
MethodsA quantitative, cross-sectional validation study was conducted. The study encompassed the theoretical construction of the instrument through its application in the target population, in order to evaluate its psychometric properties. Male patients over 18 years of age with a prior diagnosis of an autoimmune disease were included, while those with concomitant psychiatric conditions were excluded. The instrument was developed through three Delphi rounds. Internal reliability was assessed using Cronbach’s alpha coefficient, as well as McDonald’s total omega (ω total) and hierarchical omega (ωh). An exploratory factor analysis was also performed.
ResultsA final version of the instrument comprising 14 items distributed across two factors was obtained. Cronbach’s alpha coefficient was 0.93, indicating excellent reliability. To confirm and complement this estimate, McDonald’s omega coefficients were calculated. The total omega (ω = 0.95) confirmed high internal consistency, while the hierarchical omega (ωh = 0.77) indicated that a substantial proportion of the total variance was attributable to the general factor, supporting the validity of the identified bifactorial model.
ConclusionThe DS-HAI instrument demonstrated adequate psychometric properties for identifying sexual dysfunction in men, revealing a two-dimensional factorial structure.
Los hombres con enfermedades autoinmunes presentan factores fisiopatológicos precisos como inflamación crónica, dolor, fatiga, alteraciones endocrinas y efectos de la inmunosupresión que pueden afectar la función sexual de manera distinta a otras poblaciones. Nuestro objetivo fue desarrollar y validar una escala para medir la disfunción sexual en hombres con enfermedades autoinmunes.
MetodologíaSe realizó un estudio cuantitativo, con diseño transversal de tipo validación. El estudio comprendió desde la construcción teórica del instrumento hasta su aplicación en la población objetivo, con el fin de evaluar sus propiedades psicométricas. Se incluyeron pacientes masculinos mayores de 18 años con diagnóstico previo de enfermedad autoinmune. Se excluyeron aquellos con alguna condición psiquiátrica concomitante. Se construyó el instrumento a través de 3 rondas Delphi, se evaluó la confiabilidad interna del instrumento mediante el coeficiente alfa de Cronbach, así como el omega de Mc Donald total (ω total) y jerárquico (ωh). Se realizó un análisis factorial exploratorio.
ResultadosSe construyó una versión final del instrumento compuesta por 14 ítems distribuidos en dos factores. coeficiente alfa de Cronbach, que arrojó un valor de 0.93, indicando una excelente fiabilidad. Con el fin de contrastar y complementar esta estimación, se calculó el coeficiente omega de McDonald. El omega total (ω = 0.95) corroboró una alta consistencia interna, mientras que el omega jerárquico (ωh = 0.77), indicó que una proporción considerable de la varianza total es atribuible al factor general, lo cual respalda la validez del modelo bifactorial identificado.
ConclusiónEl instrumento DS-HAI mostró propiedades psicométricas adecuadas para la identificación de disfunción sexual en hombres, revelando una estructura factorial de dos dimensiones.
Sexual dysfunction is a condition that encompasses multiple areas. According to the Diagnostic and Statistical Manual of Mental Disorders (DSM-5), it is defined as a clinically significant disturbance in a person's ability to respond sexually or experience sexual pleasure for a minimum of six months, causing marked distress.1 According to this definition, sexual dysfunction (SD) has been identified in 9.3% of women and 6.2% of men in population studies.2
Rheumatic diseases can affect many aspects of sexual life, involving factors related to the disease itself and to its treatment. In the case of inflammatory diseases such as rheumatoid arthritis and axial spondyloarthritis, sexual dysfunction may be related to underlying depressive and anxiety disorders. In contrast, in Sjögren's syndrome (SS) and systemic lupus erythematosus (SLE), sexual dysfunction may be associated with pain and dryness, leading to dispareunia.3
Men with autoimmune diseases have specific pathophysiological factors, such as chronic inflammation, pain, fatigue, endocrine disturbances, and the effects of immunosuppression, which can affect sexual function differently to that observed in other populations. As instruments such as the International Index of Erectile Function-15 (IIEF-5) were primarily validated in the context of urological conditions, these variables were not considered, highlighting the need for specific tools to adequately assess the risk of sexual dysfunction in this patient group.
Another tool available for identifying sexual dysfunction in the general population is the CSFQ-14 questionnaire, which assesses changes in sexual function and activity. Although it is not specific to autoimmune diseases, it has recently been applied to this patient population, specifically rheumatoid arthritis (RA) and psoriatic arthritis (PsA), and a 10-fold increase in the risk of sexual dysfunction for RA and an 8.7-fold increase for PsA has been reported.4
Currently, instruments that do not comprehensively consider the variables influencing male sexual function continue to be used. Factors such as chronic pain, fatigue, medication use, particularly glucocorticoids, and perception of the disease can affect not only sexual desire but also the different phases of sexual response. In this context, there is a need for instruments with adequate psychometric properties that are specifically designed or validated for men with autoimmune diseases. This would allow for a more objective and accurate assessment of this condition.
Our objective was to develop and validate a scale to measure sexual dysfunction in men with autoimmune diseases.
MethodologyA quantitative study with a cross-sectional validation design was conducted. The study covered the theoretical construction of the instrument and its application to the target population in order to evaluate its psychometric properties. Male patients over the age of 18 with a previous diagnosis of a chronic autoimmune disease were included. These diseases included axial spondyloarthritis, rheumatoid arthritis, psoriasis/psoriatic arthritis, systemic lupus erythematosus (SLE), systemic sclerosis (SS), systemic vasculitis, Hashimoto's thyroiditis, inflammatory myopathies, and autoimmune liver diseases. Patients with any concomitant psychiatric condition, such as major depressive disorder, anxiety disorder, autism spectrum disorder, or psychotic disorders, were excluded.
Instrument construction and content validityIn constructing the instrument, sexual dysfunction was defined as a measurement variable and a multidimensional construct incorporating the factors applicable to males as defined in the DSM-51: delayed ejaculation, erectile disorder, hypoactive sexual desire disorder, premature ejaculation and substance/medication-induced sexual dysfunction. This construct also incorporated the satisfaction domain included in the National Institute of Health definition and reported in previous measurement instruments. Integrating these components created a broader, more comprehensive construct capable of encompassing the different dimensions of sexual dysfunction that could be affected in patients with autoimmune diseases. The Delphi method was then applied virtually using electronic voting. The panel of 7 experts consisted of 3 rheumatologists (MR, AG, and GA), one urologist (CB), one sexologist (AT), and 2 endocrinologists (CY and LK) from Colombia and Argentina. Panel members were required to have more than 5 years of clinical experience in the care of patients with sexual dysfunction or autoimmune diseases, depending on their area of specialisation. An iterative process was carried out, preserving the anonymity of the participants.
Three rounds were conducted:
- •
Round 1: ‘Brainstorm’.
- •
Round 2: ‘Assessment of the degree of agreement’.
- •
Round 3: ‘Content validation by expert judgment’, evaluating the sufficiency, clarity, coherence, and relevance of the criteria’.5
After each round, the relevant information was collected, and feedback was given to the panel of experts. Once the 47-item instrument had been finalised, a pilot test was conducted with 10 patients to assess their understanding of the items. Based on the results of this phase, the wording of some items was adjusted according to the frequency and clarity of the responses. Question D27, for example, was modified from ‘Do you associate lack of desire with any recent diagnosis or treatment?’ to ‘If you have experienced a reduction in sexual desire, do you relate it to a recent diagnosis or treatment?’.
This change was made because several patients stated that the original question presupposed the existence of a lack of desire, which could have biased the responses.
Validation of psychometric propertiesThe psychometric properties were evaluated in a sample of 75 patients undergoing active rheumatology follow-up for autoimmune diseases, selected in accordance with the recommendations of the International Test Commission.6
Item refinement processThe following criteria were taken into account for the instrument review and item refinement process: low factor loadings <.40, items with cross-loadings on several factors, low item-total correlation index, redundancy or lack of semantic clarity, and low theoretical or conceptual contribution.
Descriptive analysis of the itemsMeasures of central tendency and dispersion were calculated for each item, and the symmetry, kurtosis, difficulty, and discrimination indices were estimated using classical test theory (CTT). Mardia’s multivariate normality test was applied, and subsequently, the matrix of inter-item correlations and items with the scale average was constructed.
Internal consistencyThe internal reliability of the instrument was evaluated using Cronbach’s alpha coefficient,7 considering values ≥.70 as indicative of acceptable internal consistency,8 as well as McDonald’s total omega (total ω) and hierarchical omega (hω).9
Construct validationGiven the exploratory nature of the study, an exploratory factor analysis was performed using the weighted least squares estimation method with oblique rotation (Oblimin), with the aim of identifying an underlying factor structure that would allow the correlation between factors to be determined.
- •
The model was identified beforehand to determine the number of parameters to be estimated: 84, and the number of pieces of information: 190.
- •
The adequacy of the data was evaluated using the coefficient of determination, the Kaiser-Meyer-Olkin (KMO) index, and Bartlett's sphericity test. A coefficient of determination between 0 and 1, a KMO index greater than .50, and a P < .05 value in Bartlett's test were considered adequate.
- •
For factor retention, eigenvalues greater than 1 (Kaiser criterion) and the analysis of the scree plot were taken into account, in addition to the theoretical interpretability of the factors. Factor loadings equal to or greater than .40 were considered acceptable.
- •
Communalities, unities, and cross-loadings were evaluated, and the difference index was determined considering ambivalence with differences of less than 20%. R version 4.3.1 was used for the analysis.
This study was approved by the research ethics committee of the hospital where it was conducted (CEI-022-2025), as well as by the ethics committee of CES University.
ResultsRound of experts- •
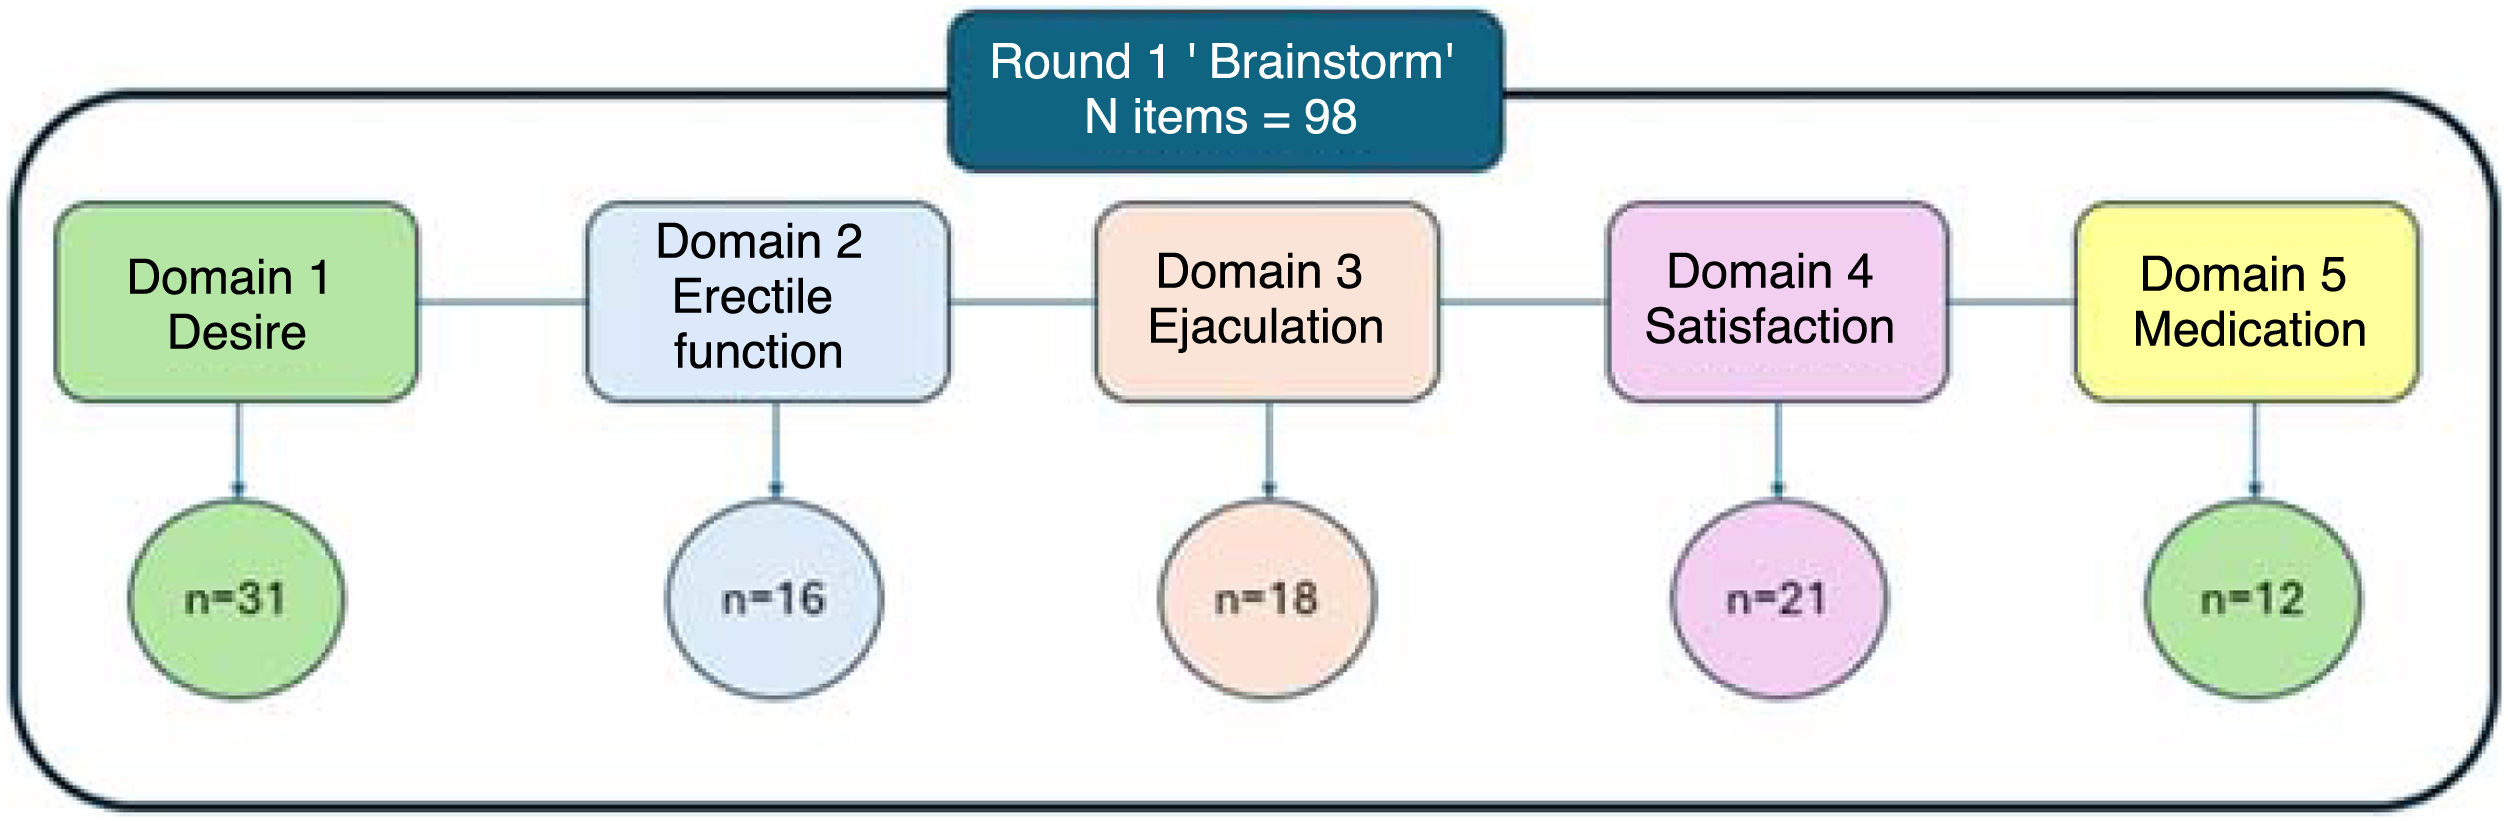
First round (brainstorm): This was based on an open question: ‘With regard to the different areas that define sexual dysfunction: desire, erection, ejaculation, satisfaction, medication, how would you assess the risk of this complication in male patients with autoimmune diseases?’ A total of 98 items were obtained, distributed as follows: domain 1: desire (31 items), domain 2: erectile function (16 items), domain 3: ejaculation (18 items), domain 4: satisfaction (21 items), domain 5: medications (12 items). There was an overrepresentation of the desire domain (Fig. 1).
- •
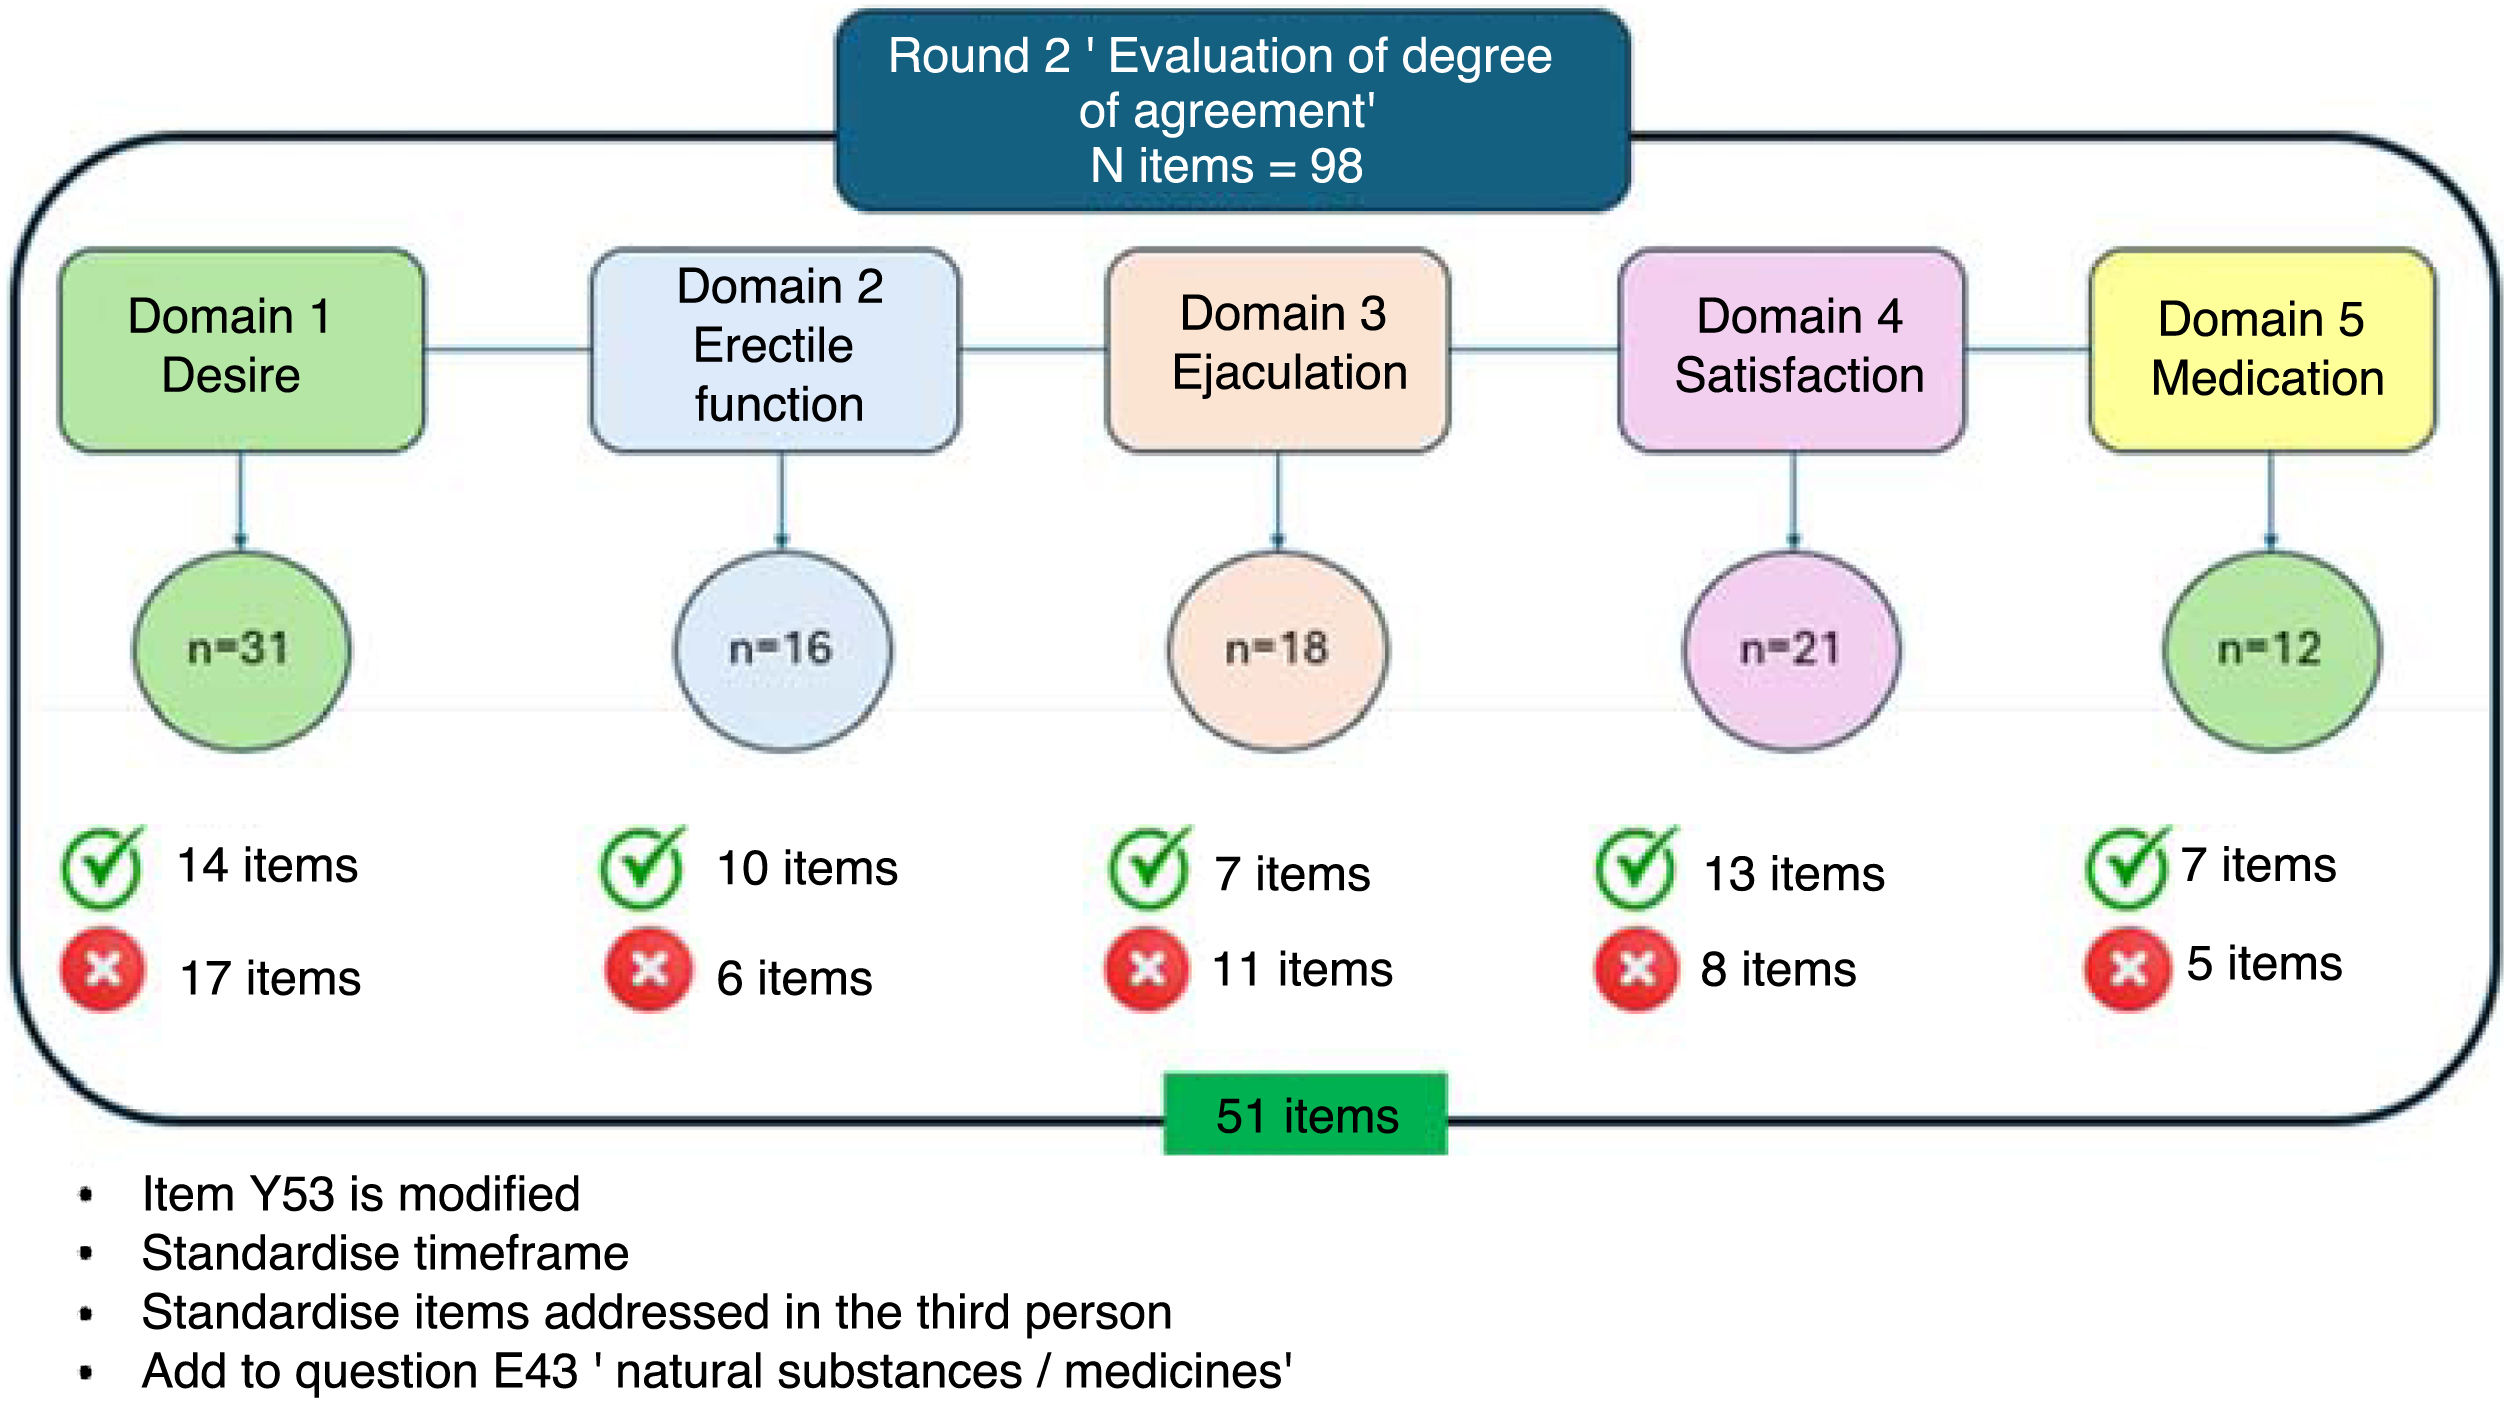
Second round (‘assessment of the degree of agreement’): the 98 items were edited, organised by domain, and experts were asked to rate their degree of agreement on a Likert scale as follows: 1=‘strongly disagree’, 2=‘disagree’, 3=‘neither agree nor disagree’, 4=‘agree’, 5=‘strongly agree’. Items with a level of agreement greater than 80% were selected. After this round, the items were reduced to 51, distributed as follows: domain 1: desire (14 items), domain 2: erectile function (10 items), domain 3: ejaculation (7 items), domain 4: satisfaction (21 items), domain 5: medications: 12 items. The items were modified according to their wording, standardisation in the time frame, and correction, addressing them in the third person, and question E43: ‘substances/natural medicines’ was added (Fig. 2).
- •
Round 3: (‘content validation by expert judgement’): evaluated using the template proposed by Escobar-Pérez and Cuervo-Martínez,10 which includes four categories: sufficiency: items belonging to the same dimension are sufficient to obtain the dimension of that item; clarity: the item is easily understood, i.e., its syntax and semantics are adequate; coherence: the item has a logical relationship with the dimension or indicator it is measuring; relevance: the item is essential or important, i.e., it must be included. The observations set out in Table 1 were obtained from this round.
Table 1.Round 3. Validation by expert judgement.
Original item Change made • Item D4: How often have you felt sexually aroused in the last six months? (low relevance). • It is very similar to item D1: How often have you felt sexual desire in the last 6 months? Item D4 is removed. • Item D16: Have you noticed that you think less about having sex since you were diagnosed with the autoimmune disease? (low coherence). • It is very similar to D11: Have you noticed any changes in sexual desire since your autoimmune disease began? D16 is removed. • Item D26: Do you have spontaneous erections in the early morning? (low coherence). • It more closely reflects the erectile function domain and is included in that domain. • Item E32: Have you had spontaneous erections unrelated to sexual activity? (low coherence). • Replaced: Have you had spontaneous erections (e.g., upon waking) that are firm enough to allow penetration and/or masturbation? • Item E44: Have you avoided sexual encounters for fear of not achieving a firm erection? (low coherence). • Replaced: Have you stopped having sex because of problems achieving or maintaining a firm erection? • Item E34: How often were you able to maintain an erection after penetration? • Does not assess the present time, only includes those with an active sex life, deleted. • Item S68: Am I satisfied with my sex life in general (low coherence)? • Ambiguity, replaced by: Are you satisfied with your sex life? • Item S70: Has my illness decreased the pleasure I usually experience during sex? (low coherence). • Replaced: Do you feel that your illness has negatively affected the pleasure you experience during sex? • Item S75: Do I avoid sex for fear of not feeling satisfied? (low coherence). • Double negative, replaced: Do I avoid having sex because I think I will not feel satisfied? • Item S76: Would I like to experience a more fulfilling sex life than I am currently experiencing? (low coherence). Talks about the future, not the present. Replace with: Are you satisfied with your current sex life? • Item S83: Are you satisfied with the quality of your sexual experiences since you began living with your autoimmune disease? (low coherence). • Changed to: Since living with your autoimmune disease, are you satisfied with your sexual experiences? • Item S84: Do you consider that your sex life meets your own expectations and those of your partner? (low coherence). • Individual perception of satisfaction; partner may alter coherence. Changed to: Does your sex life meet your expectations? - •
The pilot test was then applied to 10 patients to perform a cognitive evaluation of the items. Difficulties were found in the interpretation of item D27: Do you associate lack of desire with any recent diagnosis or treatment? This was replaced with: If you have experienced a reduction in sexual desire, do you relate it to a recent diagnosis or treatment? Item S66: How satisfied are you with your sex life? was replaced with How often do you feel satisfied with your sex life? At the end of the third round and the pilot test, a total of 47 items were obtained: desire (10 items), erectile function (10 items), ejaculation (7 items), satisfaction (13 items), medications (7 items).


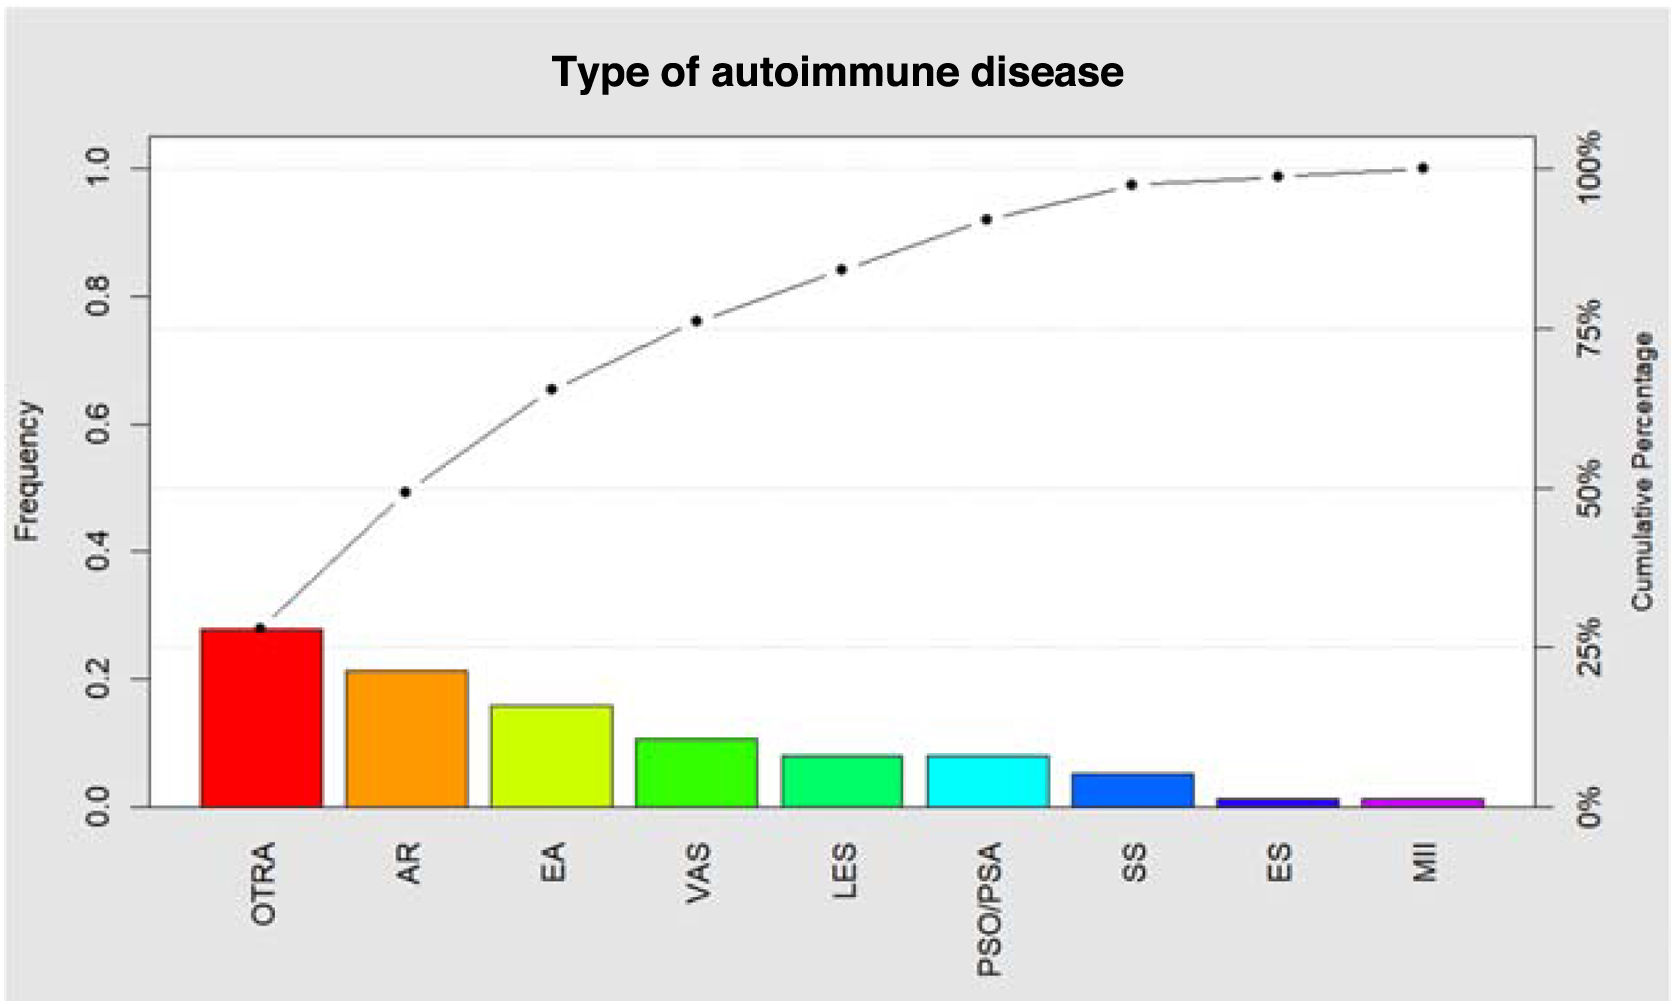
The mean age of the patients surveyed was 48 years (SD: 13.9), with a time since diagnosis of 3 years (range: 1–24); the median time taken to complete the questionnaire was 9 min (range: 1–45). The most common autoimmune diseases were rheumatoid arthritis in 21.3%, followed by axial spondyloarthritis (16%). Other diseases (Hashimoto’s thyroiditis, autoimmune hepatitis, primary biliary cholangitis) were included in the ‘other’ category in 28% of cases (Fig. 3). Mardia's multivariate normality test was performed and did not confirm the assumption of normality for asymmetry and kurtosis with P-values <.05. The difficulty index remained between 30% and 70%, and Cronbach's alpha for the initial version was .96. The instrument was then reviewed and items were refined.
Item refinement
The initial instrument consisted of 47 items. A preliminary refinement process was carried out based on statistical and conceptual criteria. Items with inter-item correlations greater than .80 were eliminated, as they were considered redundant or indicative of content overlap. Items that were repeated or showed significant semantic similarities were also discarded in order to improve clarity and reduce duplication of information.
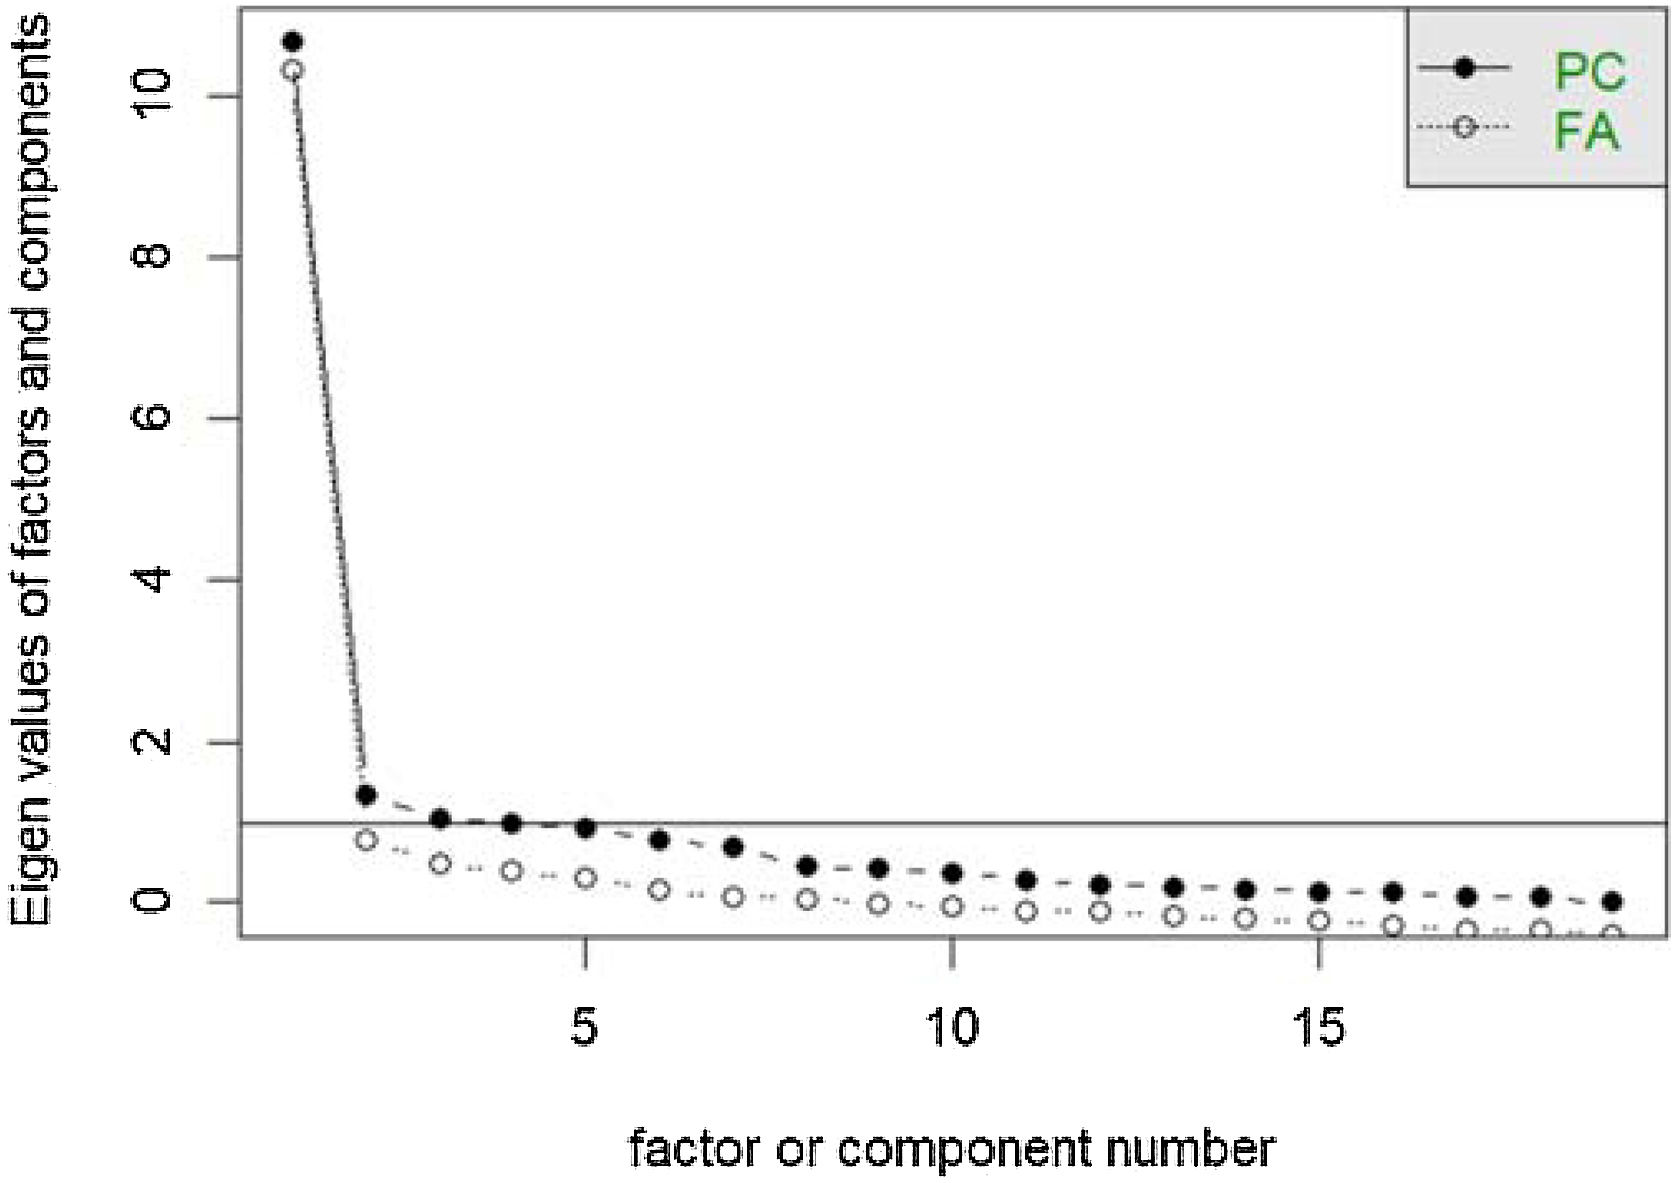
Construct validity (exploratory factor analysis)Sample adequacy measures revealed a coefficient of determination close to zero, with KMO = .89 and Bartlett's sphericity test <.01. The factorial solution identified two factors in the scree plot (Fig. 4).
- •
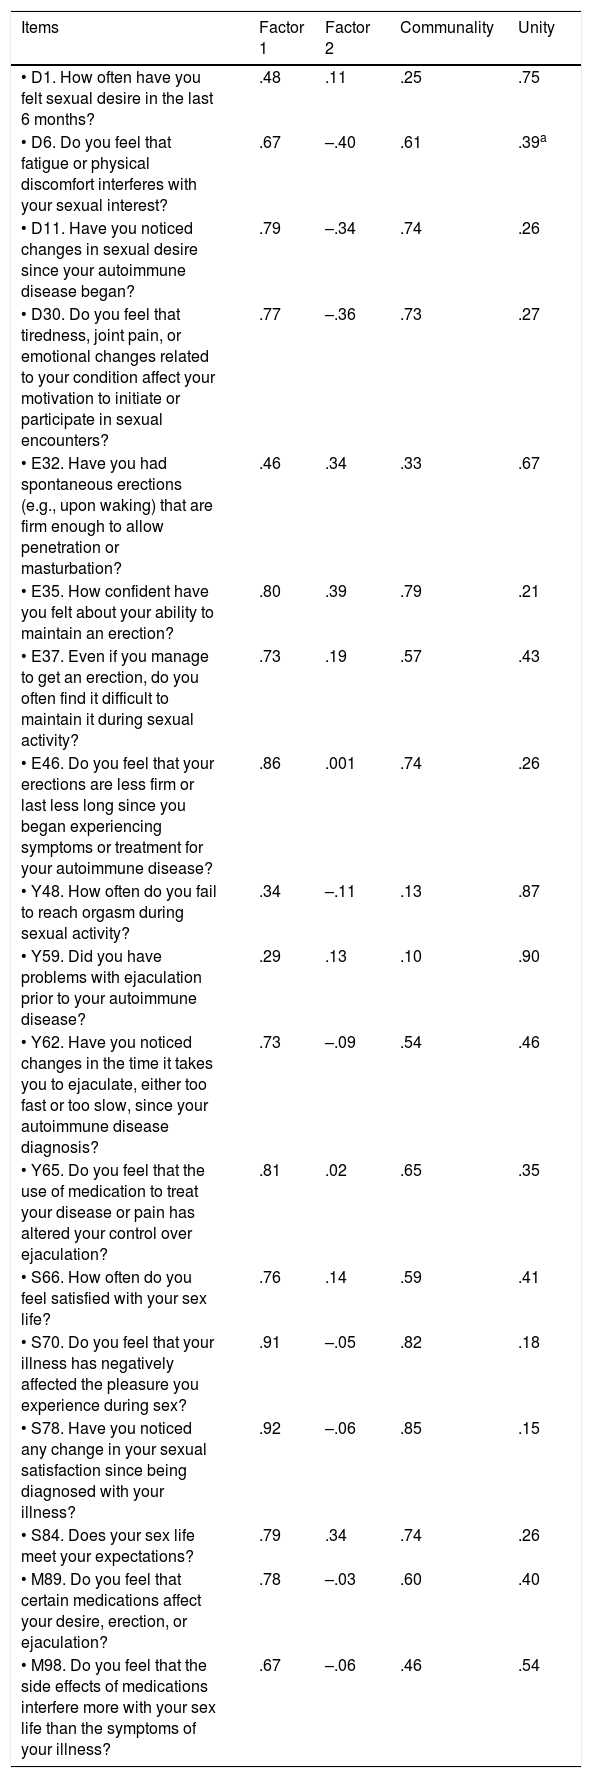
In the unrotated solution, all items loaded onto factor one, primarily question S78 (Have you noticed any change in your sexual satisfaction since your diagnosis?) and E46 (Do you feel that your erections are less firm or last less time since you began experiencing symptoms or receiving treatment for your autoimmune disease?) with factor loadings of .92 and .86. The only item that loaded onto factor 2 was D6 (Do you feel that fatigue or physical discomfort interferes with your sexual interest?) with a loading of −.40 (Table 2) and a variance proportion of 52% for factor 1 and 7% for factor 2.
Table 2.Unrotated factor loadings.
Items Factor 1 Factor 2 Communality Unity • D1. How often have you felt sexual desire in the last 6 months? .48 .11 .25 .75 • D6. Do you feel that fatigue or physical discomfort interferes with your sexual interest? .67 –.40 .61 .39a • D11. Have you noticed changes in sexual desire since your autoimmune disease began? .79 –.34 .74 .26 • D30. Do you feel that tiredness, joint pain, or emotional changes related to your condition affect your motivation to initiate or participate in sexual encounters? .77 –.36 .73 .27 • E32. Have you had spontaneous erections (e.g., upon waking) that are firm enough to allow penetration or masturbation? .46 .34 .33 .67 • E35. How confident have you felt about your ability to maintain an erection? .80 .39 .79 .21 • E37. Even if you manage to get an erection, do you often find it difficult to maintain it during sexual activity? .73 .19 .57 .43 • E46. Do you feel that your erections are less firm or last less long since you began experiencing symptoms or treatment for your autoimmune disease? .86 .001 .74 .26 • Y48. How often do you fail to reach orgasm during sexual activity? .34 –.11 .13 .87 • Y59. Did you have problems with ejaculation prior to your autoimmune disease? .29 .13 .10 .90 • Y62. Have you noticed changes in the time it takes you to ejaculate, either too fast or too slow, since your autoimmune disease diagnosis? .73 –.09 .54 .46 • Y65. Do you feel that the use of medication to treat your disease or pain has altered your control over ejaculation? .81 .02 .65 .35 • S66. How often do you feel satisfied with your sex life? .76 .14 .59 .41 • S70. Do you feel that your illness has negatively affected the pleasure you experience during sex? .91 –.05 .82 .18 • S78. Have you noticed any change in your sexual satisfaction since being diagnosed with your illness? .92 –.06 .85 .15 • S84. Does your sex life meet your expectations? .79 .34 .74 .26 • M89. Do you feel that certain medications affect your desire, erection, or ejaculation? .78 –.03 .60 .40 • M98. Do you feel that the side effects of medications interfere more with your sex life than the symptoms of your illness? .67 –.06 .46 .54 - •
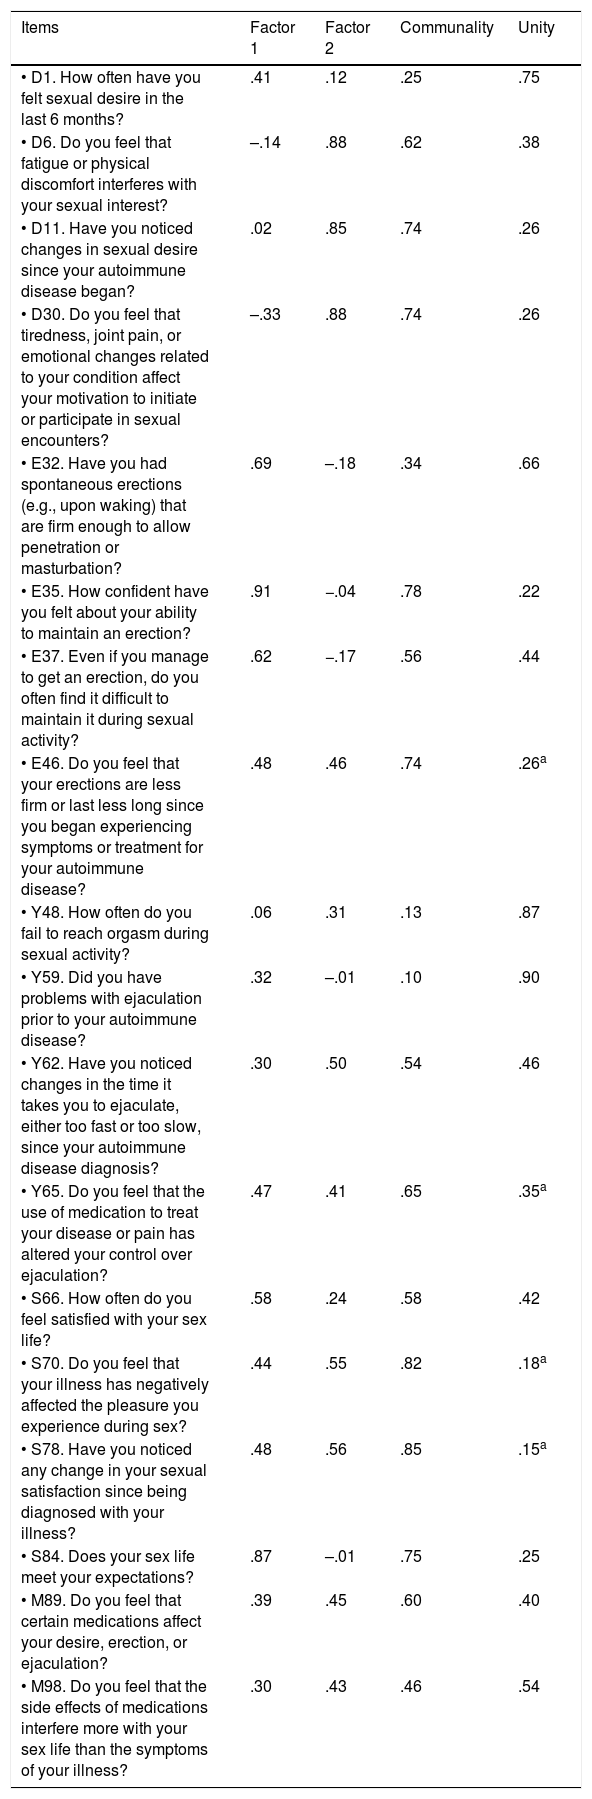
When the oblique rotation was performed using ‘Oblimin’, given that a certain dependence between the factors was assumed, a better distribution between the factors was evident: factor 1: items D1 (How often have you felt sexual desire in the last 6 months?), E35 (How confident have you felt about your ability to maintain an erection?), E32 (Have you had spontaneous erections (e.g., upon waking) that are firm enough to allow penetration or masturbation?), E37 (Even if you manage to get an erection, do you often find it difficult to maintain it during sexual activity?), E66 (How often do you feel satisfied with your sex life?), S84 (Does your sex life meet your expectations?), and factor 2: D6 (Do you feel that fatigue or physical discomfort interferes with your sexual interest?), D11 (Have you noticed changes in sexual desire since your autoimmune disease began?) D30 (Do you feel that tiredness, joint pain, or emotional changes related to your condition affect your motivation to initiate or participate in sexual encounters?), Y62 (Have you noticed changes in the time it takes you to ejaculate, either too fast or too slow since the diagnosis of your autoimmune disease?), S70 (Do you feel that your illness has negatively affected the pleasure you experience during sex?), S78 (Have you noticed that your sexual satisfaction has changed since your diagnosis?), M89(Do you feel that certain medications affect your desire, erection, or ejaculation?), M98 (Do you feel that the side effects of medications interfere more with your sex life than the symptoms of your disease?), with a proportion of variance of .29 for factor 1 and .49 for factor 2, correlation between factors of 68%, complexity index of 1.4 and RMSR: .06. Cross-loadings were identified in items E46 and Y65, which were eliminated due to difference indices of less than 20%, reflecting ambivalence, and the cross-loadings of S78 and S70 were retained in the factor with the highest loading, taking into account the high communality value (Table 3).
Table 3.Rotated exploratory factor analysis (Oblimin).
Items Factor 1 Factor 2 Communality Unity • D1. How often have you felt sexual desire in the last 6 months? .41 .12 .25 .75 • D6. Do you feel that fatigue or physical discomfort interferes with your sexual interest? –.14 .88 .62 .38 • D11. Have you noticed changes in sexual desire since your autoimmune disease began? .02 .85 .74 .26 • D30. Do you feel that tiredness, joint pain, or emotional changes related to your condition affect your motivation to initiate or participate in sexual encounters? –.33 .88 .74 .26 • E32. Have you had spontaneous erections (e.g., upon waking) that are firm enough to allow penetration or masturbation? .69 –.18 .34 .66 • E35. How confident have you felt about your ability to maintain an erection? .91 −.04 .78 .22 • E37. Even if you manage to get an erection, do you often find it difficult to maintain it during sexual activity? .62 −.17 .56 .44 • E46. Do you feel that your erections are less firm or last less long since you began experiencing symptoms or treatment for your autoimmune disease? .48 .46 .74 .26a • Y48. How often do you fail to reach orgasm during sexual activity? .06 .31 .13 .87 • Y59. Did you have problems with ejaculation prior to your autoimmune disease? .32 –.01 .10 .90 • Y62. Have you noticed changes in the time it takes you to ejaculate, either too fast or too slow, since your autoimmune disease diagnosis? .30 .50 .54 .46 • Y65. Do you feel that the use of medication to treat your disease or pain has altered your control over ejaculation? .47 .41 .65 .35a • S66. How often do you feel satisfied with your sex life? .58 .24 .58 .42 • S70. Do you feel that your illness has negatively affected the pleasure you experience during sex? .44 .55 .82 .18a • S78. Have you noticed any change in your sexual satisfaction since being diagnosed with your illness? .48 .56 .85 .15a • S84. Does your sex life meet your expectations? .87 –.01 .75 .25 • M89. Do you feel that certain medications affect your desire, erection, or ejaculation? .39 .45 .60 .40 • M98. Do you feel that the side effects of medications interfere more with your sex life than the symptoms of your illness? .30 .43 .46 .54

- •
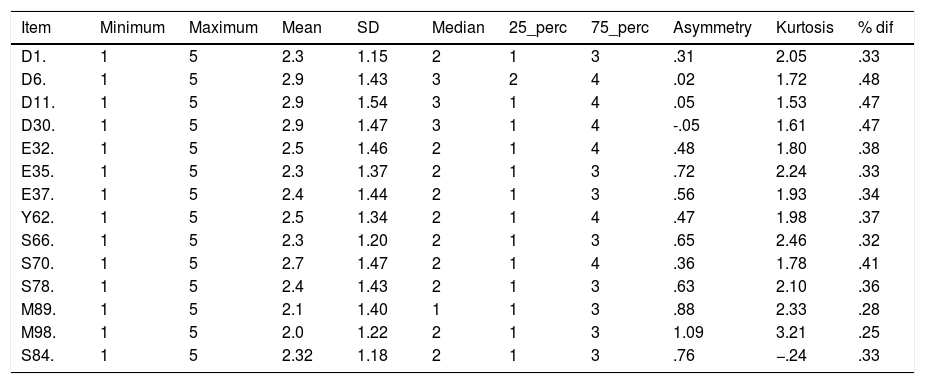
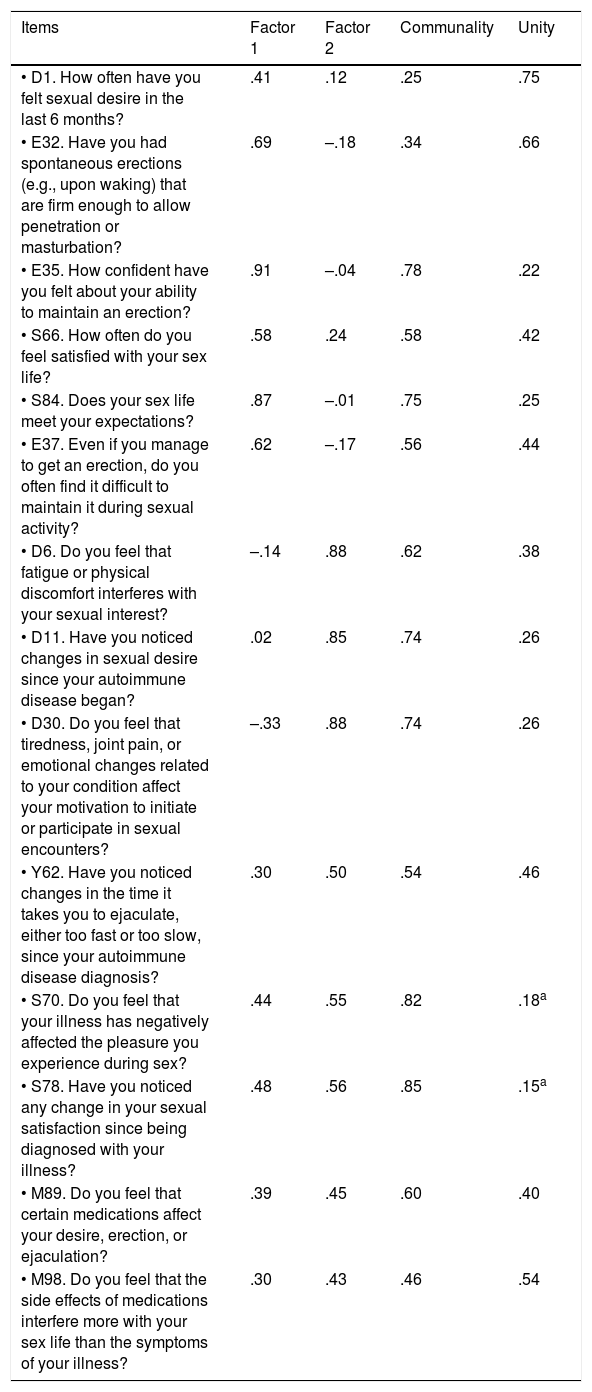
Following exploratory factor analysis, items with factor loadings greater than .40 were selected, allowing for the construction of a final version of the instrument consisting of 14 items distributed across two factors (Table 4). The total possible score on the scale is 14–70, with a higher score indicating a greater degree of dysfunction. In the sample analysed, the median was 32 points (IQR: 24–43), values that could also be considered as preliminary references for the clinical interpretation of the scale. To assess the internal consistency of the scale, Cronbach's alpha coefficient was estimated again, yielding a value of .93, indicating excellent reliability. In order to contrast and complement this estimate, McDonald's omega coefficient was calculated. The total omega (ω = .95) corroborated high internal consistency, while the hierarchical omega (hω = .77), indicated that a considerable proportion of the total variance is attributable to the general factor, which supports the validity of the identified two-factor model. The asymmetry and kurtosis values remained within acceptable ranges. The percentage of difficulty varied between .25 and .48, showing that the items have a moderate level of difficulty, adequate for discriminating between different levels of the construct evaluated. Most items showed adequate discrimination indices with levels above .70, indicating a good ability to discriminate between individuals with high and low scores (Table 4). However, items D1: How often have you felt sexual desire in the last 6 months? and E32: Have you had spontaneous erections (e.g., upon waking) that were firm enough to allow penetration or masturbation? had moderate discrimination indices of .53 and .50, respectively, which may be re-evaluated in future psychometric validation versions. Table 5 summarises the final version with the factor loadings distributed across the 2 dimensions.
Table 4.Descriptive summary, final version.
Item Minimum Maximum Mean SD Median 25_perc 75_perc Asymmetry Kurtosis % dif D1. 1 5 2.3 1.15 2 1 3 .31 2.05 .33 D6. 1 5 2.9 1.43 3 2 4 .02 1.72 .48 D11. 1 5 2.9 1.54 3 1 4 .05 1.53 .47 D30. 1 5 2.9 1.47 3 1 4 -.05 1.61 .47 E32. 1 5 2.5 1.46 2 1 4 .48 1.80 .38 E35. 1 5 2.3 1.37 2 1 3 .72 2.24 .33 E37. 1 5 2.4 1.44 2 1 3 .56 1.93 .34 Y62. 1 5 2.5 1.34 2 1 4 .47 1.98 .37 S66. 1 5 2.3 1.20 2 1 3 .65 2.46 .32 S70. 1 5 2.7 1.47 2 1 4 .36 1.78 .41 S78. 1 5 2.4 1.43 2 1 3 .63 2.10 .36 M89. 1 5 2.1 1.40 1 1 3 .88 2.33 .28 M98. 1 5 2.0 1.22 2 1 3 1.09 3.21 .25 S84. 1 5 2.32 1.18 2 1 3 .76 −.24 .33 SD: standard deviation; 25_perc: 25th percentile; 75_perc: 75th percentile; % dif: percentage of difficulty.
Table 5.Final version of the ‘Oblimin’ rotated factorial questionnaire.
Items Factor 1 Factor 2 Communality Unity • D1. How often have you felt sexual desire in the last 6 months? .41 .12 .25 .75 • E32. Have you had spontaneous erections (e.g., upon waking) that are firm enough to allow penetration or masturbation? .69 –.18 .34 .66 • E35. How confident have you felt about your ability to maintain an erection? .91 –.04 .78 .22 • S66. How often do you feel satisfied with your sex life? .58 .24 .58 .42 • S84. Does your sex life meet your expectations? .87 –.01 .75 .25 • E37. Even if you manage to get an erection, do you often find it difficult to maintain it during sexual activity? .62 –.17 .56 .44 • D6. Do you feel that fatigue or physical discomfort interferes with your sexual interest? –.14 .88 .62 .38 • D11. Have you noticed changes in sexual desire since your autoimmune disease began? .02 .85 .74 .26 • D30. Do you feel that tiredness, joint pain, or emotional changes related to your condition affect your motivation to initiate or participate in sexual encounters? –.33 .88 .74 .26 • Y62. Have you noticed changes in the time it takes you to ejaculate, either too fast or too slow, since your autoimmune disease diagnosis? .30 .50 .54 .46 • S70. Do you feel that your illness has negatively affected the pleasure you experience during sex? .44 .55 .82 .18a • S78. Have you noticed any change in your sexual satisfaction since being diagnosed with your illness? .48 .56 .85 .15a • M89. Do you feel that certain medications affect your desire, erection, or ejaculation? .39 .45 .60 .40 • M98. Do you feel that the side effects of medications interfere more with your sex life than the symptoms of your illness? .30 .43 .46 .54
Sexual function is an important aspect of quality of life, especially for individuals with chronic inflammatory diseases. The various domains that comprise this latent variable can be influenced by factors such as pain, fatigue, mood swings, and emotional changes.
Sexual dysfunction is currently classified as a distinct clinical entity, which includes the following components: delayed ejaculation, erectile disorder, female orgasmic disorder, female sexual interest disorder, genito-pelvic pain, hypoactive sexual desire, premature ejaculation, substance or medication-induced dysfunction, other sexual dysfunction, and unspecified sexual dysfunction,11 limiting the identification of this disorder to disturbances in sexual response in most cases.
Most definitions of sexual dysfunction are based on Master and Johnson’s 1990 model, which is based on the four phases of the sexual cycle: excitement, plateau, orgasm, and resolution. Similarly, differences in these phases are described according to sex, with males experiencing a refractory period after the resolution phase.12
However, given the differences in the phases of the sexual cycle between the 2 sexes, in the case of men, erectile dysfunction is defined as the inability to attain and maintain erection of the penis sufficient to permit satisfactory sexual intercourse, according to the National Institute of Health.13
Male patients suffer from inflammatory diseases with lower prevalence, although the mechanisms are not fully understood. It has been proposed that male gonadal hormone deficiency, as occurs in hypogonadotropic hypogonadism and Klinefelter syndrome, could favour a higher prevalence of these diseases due to an increased cellular and humoral immune response, as well as greater expression of anti-extractable nuclear antibodies.14
In adults with hypogonadism, sexual dysfunction can occur in 1.7%–35% of cases, related to erectile dysfunction, decreased libido, and frequency of nocturnal erections. It may be accompanied by other symptoms such as fatigue, depression, anaemia and decreased bone mineral density15; although it should be noted that psychiatric manifestations could negatively influence sexual performance.
Psychiatric symptoms accompanying immune disorders such as anxiety and depression may behave as independent predictors of sexual dysfunction; although when evaluating the correlation between the International Index of Erectile Function (IIEF) and anxiety and depression, they were found to be negatively correlated (r = −.30, P = .004 and r = −.22, P = .04) respectively.16
The IIFE-15 is a validated instrument consisting of 15 items assessing erection frequency, erection firmness, penetration capacity, maintenance frequency, maintenance capacity, intercourse frequency, intercourse satisfaction, intercourse enjoyment, ejaculation frequency, orgasm frequency, frequency of desire, level of desire, total satisfaction, relationship satisfaction, and confidence in erection. The instrument was subsequently simplified by selecting the items: maintenance capacity, confidence in erection, maintenance frequency, erection firmness, and penetration capacity for the last 6 months. A Cronbach's alpha of .85 was estimated with a sensitivity of 98% and specificity of 88% for this latest version.17
Merallo-Chalico et al., 2019, used the IIFE-5 instrument in patients with lupus to assess the prevalence of erectile dysfunction, showing that it occurs in 69% of men with lupus, and demonstrating that lymphopenia and recent use of glucocorticoids behave as independent risk factors for ED.18
Although the IIEF-15 is a widely validated tool for assessing erectile dysfunction, it has certain important limitations in terms of its applicability as a comprehensive measure of sexual function in accordance with current definitions such as that of the DSM-5, given that it does not incorporate items related to ejaculation disorders (delayed/premature) and non-erectile components of sexual function such as psychosocial factors and medication.
This study involved the development of a new instrument that incorporates items designed to capture characteristic aspects of autoimmune diseases, such as joint pain, fatigue, tiredness, and medication use. Factor analysis revealed a structure comprising two distinct dimensions: factor 1, which grouped items related to general sexual health, and factor 2, which grouped items specifically related to the symptoms of autoimmune diseases. The instrument demonstrated robust psychometric properties, thereby supporting its relevance for assessment in this clinical context.
Identifying these 2 dimensions is a significant achievement as it demonstrates the connection between sexual health and the characteristics of autoimmune diseases. This highlights the importance of assessing them together, thereby enhancing the value of this tool in the clinical measurement of sexual dysfunction in men with autoimmune diseases.
The main limitations of this study are the number of participants (n = 75), which is the minimum acceptable for a 14-item instrument. While it is well known that a small sample size can increase the probability of error in factor analyses, this limitation is offset by the high communality of the items and the robust factor loadings observed in this study, which reinforces the robustness of the factor solution obtained.19
The main strength of this study is that it has developed and validated the first instrument with adequate psychometric properties for measuring the latent variable of sexual dysfunction in men with autoimmune diseases.
ConclusionThe instrument for assessing sexual dysfunction in men with autoimmune diseases (DS-HAI) showed adequate psychometric properties for identifying sexual dysfunction in men, revealing a two-dimensional factor structure. This solution is useful for integrating the assessment of sexual dysfunction with the components of autoimmune diseases, thus strengthening its applicability in healthcare practice.
CRediT authorship contribution statementPedro Arbey Quevedo Mayorga: Lead author, writing of the research protocol and manuscript, coordinator of the expert panel. Fieldwork, application of the pilot test and final instrument, data analysis.
Diana Isabel Muñoz: Manuscript reviewer, PhD lecturer in epidemiology and biostatistics, guidance in the research process.
Bibiana Andrea Castro: Manuscript reviewer, PhD lecturer in epidemiology and biostatistics, guidance in the research process, advisor on the instrument validation process.
Daniel Fernández Ávila: Manuscript reviewer, PhD professor in epidemiology and biostatistics, guidance in the research process.
Andrea Gómez: Rheumatologist member of the expert committee who participated in each of the Delphi rounds.
Mariano Rivero: Rheumatologist member of the expert committee who participated in each of the Delphi rounds.
Andrés González: Rheumatologist member of the expert committee who participated in each of the Delphi rounds.
Carlos Yepes: Endocrinologist member of the expert committee who participated in each of the Delphi rounds.
Laura Kattah Martinez: Endocrinologist member of the expert committee who participated in each of the Delphi rounds.
Christian Bernal: Urologist member of the expert committee who participated in each of the Delphi rounds.
Andrea Criollo Gómez: Clinical sexology psychologist member who participated in each of the Delphi rounds.
Ethical considerationsThis study was approved by the research ethics committee of the Hospital Universitario Clinica San Rafael in Bogotá, Colombia, and was also approved by the research ethics committee of the CES University in Medellín, Colombia.
Declaration of Generative AI and AI-assisted technologies in the writing processNo artificial intelligence tools were used in developing this analysis.
FundingThis research study received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
The authors have no conflict of interests to declare.
The following is Supplementary data to this article:





