



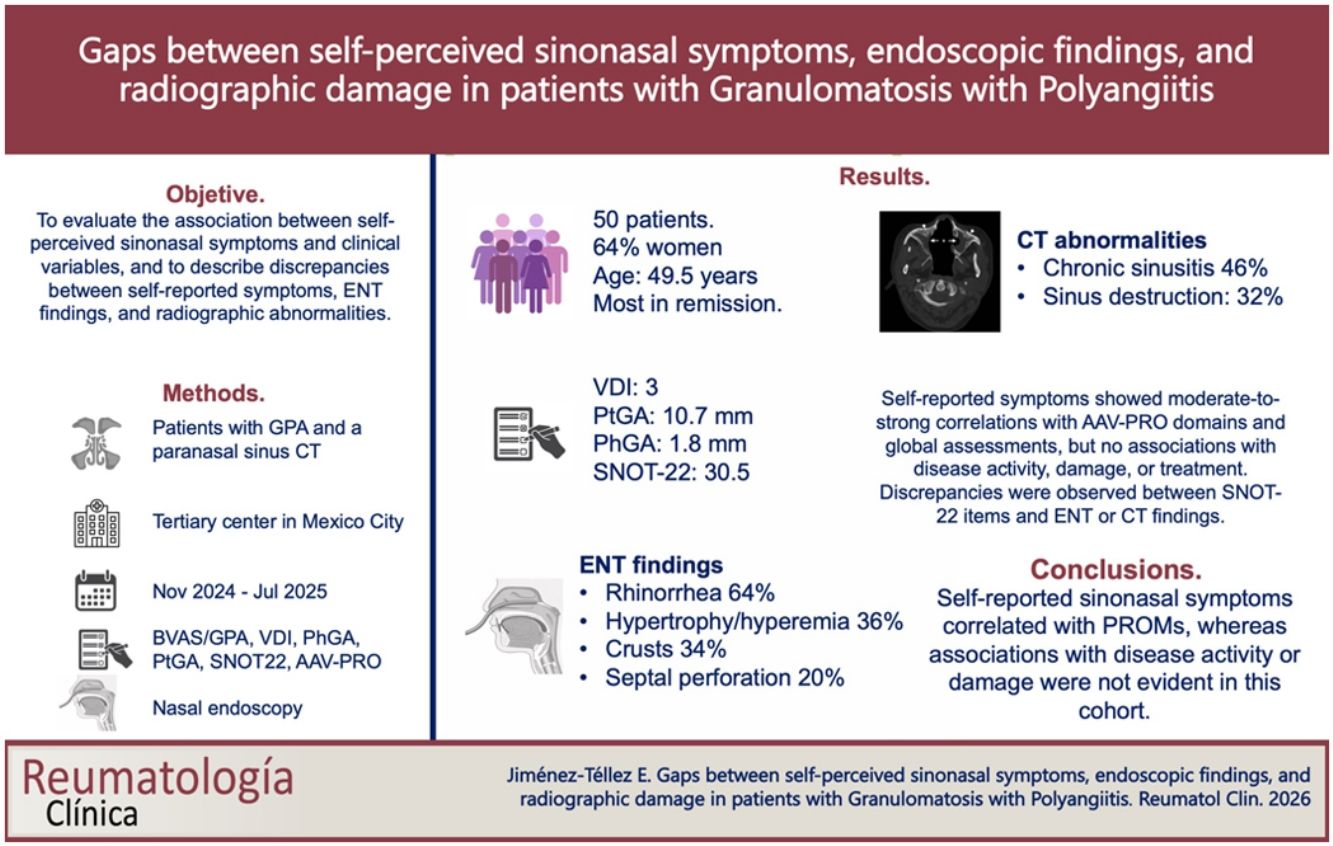
Sinonasal symptoms occur in up to 80% of patients with granulomatosis with polyangiitis (GPA), affecting quality of life. This study aimed to evaluate the association between self-perceived sinonasal symptoms (SNOT-22 questionnaire), and clinical variables, and to describe discrepancies between self-reported symptoms, ENT findings, and radiographic abnormalities.
MethodsA cross-sectional study was conducted at a tertiary center in Mexico City (November 2024–July 2025). Patients with GPA and a paranasal sinus CT scan within two years were included. Data collection comprised demographic, clinical, laboratory, and treatment variables. Assessments included disease activity (BVAS/GPA), cumulative damage (VDI), patient and physician global assessments (PhGA and PtGA), and PROMs (SNOT-22, AAV-PRO). All patients underwent ENT examination with nasal endoscopy.
ResultsFifty patients were included, 64% women, median age 49.5 years, and disease duration 88.5 months. Most were in remission (median BVAS/GPA 0). The median VDI was 3, PtGA 10.7mm, and PhGA 1.8mm. The median SNOT-22 score was 30.5. Common ENT findings were rhinorrhea (64%), hypertrophic turbinates or hyperemic mucosa (36%), nasal crusts (34%), and septal perforation (20%). CT abnormalities included chronic sinusitis (46%) and sinus destruction (32%). Self-reported symptoms showed moderate-to-strong correlations with AAV-PRO domains and global assessments, but no associations with disease activity, damage, or treatment. Discrepancies were observed between SNOT-22 items and ENT or CT findings.
ConclusionsSelf-reported sinonasal symptoms correlated with PROMs, whereas associations with disease activity or damage were not evident in this cohort. Discrepancies highlight the need for GPA-specific studies integrating PROMs, standardized ENT assessments, and imaging.
Los síntomas sinonasales ocurren en el 80% de los pacientes con granulomatosis con poliangitis (GPA) y afectan la calidad de vida. El objetivo fue evaluar la asociación entre los síntomas sinonasales percibidos por el paciente (cuestionario SNOT-22), y variables clínicas, describir las discrepancias entre síntomas autoinformados, hallazgos otorrinolaringológicos y alteraciones radiográficas.
MétodosEstudio transversal realizado en un centro terciario. Se incluyeron pacientes con GPA y tomografía computarizada (TC) de senos paranasales realizada en los dos años previos. Se recolectaron variables demográficas, clínicas, de laboratorio y tratamiento. Las evaluaciones incluyeron actividad de la enfermedad (BVAS/GPA), daño (VDI), evaluaciones globales del médico y paciente (PhGA y PtGA) y PROMs (SNOT-22 y AAV-PRO). Todos los pacientes fueron evaluados por otorrinolaringología mediante endoscopia nasal.
ResultadosSe incluyeron 50 pacientes, 64% mujeres, con mediana de edad de 49.5 años y duración mediana de la enfermedad de 88.5 meses. La mayoría se encontraba en remisión. La mediana del VDI fue 3, de la PtGA 10.7mm y de la PhGA 1.8mm. La puntuación mediana del SNOT-22 fue 30.5. Los hallazgos sinonasales más frecuentes fueron rinorrea (64%), cornetes hipertróficos o mucosa hiperémica (36%), costras nasales (34%) y perforación septal (20%). En la TC se observó sinusitis crónica en 46% y destrucción de senos paranasales en 32%. Los síntomas autoinformados se correlacionaron con los dominios del AAV-PRO y las evaluaciones globales, pero no con actividad, daño ni tratamiento. Se identificaron discrepancias entre el SNOT-22 y los hallazgos clínicos o radiográficos.
ConclusionesLos síntomas sinonasales percibidos por el paciente se asocian con PROMs, pero no con la actividad ni el daño de la enfermedad.

Antineutrophil cytoplasmic antibody (ANCA)-associated vasculitis (AAV) is a group of rare, multisystem diseases characterized by necrotizing small-vessel vasculitis with few or no immune deposits. AAV is associated with ANCA targeting proteins such as myeloperoxidase (MPO) or proteinase 3 (PR3). The main variants include granulomatosis with polyangiitis (GPA), eosinophilic GPA (EGPA), and microscopic polyangiitis (MPA).1
GPA is most commonly associated with PR3-ANCA positivity (65–75%), typically involves the upper and lower respiratory tracts, and presents with granulomatous inflammation.1,2 Common clinical manifestations include otitis, conductive hearing loss, orbital pseudotumors, subglottic stenosis, capillaritis with vasculitis, alveolar hemorrhage, and glomerulonephritis.2 Nasal and sinus symptoms occur in 64–80% of patients and include chronic sinusitis, crusting, rhinorrhea, obstruction, epistaxis, septal perforation, and saddle-nose deformity.3,4 Facial pain, hyposmia, anosmia, or cacosmia may also be present. These manifestations negatively impact quality of life, affecting social and daily functioning.5,6 CT findings commonly include mucosal thickening, bone and septal destruction, sclerosis, neo-osteogenesis, calcifications, and sinus opacification.4
Among the patient-reported outcome measures (PROMs) is the 22-item Sinonasal Outcome Test (SNOT-22), a self-administered questionnaire validated to assess the impact of chronic rhinosinusitis (CRS) of any etiology on health-related quality of life.7 This instrument evaluates symptom severity, social and emotional impact, productivity, and sleep disturbances related to CRS.8 It has been administered to patients with AAV, showing a correlation with disease activity measured by the Birmingham Vasculitis Activity Score (BVAS) and, prospectively, higher scores have been associated with an increased risk of disease relapse, suggesting that CRS may contribute to the pathophysiology of relapses in patients with AAV.6,9 In addition, the ANCA-associated vasculitis patient-reported outcomes questionnaire (AAV-PRO) is a 29-item tool that assesses symptoms, treatment effects, emotional and social impact, future concerns, and physical function.10 Integrating these tools into clinical practice provides valuable insights into patients’ experiences and complements physician assessments.
Therefore, this study aimed to evaluate the association between self-perceived sinonasal symptoms, as reported in the SNOT-22 questionnaire, and other clinical variables, as well as to describe discrepancies between these self-reported symptoms, ENT examination findings, and sinonasal radiographic abnormalities in patients with GPA.
Patients and methodsStudy design and patientsThis cross-sectional study was conducted from November 1, 2024, to July 30, 2025 at the Instituto Nacional de Ciencias Médicas y Nutrición Salvador Zubirán, a tertiary care center in Mexico City. The study was approved by the Institutional Research and Ethics Committees on October 2024 (Reference number 5323). Written informed consent was obtained from all participants, and all procedures adhered to the principles laid down in the 1964 Declaration of Helsinki and its later amendments.
Eligible patients were aged ≥18 years and had a diagnosis of GPA following the 2012 Chapel Hill Consensus Conference nomenclature11 and/or the 2022 American College of Rheumatology/European Alliance of Associations for Rheumatology (ACR/EULAR) classification criteria.12 All included patients had undergone a paranasal sinus CT scan at our institution between 0 and 48 months before the evaluation. In 30 patients (60%), the CT scan had been performed within the year prior to the evaluation. Patients were excluded if they had a diagnosis of another overlapping autoimmune disease; symptoms of an upper respiratory tract infection on the day of evaluation (based on the reported time of symptom onset, presence of fever or other upper respiratory manifestations, and recent contact with individuals exhibiting similar symptoms); a history of nasal or paranasal sinus surgery; a history of inhaled cocaine use; or use of intranasal topical steroids within the previous two weeks.
Data collection and measurementsCollected data included demographic, clinical, laboratory, and treatment-related variables. A comprehensive medical evaluation was performed by two rheumatologists and included assessments of disease activity using the BVAS/GPA13 and cumulative damage using the Vasculitis Damage Index (VDI).14 Remission was defined as BVAS/GPA=0, and active disease as BVAS/GPA≥1.2 Patient and physician global assessments (PtGA and PhGA, respectively) were also recorded on a 0–100 scale. All patients completed the validated Spanish versions of the self-administered CRS questionnaire (SNOT-22)15 and the AAV-PRO. Physicians were blinded to SNOT-22 and AAV-PRO when assessing disease activity.
Items of the SNOT-22 are scored from 0 (no problem) to 5 (problem as bad as it can be), yielding a total score ranging from 0 to 110. The questionnaire comprises five subdomains with different score ranges, rhinologic (0–30), extranasal rhinologic (0–15), ear and face symptoms (0–25), psychological dysfunction (0–35), and sleep dysfunction (0–25), with higher scores indicating a greater symptom burden.16 The minimal clinically important difference (MCID) in patients with CRS is 8 for the total score.7,9 The AAV-PRO, in contrast, comprises six domains (i.e., organ specific symptoms, systemic symptoms, treatment side-effects, social and emotional impact, concerns about the future, and physical function) reported as values ranging from 0 to 100, with higher scores reflecting greater symptom intensity.10 Permission and licenses to use the certified Spanish translations of the SNOT-2215 and the AAV-PRO were obtained from the original authors and Oxford University, respectively.
On the same day as the rheumatologic assessment, a comprehensive otorhinolaryngological examination was performed. Nasal endoscopy was conducted using a 4mm, 30° rigid lens to evaluate the internal anatomy. The assessment included the mucosa (hydration, coloration, friability, and presence of blood remnants, synechiae, crusts, or ulcers), nasal turbinates and septum (for deviations or perforations), nasopharynx (mucosal condition and mucus presence), and the torus tubarius (mucosal state, mucus amount, cushions, and patency).
A single radiologist performed the tomographic evaluation. Paranasal sinus CT scans were acquired with a General Electric Lightspeed VCT 64-slice scanner using 0.5cm slices, reconstructed in axial, coronal, and sagittal planes with bone and soft tissue windows. The following findings were assessed: sinus mucosal thickening, paranasal granulomas, irregular scalloping of the internal walls, neo-osteogenesis, sclerotic bone thickening, septal perforation, paranasal bone destruction, calcifications in the paranasal sinuses and greater wings of the sphenoid, and complete obliteration of one or more paranasal sinuses.
Statistical analysisDescriptive statistics included frequencies and percentages for categorical variables, and means with standard deviations or medians with interquartile ranges (IQR) for continuous variables, as appropriate. Normality was assessed using the Shapiro–Wilk test. Correlation analyses were conducted using Pearson's correlation coefficient (r) or Spearman's rank correlation coefficient (ρ), depending on the type and distribution of the variables. The Bonferroni correction was applied to adjust for multiple comparisons. Correlation coefficients were interpreted as follows: 0.00–0.10 (negligible), 0.10–0.39 (weak), 0.40–0.69 (moderate), 0.70–0.89 (strong), and 0.90–1.00 (very strong).17 Univariable and multivariable logistic regression analyses were performed to assess differences between patients in remission vs. active disease, and a multivariable linear regression analysis with sensitivity checks was performed to examine factors independently associated with the SNOT-22 total score in the study cohort. A p-value ≤0.05 was considered statistically significant.
All statistical analyses were performed using STATA version 14.0 (StataCorp; College Station, TX, USA).
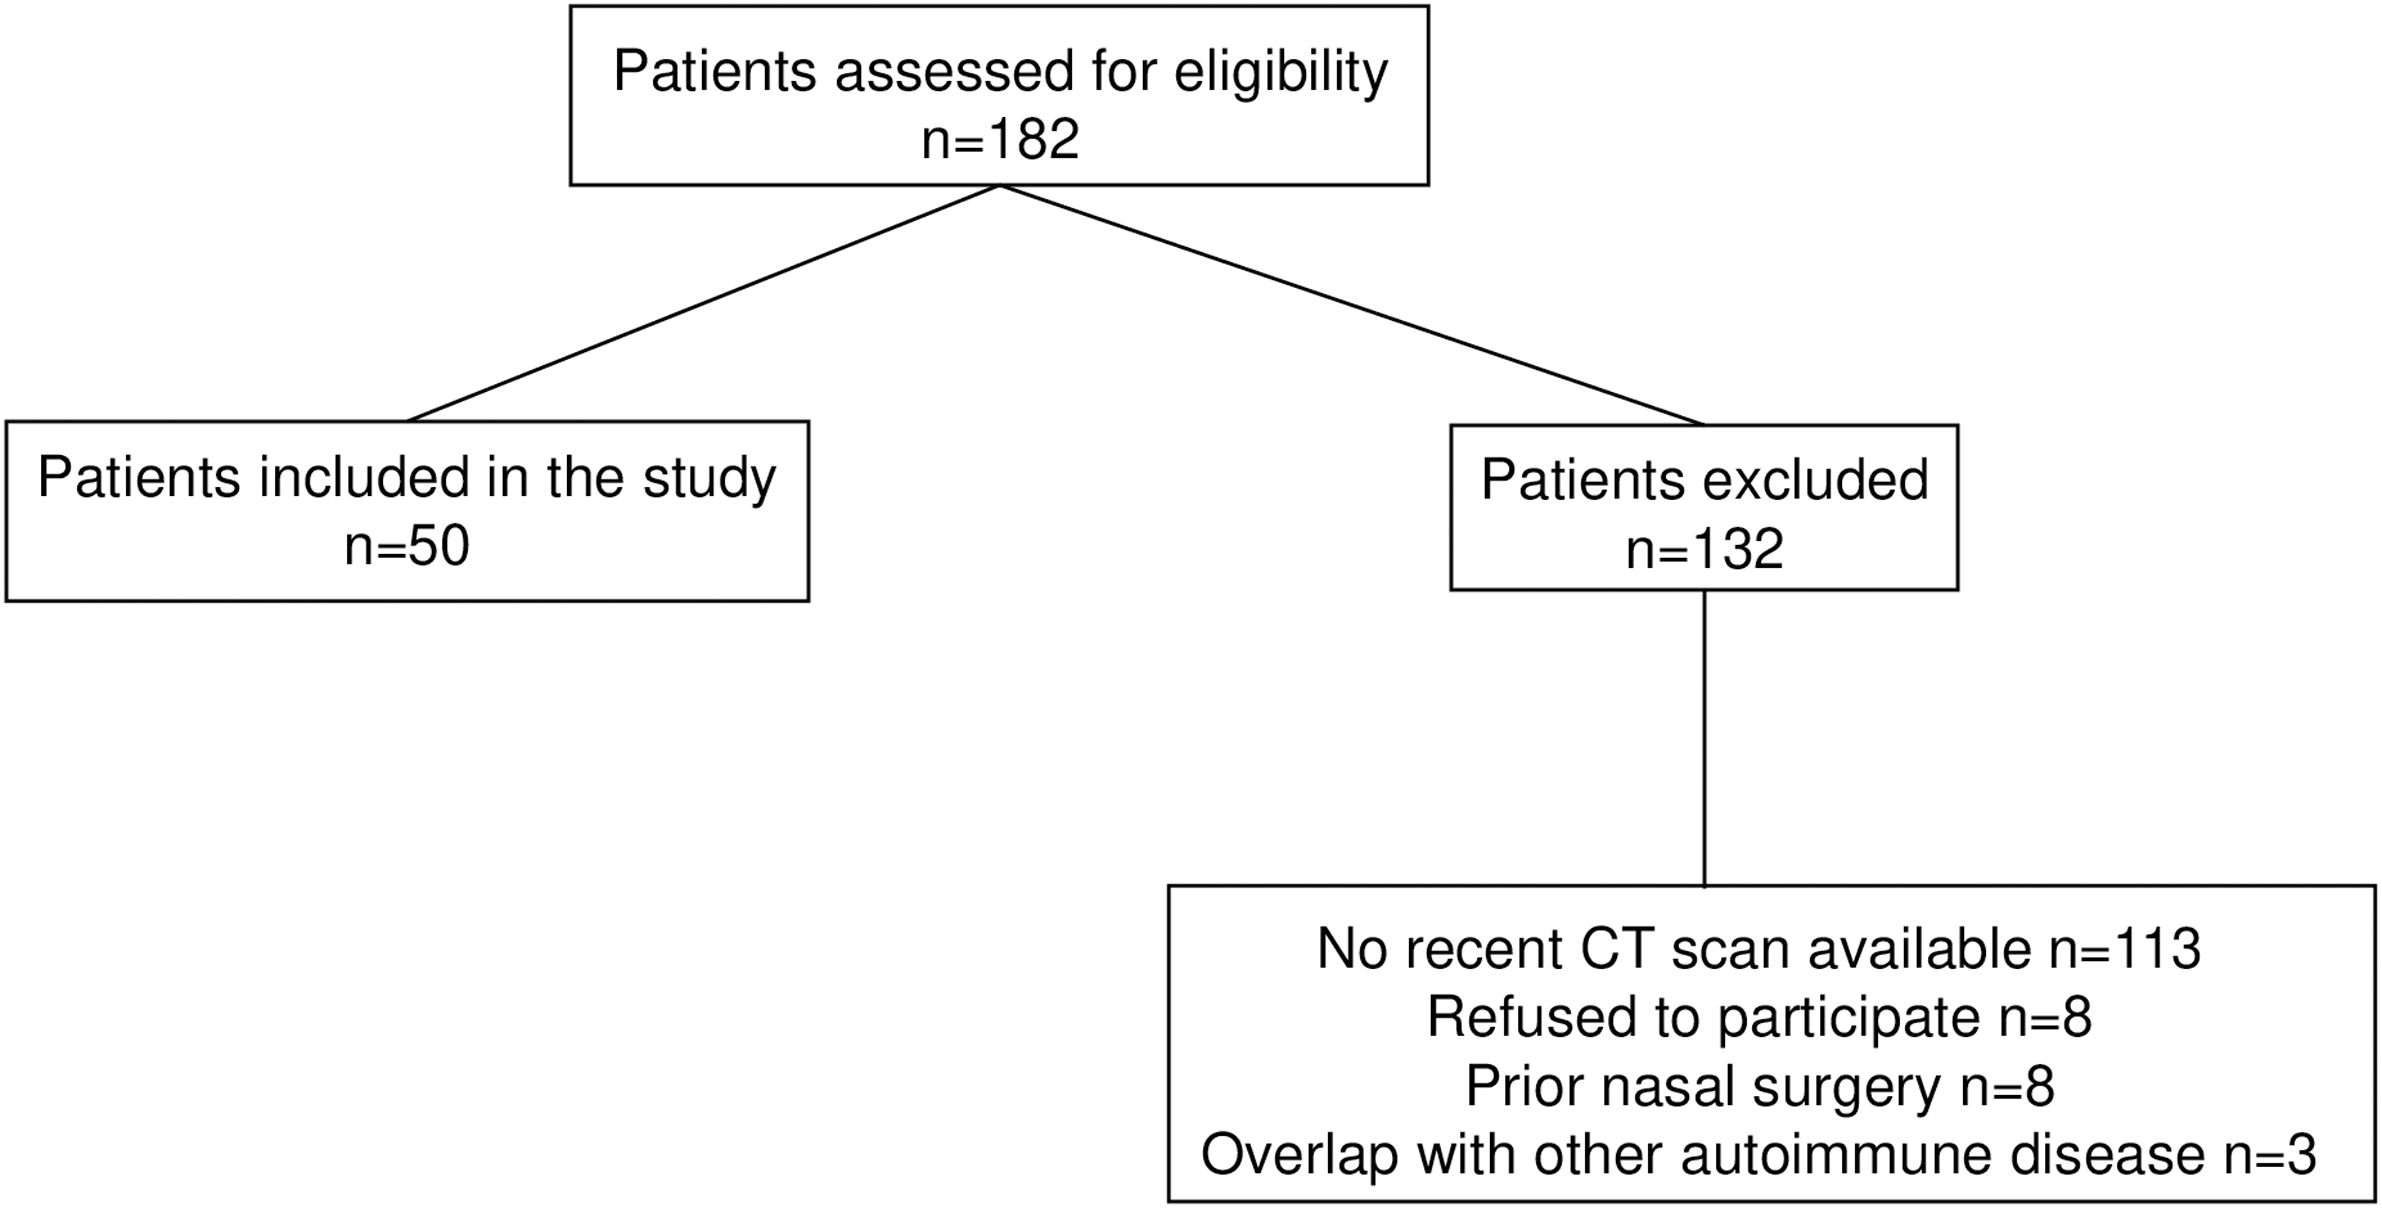
ResultsDemographic and clinical characteristicsOf the 182 patients assessed for eligibility, 50 met the inclusion criteria and were included in the study (Fig. 1 shows the inclusion flowchart). Most patients (64%) were women, with a median age of 49.5 years (IQR 40–61) at the time of evaluation and a median disease duration of 88.5 months (IQR 34–148). The majority of patients (86%) were PR3-ANCA positive at diagnosis.

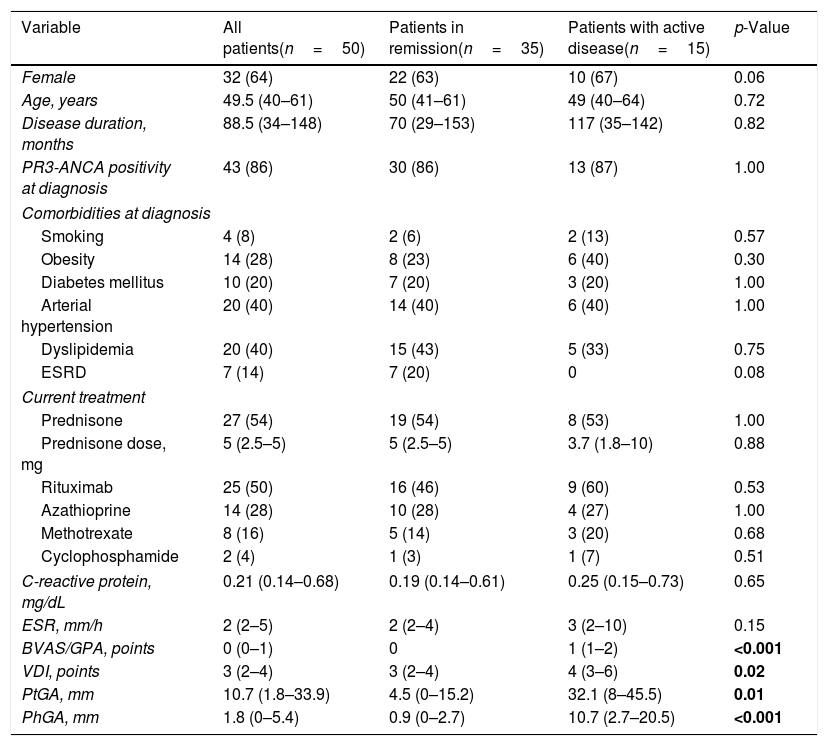
The most common comorbidities were arterial hypertension and dyslipidemia, present in 40% of patients. More than half of the cohort (54%) were receiving prednisone at the time of evaluation. Clinical and demographic characteristics are summarized in Table 1.
Demographic and clinical characteristics of the study cohort.
| Variable | All patients(n=50) | Patients in remission(n=35) | Patients with active disease(n=15) | p-Value |
|---|---|---|---|---|
| Female | 32 (64) | 22 (63) | 10 (67) | 0.06 |
| Age, years | 49.5 (40–61) | 50 (41–61) | 49 (40–64) | 0.72 |
| Disease duration, months | 88.5 (34–148) | 70 (29–153) | 117 (35–142) | 0.82 |
| PR3-ANCA positivity at diagnosis | 43 (86) | 30 (86) | 13 (87) | 1.00 |
| Comorbidities at diagnosis | ||||
| Smoking | 4 (8) | 2 (6) | 2 (13) | 0.57 |
| Obesity | 14 (28) | 8 (23) | 6 (40) | 0.30 |
| Diabetes mellitus | 10 (20) | 7 (20) | 3 (20) | 1.00 |
| Arterial hypertension | 20 (40) | 14 (40) | 6 (40) | 1.00 |
| Dyslipidemia | 20 (40) | 15 (43) | 5 (33) | 0.75 |
| ESRD | 7 (14) | 7 (20) | 0 | 0.08 |
| Current treatment | ||||
| Prednisone | 27 (54) | 19 (54) | 8 (53) | 1.00 |
| Prednisone dose, mg | 5 (2.5–5) | 5 (2.5–5) | 3.7 (1.8–10) | 0.88 |
| Rituximab | 25 (50) | 16 (46) | 9 (60) | 0.53 |
| Azathioprine | 14 (28) | 10 (28) | 4 (27) | 1.00 |
| Methotrexate | 8 (16) | 5 (14) | 3 (20) | 0.68 |
| Cyclophosphamide | 2 (4) | 1 (3) | 1 (7) | 0.51 |
| C-reactive protein, mg/dL | 0.21 (0.14–0.68) | 0.19 (0.14–0.61) | 0.25 (0.15–0.73) | 0.65 |
| ESR, mm/h | 2 (2–5) | 2 (2–4) | 3 (2–10) | 0.15 |
| BVAS/GPA, points | 0 (0–1) | 0 | 1 (1–2) | <0.001 |
| VDI, points | 3 (2–4) | 3 (2–4) | 4 (3–6) | 0.02 |
| PtGA, mm | 10.7 (1.8–33.9) | 4.5 (0–15.2) | 32.1 (8–45.5) | 0.01 |
| PhGA, mm | 1.8 (0–5.4) | 0.9 (0–2.7) | 10.7 (2.7–20.5) | <0.001 |
Values are reported as n (%) or median (IQR). p-Values in bold represent statistically significant differences between groups.
Abbreviations: PR3, proteinase 3 ANCA; ESRD, end-stage renal disease; ESR, erythrocyte sedimentation rate; BVAS/GPA, Birmingham Vasculitis Activity Score for granulomatosis with polyangiitis; VDI, Vasculitis Damage Index; PtGA, patient global assessment; PhGA, physician global assessment.
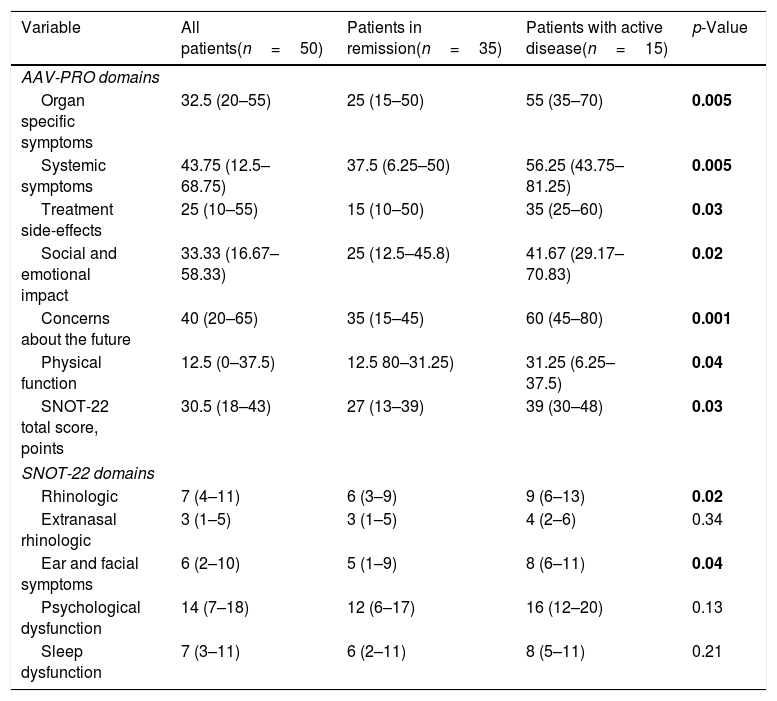
Ten patients (20%) scored positive in the ENT domain of the BVAS/GPA score (i.e., bloody nasal discharge, nasal crusting, ulcer, sinus involvement). The median VDI was 3 points (IQR 2–4), the PhGA was 1.8mm (IQR 0–5.4), and the PtGA was 10.7mm (IQR 1.8–33.9) (Table 1). Within the AAV-PRO, the highest scores were observed in the systemic symptoms and concerns about the future domains, as shown in Table 2.
Patient-reported outcome measures (PROMs).
| Variable | All patients(n=50) | Patients in remission(n=35) | Patients with active disease(n=15) | p-Value |
|---|---|---|---|---|
| AAV-PRO domains | ||||
| Organ specific symptoms | 32.5 (20–55) | 25 (15–50) | 55 (35–70) | 0.005 |
| Systemic symptoms | 43.75 (12.5–68.75) | 37.5 (6.25–50) | 56.25 (43.75–81.25) | 0.005 |
| Treatment side-effects | 25 (10–55) | 15 (10–50) | 35 (25–60) | 0.03 |
| Social and emotional impact | 33.33 (16.67–58.33) | 25 (12.5–45.8) | 41.67 (29.17–70.83) | 0.02 |
| Concerns about the future | 40 (20–65) | 35 (15–45) | 60 (45–80) | 0.001 |
| Physical function | 12.5 (0–37.5) | 12.5 80–31.25) | 31.25 (6.25–37.5) | 0.04 |
| SNOT-22 total score, points | 30.5 (18–43) | 27 (13–39) | 39 (30–48) | 0.03 |
| SNOT-22 domains | ||||
| Rhinologic | 7 (4–11) | 6 (3–9) | 9 (6–13) | 0.02 |
| Extranasal rhinologic | 3 (1–5) | 3 (1–5) | 4 (2–6) | 0.34 |
| Ear and facial symptoms | 6 (2–10) | 5 (1–9) | 8 (6–11) | 0.04 |
| Psychological dysfunction | 14 (7–18) | 12 (6–17) | 16 (12–20) | 0.13 |
| Sleep dysfunction | 7 (3–11) | 6 (2–11) | 8 (5–11) | 0.21 |
Values are reported as n (%) or median (IQR). p-Values in bold represent statistically significant differences between groups.
Abbreviations: AAV-PRO, ANCA-associated vasculitis patient-reported outcomes; SNOT-22, Sino-Nasal Outcome Test-22.
At the time of evaluation, 35 patients (70%) were in remission and 15 (30%) had active disease. Patients with active disease had higher VDI scores (4 points [IQR 3–6] vs. 3 points [IQR 2–4], p=0.02), worse PtGA (32.1 [IQR 8–45.5] vs. 4.5 [IQR 0–15.2], p=0.01) and PhGA (10.7 [IQR 2.7–20.5] vs. 0.9 [IQR 0–2.7], p<0.001) (Table 1), higher values across all AAV-PRO domains, a higher SNOT-22 total score (39 points [IQR 30–48] vs. 27 points [IQR 13–39], p=0.03), and higher scores in the rhinologic and ear and facial symptom domains of the SNOT-22 (Table 2). In the multivariable analysis, only the PhGA (OR=1.14; 95% CI 1.03–1.25; p=0.01) and the concerns about the future domain of the AAV-PRO (OR=1.10; 95% CI 1.03–1.17; p=0.004) remained independently associated with disease activity.
Self-perceived sinonasal symptoms, ENT endoscopic evaluation, and radiographic findingsThe median total SNOT-22 score was 30.5 points (IQR 18–43). Forty-seven patients (94%) had a SNOT-22 total score greater than 8 points. The five most troublesome symptoms reported were fatigue in 20 patients (40%), difficulty falling asleep in 19 (38%), nasal blockage in 18 (36%), ear fullness in 17 (34%), and waking up tired in 16 (32%). The median raw scores by domain were: rhinologic, 7 (IQR 4–11); extranasal rhinologic, 3 (IQR 1–5); ear and facial symptoms, 6 (IQR 2–10); psychological dysfunction, 14 (IQR 7–18); and sleep dysfunction, 7 (IQR 3–11). Considering each domain individually, 19 patients (38%) in the rhinologic domain, 2 patients (4%) in the extranasal rhinologic domain, 16 patients (32%) in the ear and facial symptoms domain, 33 patients (66%) in the psychological dysfunction domain, and 21 patients (42%) in the sleep dysfunction domain had scores greater than 8 points. There was no significant difference in the median total SNOT-22 score between patients who were evaluated as positive in the ENT domains of the BVAS/GPA and those who were evaluated as negative [36 (IQR 27–43) vs. 29 (IQR 16–42.5), p=0.19].
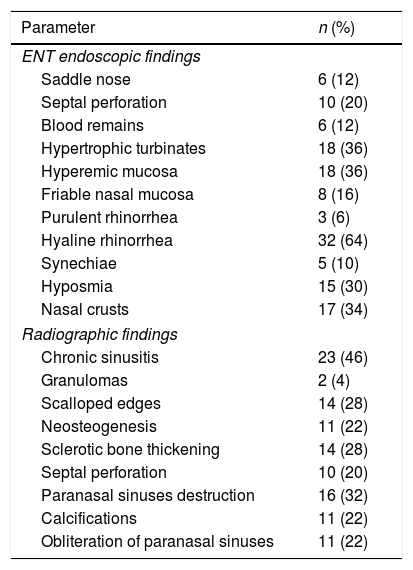
The most frequent ENT findings were hypertrophic turbinates and hyperemic mucosa, present in 18 patients (36%); hyaline rhinorrhea, in 32 (64%); hyposmia, in 15 (30%); and nasal crusts, in 17 (34%). Septal perforation was present in 10 (20%) and ranged from 0.5 to 3.0cm. The most common radiographic findings were chronic sinusitis (sinus mucosal thickening) in 23 patients (46%), paranasal sinus destruction in 16 (32%), and scalloped edges with sclerotic bone thickening in 14 (28%). These results are summarized in Table 3.
ENT and radiographic findings (n=50).
| Parameter | n (%) |
|---|---|
| ENT endoscopic findings | |
| Saddle nose | 6 (12) |
| Septal perforation | 10 (20) |
| Blood remains | 6 (12) |
| Hypertrophic turbinates | 18 (36) |
| Hyperemic mucosa | 18 (36) |
| Friable nasal mucosa | 8 (16) |
| Purulent rhinorrhea | 3 (6) |
| Hyaline rhinorrhea | 32 (64) |
| Synechiae | 5 (10) |
| Hyposmia | 15 (30) |
| Nasal crusts | 17 (34) |
| Radiographic findings | |
| Chronic sinusitis | 23 (46) |
| Granulomas | 2 (4) |
| Scalloped edges | 14 (28) |
| Neosteogenesis | 11 (22) |
| Sclerotic bone thickening | 14 (28) |
| Septal perforation | 10 (20) |
| Paranasal sinuses destruction | 16 (32) |
| Calcifications | 11 (22) |
| Obliteration of paranasal sinuses | 11 (22) |
Abbreviations: ENT, ear, nose, and throat.
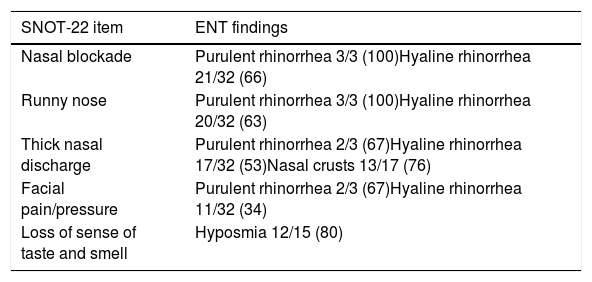
The closest correspondences were observed between the nasal blockade item of the SNOT-22 and the ENT finding of purulent rhinorrhea, as well as with the presence of granulomas and obliteration of the paranasal sinuses on CT scans. The runny nose item of the SNOT-22 also corresponded with the finding of purulent rhinorrhea on ENT examination, and the loss of sense of smell item corresponded with hyposmia on ENT evaluation. Additional examples of concordances and discrepancies between self-reported sinonasal symptoms in the SNOT-22 and the corresponding ENT and radiographic findings are presented in Table 4.
Coincidences and discrepancies between the self-perceived sinonasal symptoms, endoscopic ENT and radiographic findings.
| SNOT-22 item | ENT findings |
|---|---|
| Nasal blockade | Purulent rhinorrhea 3/3 (100)Hyaline rhinorrhea 21/32 (66) |
| Runny nose | Purulent rhinorrhea 3/3 (100)Hyaline rhinorrhea 20/32 (63) |
| Thick nasal discharge | Purulent rhinorrhea 2/3 (67)Hyaline rhinorrhea 17/32 (53)Nasal crusts 13/17 (76) |
| Facial pain/pressure | Purulent rhinorrhea 2/3 (67)Hyaline rhinorrhea 11/32 (34) |
| Loss of sense of taste and smell | Hyposmia 12/15 (80) |
| SNOT-22 item | Radiographic findings |
|---|---|
| Nasal blockade | Chronic sinusitis 17/23 (74)Granulomas 2/2 (100)Obliteration of paranasal sinuses 9/11 (82) |
| Thick nasal discharge | Chronic sinusitis 14/23 (61)Obliteration of paranasal sinuses 6/11 (55) |
| Facial pain/pressure | Chronic sinusitis 10/23 (43)Obliteration of paranasal sinuses 5/11 (45) |
Data are presented as the number of patients with a SNOT-22 item score ≥1 divided by the number of patients with the corresponding ENT or radiographic finding, with percentages shown in brackets.
Abbreviations: ENT, ear, nose, and throat; SNOT-22, Sino-Nasal Outcome Test-22.
The variables analyzed for correlation with the SNOT-22 total score included age, disease duration, prednisone dose, ESR, CRP, PtGA, PhGA, VDI score, BVAS/GPA score, and the individual subdomains of the AAV-PRO instrument.
The following domains of the AAV-PRO showed moderate to strong significant correlations with the SNOT-22 after Bonferroni correction: treatment side effects (r=0.71, 95% CI 0.53–0.82, p<0.001), organ specific symptoms (r=0.70, 95% CI 0.52–0.81, p<0.001), social and emotional impact (r=0.63, 95% CI 0.43–0.77, p<0.001), systemic symptoms (r=0.62, 95% CI 0.41–0.76, p<0.001), physical function (r=0.58, 95% CI 0.36–0.73, p<0.001), and concerns about the future (r=0.54, 95% CI 0.31–0.71, p<0.001). Moreover, the global assessments PtGA (r=0.55, 95% CI 0.31–0.72, p<0.001) and PhGA (r=0.48, 95% CI 0.23–0.66, p<0.001), also showed significant positive correlations. No significant correlations were found with prednisone dose, damage, disease activity, disease duration, or acute-phase reactants.
In the multivariable linear regression analysis, the organic symptoms (β=0.31, 95% CI 0.12–0.49; p=0.001) and treatment side effects (β=0.29, 95% CI 0.09–0.49; p=0.006) domains of the AAV-PRO remained significantly associated, suggesting that higher values in these domains were linked to a greater sinonasal symptom burden.
DiscussionIn this study, we evaluated self-perceived sinonasal symptoms using the SNOT-22 questionnaire together with clinical variables and examined discrepancies between patient-reported symptoms, ENT examination findings, and sinonasal radiographic abnormalities in patients with GPA. Self-reported sinonasal symptoms correlated with other PROMs, including the AAV-PRO domains and the PtGA, but not with measures of disease activity, likely because most patients were in remission at the time of evaluation. Discrepancies between specific SNOT-22 items and objective ENT and radiologic findings highlight the gap between patient- and clinician-reported disease assessment and underscore the importance of incorporating PROMs in the evaluation of GPA patients, even when they are clinically in remission.
Self-perceived sinonasal symptoms are common in GPA and contribute substantially to patient-reported burden, but only partially align with objective assessments. Although normative SNOT-22 values are not available, a study of 1000 healthy European individuals reported a mean score of 20.2±19.4.18 In the present cohort, the median SNOT-22 score was 30.5, comparable to values reported in AAV patients with ENT involvement in cross-sectional and longitudinal studies.6,9 In contrast to previous studies,6,9 no correlation was observed between SNOT-22 and BVAS/GPA, which may be explained by longstanding disease, outpatient recruitment, remission status, low prevalence of active ENT involvement (20%), and single time-point assessment.
PROMs appear more sensitive to chronic, day-to-day symptom burden and functional impact than BVAS or VDI, which primarily capture clinician-assessed disease activity and cumulative organ damage. Patients may experience substantial ongoing symptoms despite low BVAS or stable VDI, and PROMs help quantify this residual morbidity. Objective outcome measures reflect distinct dimensions of disease and do not always correlate with symptoms. This dissociation mirrors findings in CRS, where PROMs such as SNOT-22 correlate weakly or inconsistently with endoscopic and CT findings, underscoring the need to interpret symptoms alongside clinician-reported activity and imaging.19,20
Assessing ENT disease activity in GPA remains challenging due to the lack of objective markers that specifically reflect GPA-related activity or damage, as well as the variability of manifestations according to disease stage (e.g., crusting, granulation, and necrosis are more common in the active phase, whereas saddle nose deformity, turbinate loss, and septal perforation are more frequent in later stages of the disease).21 GPA-specific instruments such as the ENT/GPA Disease Activity Score (ENT/GPA DAS) and ENTAS-2 incorporate clinical signs, symptoms, endoscopy, and diagnostic tests and have demonstrated acceptable reliability for distinguishing active disease from damage, as well as greater sensitivity but lower specificity than BVAS ENT items.22,23 However, these instruments were not designed to quantify patient-perceived symptom severity and should therefore be considered complementary to PROMs such as the SNOT-22 and the AAV-PRO.
The most frequent radiographic findings were chronic sinusitis, scalloped edges, sclerotic bone thickening, and paranasal sinus destruction, consistent with previous reports.4,24,25 Radiographic septal perforation was present in 20% of patients, lower than the 60% reported in systematic reviews,24 but correlated well with endoscopic findings. CT imaging captures two related but distinct domains: mucosal disease, reflecting current inflammation but sometimes difficult to distinguish from chronic sinusitis, and bone changes, particularly osteitis and osseous destruction, reflecting cumulative damage. Longitudinal studies have shown that baseline mucosal disease independently predicts later osteitis progression over approximately five years, indicating that ongoing inflammation drives structural damage even when symptoms fluctuate, similar to CRS.26,27 CT-based methods, such as the mean maxillary and sphenoid diameters normalized to landmark distances and the Global Osteitis Scoring Scale, have been designed to capture, classify, and quantify time-dependent changes in GPA-related paranasal osteitis.28 Certain CT features, such as nasal strands, help distinguish GPA from primary CRS.29 Because structural damage may be clinically silent, reliance on symptoms alone risks underestimating progressive disease.25,29
Endoscopic findings most frequently included hyaline rhinorrhea, hypertrophic turbinates, and hyperemic mucosa, whereas nasal crusts were less common. Discrepancies were observed between rhinologic and ear/facial SNOT-22 items and endoscopic findings. The five most troublesome symptoms reported by patients did not cluster within a single domain. The association between symptoms and endoscopy in GPA is modest: symptoms tend to increase with active crusting, ulceration, and purulence, but endoscopy also detects subclinical inflammation and irreversible damage, such as septal perforation or saddle-nose deformity, which may not correlate with symptom severity. These findings parallel CRS, where SNOT-22 often shows weak or no correlation with endoscopic or CT scores at a single time point, and any correlations are typically small to moderate and domain-specific.30
These findings support a practical clinical approach in GPA: (1) use PROMs (e.g., SNOT-22 or AAV-PRO organ-specific items) to quantify patient-perceived impact; (2) combine them with standardized ENT assessments (nasal endoscopy, ENT/GPA DAS, or ENTAS-2) at regular follow-up visits to distinguish active inflammation from permanent damage; and (3) perform serial CT imaging when structural progression is suspected or baseline mucosal disease is extensive. This integrated approach is essential, as surgery does not appear to halt osteitis progression and treatment decisions regarding immunosuppression should rely on combined evidence from symptoms, endoscopic activity, and imaging.27,28
Most evidence regarding discordance between PROMs and objective measures derives from CRS rather than GPA-specific cohorts. Although the direction of this discordance is likely similar, effect sizes in GPA remain insufficiently explored. Sinonasal manifestations associated with autoimmune disease may be atypical, recurrent, and treatment-resistant, with more severe subjective and objective findings than CRS of other etiologies.31 Moreover, endoscopic and CT scores measure different constructs, and cross-sectional correlations cannot capture longitudinal relationships, such as baseline mucosal disease predicting later osteitis.19,27
Study limitations include the cross-sectional design, small sample size, predominance of patients in remission with long disease duration, and single tertiary-center setting, limiting generalizability. The low prevalence of active ENT disease raises the possibility of type II error. Control groups were not included, and potential confounders such as nasal treatments, Staphylococcus aureus colonization, and infection were not assessed. CT scans were performed 0–48 months before clinical evaluation, potentially biasing symptom-imaging agreement. ENT/GPA DAS and ENTAS-2 were not applied. Nevertheless, the use of validated PROMs combined with standardized endoscopic, rheumatologic, and imaging assessments strengthens internal validity, and the findings should be confirmed in larger prospective studies.
ConclusionsSelf-reported sinonasal symptoms were more closely related to PROMs than to measures of disease activity or damage. Discrepancies between specific SNOT-22 items and objective ENT or radiologic findings underscore the gap between patient- and clinician-reported perceptions of disease. Future GPA-specific longitudinal studies integrating PROMs, standardized ENT assessments, and serial CT imaging may help identify symptom patterns that best predict damage accrual and define clinically meaningful change over time.
CRediT authorship contribution statementAHA, EMN, MIGS, and MTSG participated in the conception and design of the study; AHA, EMN, MIGS, EJT, MTSG, and ESO participated in the acquisition, analysis, and interpretation of the data; AHA, EMN, MIGS, MTSG, EJT, and ESO participated in the revision of the draft and intellectual content and approved the final version of the manuscript.
FundingThe present research did not receive any specific funding from public, commercial, or not-for-profit agencies.
Conflict of interestThe authors report there are no competing interests to declare.
Data availabilityThe data supporting this study is available upon reasonable request to the corresponding author.




