



To determine the incidence rate of neoplasms among the GPSD population and compare it with the Spanish general population, as well as to identify its role as a paraneoplastic syndrome in terms of temporal criteria.
MethodsAn observational, single-center, longitudinal study on GPSD patients (2015–2023) was conducted. Demographic, clinical variables and neoplasms found after GPSD diagnosis (excluding metastatic events or recurrences and non-melanoma skin cancer) were collected. In order to adjust by age and sex, we performed an indirect standardization method and calculated the standardized neoplasm ratio (SNR) and standardized incidence ratio (SIR).
ResultsAmong 334 patients, 16 (4.8%) developed neoplasms, with 11 diagnosed within the first two years (7 within the first year).
The SNR was 4.03 (CI 95% 1.53–6.53) in women and 2.37 (CI 95% 0.47–4.27) in men. Considering the neoplasms diagnosed in the two first years, the SNR were 2.42 (CI 95% 0.484–4.356) in women and 2.11 (CI 95% 0.258–3.868) in men.
ConclusionWe observed a high incidence rate of neoplasms in our women GPSD patients. While no statistical significance was reached in men or in cases beyond two years post-diagnosis, a tendency toward higher rates was noted. These findings emphasize the need for further research on the potential oncologic implications of GPSD.
Determinar la tasa de incidencia de neoplasias en la población con PMR-ACG y compararla con la población general española, así como identificar su posible papel como síndrome paraneoplásico según criterios temporales.
MétodosSe llevó a cabo un estudio observacional, unicéntrico y longitudinal en pacientes con PMR-ACG (2015-2023). Se recogieron variables demográficas y clínicas, y las neoplasias detectadas tras el diagnóstico de PMR-ACG (excluyendo eventos metastásicos o recidivas y el cáncer cutáneo no melanoma). Para ajustar por edad y sexo, se aplicó un método de estandarización indirecta y se calcularon la razón de neoplasias estandarizada (RNE) y la razón de incidencia estandarizada (RIE).
ResultadosDe 334 pacientes, 16 (4,8%) desarrollaron neoplasias; 11 se diagnosticaron en los dos primeros años (7 en el primer año). La RNE fue de 4,03 (IC95%: 1,53-6,53) en mujeres y de 2,37 (IC95%: 0,47-4,27) en hombres. Considerando las neoplasias diagnosticadas en los dos primeros años, las RNE fueron de 2,42 (IC95%: 0,484-4,356) en mujeres y de 2,11 (IC95%: 0,258-3,868) en hombres.
ConclusiónObservamos una elevada tasa de incidencia de neoplasias en nuestras pacientes mujeres con PMR-ACG. Aunque no se alcanzó significación estadística en los varones ni en los casos más allá de los dos años tras el diagnóstico, se observó una tendencia hacia tasas más altas de neoplasias. Estos hallazgos subrayan la necesidad de investigar más a fondo las posibles implicaciones oncológicas del espectro PMR-ACG.
Polymyalgia rheumatica (PMR) and giant cell arteritis (GCA) are two closely related diseases that frequently coexist. Although their pathophysiology is not fully understood, they are considered rheumatic diseases with similar characteristics, such as onset in patients over 50 years old, predominance in females, marked inflammation with elevated acute-phase reactants, and treatment with glucocorticoids and even interleukin-6 receptor inhibitors.1,2 In fact, there is a growing tendency that views both conditions as part of a single disease spectrum, constituting the giant cell arteritis-polymyalgia rheumatica spectrum disease (GPSD).3
Across Europe, GCA and PMR are frequent in older adults. In Spain, recent nationwide data report a GCA incidence of 7.42 (95% CI, 6.57–8.27) cases per 100,000 persons older than 50.4
The dysregulation of the immune system inherent in rheumatic diseases has been associated with an increased incidence of neoplasms.5 Diseases such as rheumatoid arthritis,6 systemic lupus erythematosus,7 or dermatomyositis8 have shown a consistent association with cancer development. The data on the GPSD are varied and contradictory, with studies showing both positive9–11 and negative12–14 associations. However, malignancies can mimic GPSD (particularly PMR) and must be ruled out in selected cases such as atypical presentation, inadequate response to therapy or refractory course.15
Specific characteristics of the GPSD, such as its partially unknown pathophysiology, onset in elderly individuals, and variability in chronicity and maintenance of a pro-inflammatory state, make establishing a causal relationship between GPSD and cancer even more challenging.
The term paraneoplastic syndrome describes symptoms derived from a neoplasm, not caused by direct tissue invasion, but rather by substances released by tumor cells.16 Paraneoplastic syndromes are typically thought to precede the onset of neoplasia by around two years,17 with cancer being diagnosed mainly within the first year after the clinical onset. The fact that studies have found that patients develop neoplasms predominantly within the first year following GPSD diagnosis has led to speculation that GPSD may be a paraneoplastic syndrome. PMR has been described as a manifestation of an underlying neoplasm that improves with treatment.18 However, a recent review found insufficient evidence to categorize PMR as a true paraneoplastic syndrome.19
Our study aims to describe the relationship between the GPSD and cancer by calculating the crude incidence ratio of neoplasms in our population and comparing it with the Spanish population. Additionally, we aim to interpret its potential role as a paraneoplastic syndrome, particularly regarding the time criterion (cancer incidence within two years of diagnosis).
MethodsDesignThis is a single-center, retrospective observational study with longitudinal follow-up of GPSD patients diagnosed and monitored at our hospital between January 1, 2015, and December 31, 2023. Data was obtained through a review of each patient's electronic medical record. Patient anonymity was preserved during data collection and recording to ensure confidentiality and privacy. This study was approved by the Ethics Committee of Hospital Universitari i Politécnic La Fe and was conducted in accordance with ethical principles and recommendations from the Declaration of Helsinki.
Patients were included if diagnosed based on clinical (compatible symptoms), laboratory (elevated CRP and ESR), complementary tests (vascular ultrasound, PET-CT, or temporal artery biopsy), and/or clinical judgment. Patients diagnosed with another rheumatic disease during follow-up were excluded. Patients were followed from diagnosis to the development of a neoplasm, death, or end of the study. The different neoplasms diagnosed after the disease were listed, as well as their type and time of appearance, excluding recurrences and non-melanoma skin cancers. Clinical and demographic variables were collected. Patients were classified into polymyalgic, ischemic, or cranial phenotype according to the predominant clinical presentation at the time of diagnosis.
Statistical analysisA descriptive analysis of the sample was conducted, using the mean and standard deviation (SD) or median and interquartile range (IQR) for continuous variables and absolute frequency and percentage for categorical variables. A bivariate analysis using Chi-square and Student's t-tests was performed to check for differences between patients who developed neoplasms and those who did not. A Poisson model, adjusting for clinical and demographic variables, was used to study risk factors for neoplasm incidence.
The crude incidence rate of neoplasms (CIRN) per 100,000 person-years (py) was calculated. An indirect age- and sex-adjusted rate method was used to calculate the standardized neoplasm ratio (SNR) and the standardized rate of our population. We obtained the crude cancer incidence rate for Spain from the Global Cancer Observatory (GLOBOCAN), conducted by the International Agency for Research on Cancer (IARC) of the World Health Organization (WHO). The statistical analysis was performed using STATA V.13.1 (StataCorp). Statistical significance was set at p<0.05.
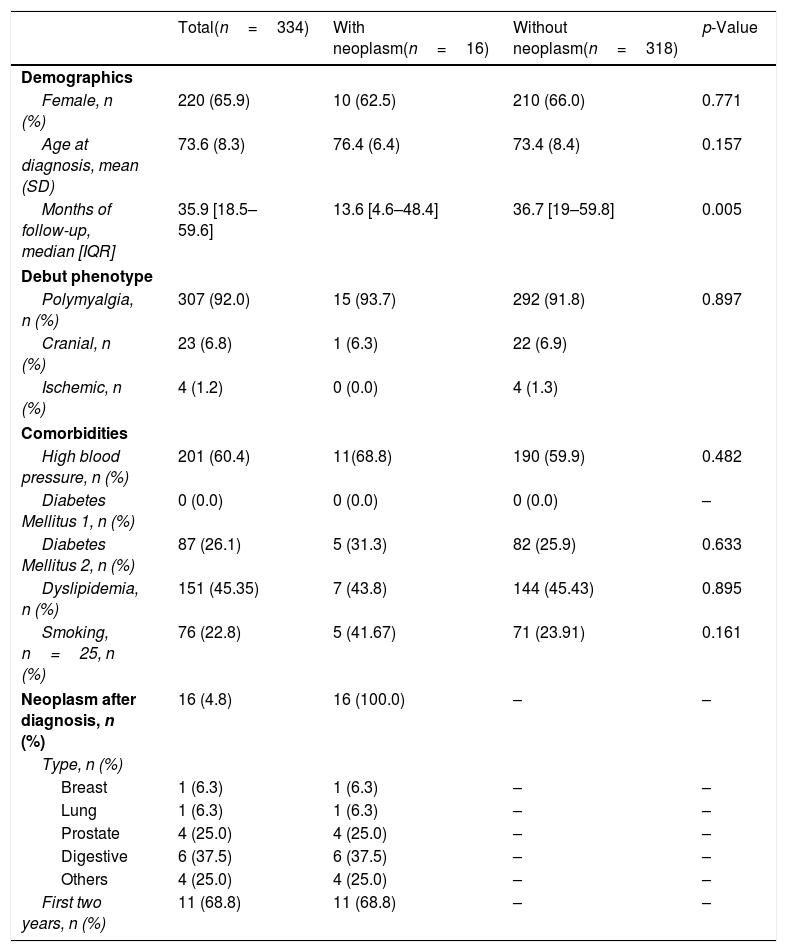
ResultsPatient characteristicsA total of 334 patients were included. Females predominated (65.9%), and the mean age at diagnosis was 73.6 years (±8.3). PMR phenotype was present in 92% of patients at diagnosis (Table 1) and of the remaining 8% of patients, 88.5% met the ACR/EULAR 2022 classification criteria. Temporal artery biopsy was performed in 10 patients (60% positive), ultrasound in 24 patients (70.8% positive) and positron emission tomography-computed tomography (PET-CT) in 17 patients (41.2% positive).
Descriptive and univariate analysis of the GPSD population.
| Total(n=334) | With neoplasm(n=16) | Without neoplasm(n=318) | p-Value | |
|---|---|---|---|---|
| Demographics | ||||
| Female, n (%) | 220 (65.9) | 10 (62.5) | 210 (66.0) | 0.771 |
| Age at diagnosis, mean (SD) | 73.6 (8.3) | 76.4 (6.4) | 73.4 (8.4) | 0.157 |
| Months of follow-up, median [IQR] | 35.9 [18.5–59.6] | 13.6 [4.6–48.4] | 36.7 [19–59.8] | 0.005 |
| Debut phenotype | ||||
| Polymyalgia, n (%) | 307 (92.0) | 15 (93.7) | 292 (91.8) | 0.897 |
| Cranial, n (%) | 23 (6.8) | 1 (6.3) | 22 (6.9) | |
| Ischemic, n (%) | 4 (1.2) | 0 (0.0) | 4 (1.3) | |
| Comorbidities | ||||
| High blood pressure, n (%) | 201 (60.4) | 11(68.8) | 190 (59.9) | 0.482 |
| Diabetes Mellitus 1, n (%) | 0 (0.0) | 0 (0.0) | 0 (0.0) | – |
| Diabetes Mellitus 2, n (%) | 87 (26.1) | 5 (31.3) | 82 (25.9) | 0.633 |
| Dyslipidemia, n (%) | 151 (45.35) | 7 (43.8) | 144 (45.43) | 0.895 |
| Smoking, n=25, n (%) | 76 (22.8) | 5 (41.67) | 71 (23.91) | 0.161 |
| Neoplasm after diagnosis, n (%) | 16 (4.8) | 16 (100.0) | – | – |
| Type, n (%) | ||||
| Breast | 1 (6.3) | 1 (6.3) | – | – |
| Lung | 1 (6.3) | 1 (6.3) | – | – |
| Prostate | 4 (25.0) | 4 (25.0) | – | – |
| Digestive | 6 (37.5) | 6 (37.5) | – | – |
| Others | 4 (25.0) | 4 (25.0) | – | – |
| First two years, n (%) | 11 (68.8) | 11 (68.8) | – | – |
GPSD: giant cell arteritis-polymyalgia rheumatica spectrum disease; IQR: interquartile range; SD: standard deviation.
A total of 16 patients developed cancer after PMR or GCA diagnosis, including 6 males (37.5%) and 10 females (62.5%). The most common cancer types were digestive system cancers (37.5%) and prostate cancer (25%). All neoplasms except one occurred in patients over 70 years of age. Of patients who developed a neoplasm, 93.8% had a PMR phenotype at disease onset.
Regarding the timing of onset, we found two distinct profiles: 11 (68.8%) of the neoplasms were diagnosed within the first two years (7 during the first year). In contrast, the remaining 5 neoplasms were diagnosed more than 5 years after the diagnosis of PMR-GCA.
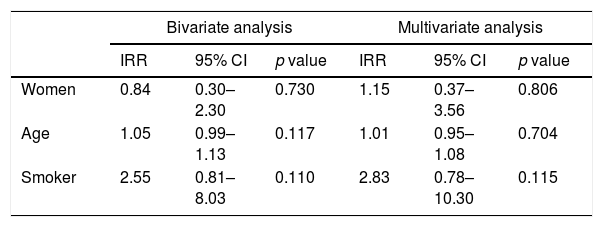
Neoplasm-associated factorsAmong the variables studied, no statistically significant differences were found between patients with and without neoplasms, except for median follow-up months (Table 1). For inspection using Poisson models (Table 2), clinically relevant variables were selected. This analysis shows that none of the studied variables were significantly associated with neoplasm development.
Poisson model (bivariate and multivariate analysis) analysis of factors associated with neoplasm development.
| Bivariate analysis | Multivariate analysis | |||||
|---|---|---|---|---|---|---|
| IRR | 95% CI | p value | IRR | 95% CI | p value | |
| Women | 0.84 | 0.30–2.30 | 0.730 | 1.15 | 0.37–3.56 | 0.806 |
| Age | 1.05 | 0.99–1.13 | 0.117 | 1.01 | 0.95–1.08 | 0.704 |
| Smoker | 2.55 | 0.81–8.03 | 0.110 | 2.83 | 0.78–10.30 | 0.115 |
95% CI: 95% confidence interval; IRR: incidence rate ratio.
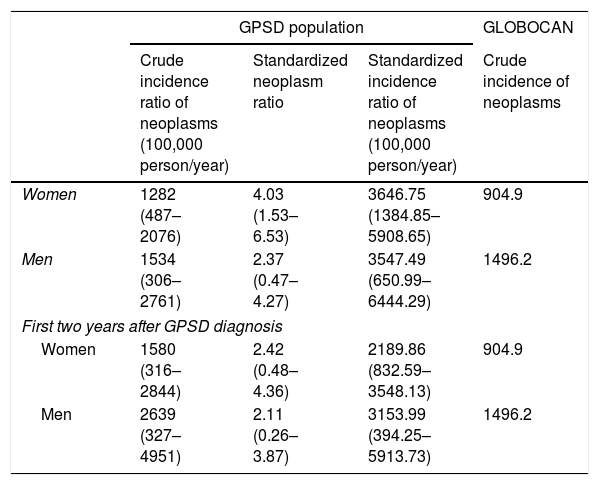
The CIRN was 1366 per 100,000py (95% CI 781–2219) when considering total follow-up and 1926 per 100,000py (95% CI 961–3445) when considering only the first two years of follow-up. The sex-specific CIRN was 1282 (95% CI 487–2076) for females and 1534 (95% CI 306–2761) for males. In the first two years after diagnosis, CIRN was 1580 (95% CI 316–2844) for females and 2639 (95% CI 327–4951) for males (Table 3).
Crude and standarized incidence rate of neoplasms (95% CI) in GPSD population and crude incidence rate of neoplasms in the general population in Spain (GLOBOCAN), stratified by sex and years after GPSD diagnosis.
| GPSD population | GLOBOCAN | |||
|---|---|---|---|---|
| Crude incidence ratio of neoplasms (100,000 person/year) | Standardized neoplasm ratio | Standardized incidence ratio of neoplasms (100,000 person/year) | Crude incidence of neoplasms | |
| Women | 1282 (487–2076) | 4.03 (1.53–6.53) | 3646.75 (1384.85–5908.65) | 904.9 |
| Men | 1534 (306–2761) | 2.37 (0.47–4.27) | 3547.49 (650.99–6444.29) | 1496.2 |
| First two years after GPSD diagnosis | ||||
| Women | 1580 (316–2844) | 2.42 (0.48–4.36) | 2189.86 (832.59–3548.13) | 904.9 |
| Men | 2639 (327–4951) | 2.11 (0.26–3.87) | 3153.99 (394.25–5913.73) | 1496.2 |
95% CI: 95% confidence interval; GLOBOCAN: Global Cancer Observatory; GPSD: giant cell arteritis-polymyalgia rheumatica spectrum disease.
After age and sex standardization, the SNR was 4.03 (95% CI 1.53–6.53) for females and 2.37 (95% CI 0.47–4.27) for males. Therefore, we found a higher SNR in the GPSD population. When considering only the first two years after diagnosis, SNR was 2.42 (95% CI 0.48–4.36) for females and 2.11 (0.26–3.87) for males (Table 3).
DiscussionWe present a study of 334 Spanish patients diagnosed within the GPSD. This is one of the first studies on cancer and GPSD in the Spanish population from a Mediterranean region, which is often underrepresented in large-scale epidemiological studies because of the higher incidence in northern European populations.
A total of 16 neoplasms were diagnosed throughout the follow-up period. When comparing our neoplasm rate with that of the Spanish population, we found a higher number of neoplasms in women diagnosed within the GPSD compared to the general population. Although statistical significance was not reached in men or in the ratios calculated after the first two years post-diagnosis, we observed a tendency indicating more neoplasms in our population compared to the general population. None of the variables selected for the bivariate analysis and Poisson model showed a statistically significant association with the incidence of neoplasms.
The most common cancer types diagnosed in our sample were related to the digestive system and prostate cancer, which is consistent with the study by Muller et al.10 that also reported an increased number of prostate cancer cases.
In our sample, we observed two peaks of cancer detection: one at the time of diagnosis and another more than five years after diagnosis. The pathophysiology of these two entities is not clearly established; however, a significant proportion of patients achieve remission without treatment or with low doses of glucocorticoids. Therefore, we might hypothesize whether long-term cancers are a result of a chronic carcinogenic inflammatory state or are simply because we are dealing with an elderly patient population in which the development of neoplasms is expected. Indeed, of the five cancers that developed beyond five years of follow-up, four occurred in patients over 80 years of age.
There are studies examining the relationship between GPSD and cancer, some focusing on the entire spectrum,9,13,14 others only on PMR,10,11,20 and others only on GCA,12,21 using registry data or cohorts from the same study centers as comparator groups. Recently, there has been a growing tendency to consider PMR and GCA as part of the same disease spectrum. Our study considers GPSD in terms of its initial phenotype, with none of the phenotypes being linked to cancer development. As expected, given its higher prevalence, 92% of patients presented a polymyalgic phenotype at disease onset, which was associated with 93.7% of cancer cases.
One of the aims of our study was to compare the incidence of neoplasms in our sample with the reference Spanish population. After adjusting for sex and age, we obtained a standardized neoplasm ratio for women of 4.03 (95% CI 1.53–6.53), showing a statistically significant higher number of neoplasms in the GPSD population compared to the Spanish population. Although statistical significance was not achieved, neoplasm rates were numerically higher in the case of men and during the first two years after diagnosis. Nearly 70% of the cancer cases were diagnosed within the first two years of follow-up, especially during the first year. This could be due to more in-depth examinations in patients presenting other abnormalities after an initial contact, such as unexplained iron deficiency anemia or elevated prostate-specific antigen levels. On the other hand, this may also introduce a diagnostic lead-time bias. So, we must consider the possibility that our patients underwent closer follow-up and more thorough evaluation compared to the reference population.
These findings are consistent with other studies showing a positive association between GPSD and neoplasms.9–11 This has clinical relevance and implications for clinical practice, with physicians needing to consider the necessity of cancer screening from the time of diagnosis. The rheumatologist played a direct role in the diagnosis of 5 (31.3%) of the recorded neoplasms by requesting additional tests and referring the patients to other specialists.
Even though the chronic inflammation associated with GPSD in the long term could contribute to the development of neoplasms, numerous studies have discussed the possibility that GPSD might be a paraneoplastic syndrome. The fact that cancer cases frequently appear within the first year of follow-up in many studies9,10 could reinforce the idea that in some cases, GPSD acts as a clinical manifestation of an underlying occult neoplasm, and we may, in fact, be dealing with prevalent, not incident, cancer cases. Furthermore, it has been suggested that the paraneoplastic role of PMR is especially linked to hematologic neoplasms,16 which are less prominent in our series (only one case). Nevertheless, we did not find sufficient evidence to affirm that GPSD is indeed a paraneoplastic syndrome. The rapid improvement of patients with accessible, effective, and inexpensive treatment complicates the design of studies to differentiate between causality and coincidence.19 Our findings suggest that GPSD may not strictly fulfill the criteria for paraneoplastic syndrome but warrant further study regarding its long-term cancer risk.
The limitations of our study are mainly due to its retrospective nature, with the possible loss of associated information. Additionally, our sample size is relatively small compared to larger registries, which makes it difficult to analyze specific types of cancer associated with GPSD. This fact reduces statistical power and makes it difficult to draw definitive conclusions. Prior studies with larger samples9,10 provide essential comparative data, highlighting the need for further studies with greater statistical power. Therefore, while our findings aligned with previous reports suggesting an increased risk of cancer in GPSD, we emphasize that these results should be interpreted with caution due to the small sample size.
Another potential limitation of the study is the COVID-19 pandemic. GLOBOCAN's estimates rely on pre-pandemic data, which may affect the reliability of their estimates.22 The pandemic affected the number of cancer diagnoses, so the actual number may be underestimated, potentially altering the estimates. In our sample, eight cancers were diagnosed before March 15, 2020 (the start of Spain's lockdown), and eight were diagnosed afterward. Among cases that developed cancer in the long term (more than five years), two patients were diagnosed with cancer before the pandemic, while three were diagnosed with GPSD before the pandemic and developed cancer posteriorly. It is possible that a diagnostic delay occurred in these patients.
On the other hand, even though our study does not have a comparator group from the same center, it does combine individual case review of clinical histories with Spanish general data provided by GLOBOCAN.
Even though in other regions, patients with GPSD, especially those with PMR, are treated in primary care and not followed by a rheumatologist, in our center, they are usually referred from the moment of diagnostic suspicion. A possible limitation of our approach could be the clinical heterogeneity inherent to considering the entire spectrum. However, despite the potential heterogeneity of the sample, in our study, patients with PMR are typically diagnosed by a rheumatologist due to this referral system. Therefore, we included the entire spectrum, as patients are evaluated, followed, and classified within it by a rheumatologist.
Future studies with larger sample sizes could confirm the possible relationship between neoplasms and GPSD and help to understand the underlying mechanisms.
Our finding of a higher incidence of neoplasms in women compared to the general population and the fact that most cancer cases appear within the first year after diagnosis should raise awareness about the potential presence of an underlying neoplasm in some cases. Therefore, close follow-up should be conducted to enable early cancer detection, especially during the first two years.
FundingNo fundings declared.
Conflict of interestThe authors declare that they have no conflicts of interest.
Generative AIDuring the preparation of this work the author) used ChatGPT (OpenAI) in order to improve readability and to support translation into English. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.




