



Health literacy in fibromyalgia syndrome (FMS) has been previously investigated; however, digital and artificial intelligence (AI) literacy remain underexplored in this population. This study aimed to evaluate both e-health and AI literacy in individuals with FMS and to explore factors influencing these competencies, with particular emphasis on AI literacy. Given the central role of digital and AI-related competencies, the study primarily focused on outcomes derived from the E-Health Literacy Scale (eHLS), and Artificial Intelligence Literacy Scale (AILS) scale.
Material and methodsThis cross-sectional study, conducted between December 2024 and May 2025, included 106 FMS patients and 106 age- and sex-matched healthy controls. Participants completed the Revised Fibromyalgia Impact Questionnaire (rFIQ), Beck Depression Inventory (BDI), Beck Anxiety Inventory (BAI), eHLS, and -AILS. Adequate cognitive function was confirmed through clinical interview, absence of cognitive complaints, and the ability to complete questionnaires independently. Between-group comparisons and correlation analyses were performed.
ResultsAlthough eHLS scores were slightly higher in the FMS group, the difference was not statistically significant (p=0.074). AILS scores were significantly greater among FMS patients compared to controls (p<0.001). No correlation was observed between eHLS or AILS and symptom severity. However, both measures demonstrated a shared digital competency profile, as reflected by their strong mutual correlation. However, a strong positive correlation was found between eHLS and AILS (r=0.736, p<0.001).
ConclusionsThis is the first study to assess AI literacy in FMS using a validated scale. The observed link between digital and AI literacy highlights their intertwined roles in chronic disease management. These results underscore the need for future interventions focused on enhancing digital competencies among individuals with FMS. Future research should also incorporate broader patient-centered outcomes, including quality of life, treatment adherence, disease burden, and disease severity, to determine the real-world impact of AI literacy on fibromyalgia management.
Trial registrationClinicalTrials.gov Identifier: NCT07020845, Registration date: December 16, 2024.
La alfabetización en salud en el síndrome de fibromialgia (FMS) ha sido previamente investigada; sin embargo, la alfabetización digital y en inteligencia artificial (IA) permanece poco explorada en esta población. El objetivo de este estudio fue evaluar tanto la alfabetización en salud digital (e-salud) como la alfabetización en IA en individuos con FMS, y explorar los factores que influyen en estas competencias, con especial énfasis en la alfabetización en IA. Dado el papel central de las competencias digitales y relacionadas con la IA, el estudio se centró principalmente en los resultados derivados de las escalas eHLS y AILS.
Material y métodosEste estudio transversal, realizado entre diciembre de 2024 y mayo de 2025, incluyó a 106 pacientes con FMS y 106 controles sanos pareados por edad y sexo. Los participantes completaron el Cuestionario de Impacto de la Fibromialgia Revisado (rFIQ), el Inventario de Depresión de Beck (BDI), el Inventario de Ansiedad de Beck (BAI), la Escala de Alfabetización en Salud Electrónica (eHLS) y la Escala de Alfabetización en Inteligencia Artificial (AILS). Se efectuaron comparaciones entre grupos y análisis de correlación.
ResultadosAunque las puntuaciones de la eHLS fueron ligeramente más altas en el grupo con FMS, la diferencia no alcanzó significación estadística (p=0,074). Las puntuaciones de la AILS fueron significativamente mayores en los pacientes con FMS en comparación con los controles (p <0,001). No se observó correlación entre la eHLS o la AILS y la gravedad de los síntomas. Sin embargo, se encontró una fuerte correlación positiva entre la eHLS y la AILS (r=0,736, p <0,001). Ambas medidas reflejaron un perfil compartido de competencia digital, como lo demuestra su fuerte correlación mutua.
ConclusionesEste es el primer estudio que evalúa la alfabetización en IA en pacientes con FMS mediante una escala validada. El vínculo observado entre la alfabetización digital y la alfabetización en IA resalta su papel interrelacionado en el manejo de enfermedades crónicas. Estos resultados subrayan la necesidad de desarrollar futuras intervenciones dirigidas a mejorar las competencias digitales en individuos con FMS. Futuras investigaciones deberán incluir medidas centradas en el paciente, como la calidad de vida, la adherencia al tratamiento, la carga y la severidad de la enfermedad, para determinar el impacto real de la alfabetización en IA en el manejo de la fibromialgia.
Registro del estudioClinicalTrials.gov Identificador: NCT07020845, fecha de registro: 16 de diciembre de 2024.
Fibromyalgia syndrome (FMS) is a chronic, multifaceted musculoskeletal disorder characterized by widespread pain, fatigue, sleep disturbances, cognitive dysfunction, and various somatic symptoms.1 These manifestations collectively impair physical functioning, emotional well-being, and quality of life, making FMS a complex condition that requires continuous self-management. The absence of clear organic pathology often leads patients to seek additional sources of information to better understand their symptoms and treatment options.
With the increasing digitalization of healthcare, online platforms have become a primary source of health information for many individuals. Timely access to accurate digital health information can aid patients in understanding chronic diseases and participating more effectively in their care.2,3 This trend has highlighted the importance of health literacy (HL), defined as the ability to obtain, interpret, and apply health information and navigate healthcare systems competently.4 Given that a significant proportion of the population obtains health information from online databases, digital platforms now play an essential role in shaping HL.5 Despite this shift, the extent to which patients with FMS can effectively use digital health resources remains insufficiently explored.
Artificial intelligence (AI) has increasingly been incorporated into healthcare delivery, influencing diagnostic support, patient education, and digital communication, although concerns regarding trust, accuracy, and integration persist among healthcare providers.6,7 Improving HL remains a crucial element for optimizing patient engagement, adherence, and overall quality of life. Prior research evaluating HL in FMS has yielded inconsistent findings across populations and methodologies, and importantly, no study has assessed digital health literacy in this population using the E-Health Literacy Scale (eHLS). Similarly, although AI-related studies involving FMS have addressed issues such as physician attitudes, AI-generated informational content, or large-scale digital analyses, they have not examined patient-level artificial intelligence literacy.8–10 To date, no study has evaluated AI literacy in individuals with FMS using a validated instrument such as the AILS, leaving a significant gap in the literature.
The present study aimed to evaluate both e-health and AI literacy in individuals with FMS, with particular emphasis on AI literacy, and to identify factors associated with these competencies. All participants were required to demonstrate adequate cognitive function to ensure the reliability of self-reported literacy measures. Understanding patients’ readiness to use AI-based tools is essential for informing strategies that enhance digital health education and support more effective disease management. Furthermore, by examining associations between literacy levels and demographic, clinical, and psychosocial variables, this study seeks to contribute to a more individualized and efficient integration of digital technologies into fibromyalgia care.
Patient and methodsStudy designA cross-sectional observational design was employed for this study, carried out between December 2024 and May 2025, including both patient and control groups. Written informed consent was obtained from all participants prior to enrollment. Participants were also informed that they could withdraw at any time without providing a reason. The structure and content of the questionnaire were reviewed by a panel of experts in physical medicine and public health. The selection of assessment tools prioritized the evaluation of digital health and artificial intelligence literacy, and the additional questionnaires were included solely to explore secondary associations. Prior to full administration, a pilot test was conducted on 10 patients to ensure clarity and comprehensibility. No major modifications were needed. The research protocol obtained formal clearance from the Human Research Ethics Committee (2024-GOKAEK-2411_2024.10.16_160), ensuring compliance with international ethical standard. Patient enrollment start date: 16/12/2024, and ClinicalTrials.gov registration ID: NCT07020845.
PatientsPatients aged 18–50 who attended the Physical Medicine and Rehabilitation outpatient clinic at Bozok University Faculty of Medicine, met the 2016 American College of Rheumatology (ACR) fibromyalgia diagnostic criteria, demonstrated adequate cognitive function, were literate, and consented to participate were enrolled as the patient group. Cognitive function was assessed through clinician-administered orientation, attention, and comprehension questions during routine physical examination. After the patient group was completed, the gender distribution and average age of the patient group were determined. The control group consisted of healthy volunteers matched to the patient group in terms of age and sex, aged 18–50 years, with intact cognitive function and literacy skills, no reported health issues, and who willingly consented to participate in the study. Cognitive status was evaluated using the same brief clinical mental assessment applied to the patient group.
The questionnaires were administered in-person during outpatient clinic visits by trained researchers. The sociodemographic questionnaire, which was the data collection tool, was administered face-to-face to individuals at the Physical Medicine and Rehabilitation clinic along with several assessment scales: the Revised Fibromyalgia Impact Questionnaire (rFIQ), the Beck Depression Inventory (BDI), Beck Anxiety Inventory (BAI), the eHLS, and the AILS.
rFIQ: aims to measure FMS patient status, progress and outcomes through 21 questions that inquire about physical functions, work-related situations, depression, anxiety, waking up tired, pain, stiffness, and fatigue The Turkish adaptation of the rFIQ was psychometrically evaluated for validity and reliability by Sarmer et al.11 In this study, the rFIQ was used only to examine potential secondary associations with digital and AI literacy levels.
BDI: is developed by Beck and colleagues in 1961, is intended to evaluate the typical signs and symptoms associated with depression. This instrument is a self-administered questionnaire comprising 21 items and usually requires around 10min to complete. The Turkish version of the inventory was adapted and validated by Hisli and colleagues.12 The BDI served as a secondary variable to explore potential correlations with literacy scores.
BAI: is developed by Aaron T. Beck, is an internationally validated tool for assessing anxiety levels. It consists of 21 items. The Turkish adaptation and validation of the inventory were performed by Ulusoy and colleagues.13 The BAI was likewise used solely for secondary correlation analyses.
eHLS: An 8-item, 5-point Likert-type scale developed by Norman and Skinner,14 validated in Turkish by Tamer Gencer.15 Higher scores indicate higher e-HL.26
AILS: A 12-item, 7-point Likert-type scale developed by Wang et al.,16 and adapted into Turkish by Çelebi et al.17 Higher scores indicate greater AI literacy.
Statistical analysisSample size estimation was performed using the OpenEpi application (https://www.openepi.com/SampleSize/SSPropor.htm). Based on data from a previous study by Zaimoğlu et al. on e-HL [30], the required sample size was calculated using G*Power version 3.1.9.7. Assuming a power of 95% and a margin of error of 5%, it was determined that at least 105 participants were needed in each group (patient and control), resulting in a total sample of 210 individuals.18 Data analyses were conducted using SPSS software version 25.0 (SPSS Inc., Armonk, NY). The normality of continuous variables was assessed with the Kolmogorov–Smirnov test, supported by skewness and kurtosis values, which indicated that the data were normally distributed. Categorical variables were analyzed using the Pearson Chi-square test, depending on expected cell frequencies. For continuous variables, group differences were examined using the Independent Samples t-test and One-Way Analysis of Variance (ANOVA), as appropriate. Post hoc comparisons in multiple group analyses were conducted using Tukey's test. To evaluate the relationships between variables and disease activity or scale scores (rFIQ, BDI, BAI, eHLS, and AILS), Pearson correlation coefficients were calculated.19 These analyses were performed to investigate whether psychological factors or symptom severity influenced digital and AI literacy, consistent with the exploratory nature of the study. All data were double-entered into a secured database by two independent researchers to minimize entry errors. Incomplete or inconsistent responses were excluded from the final analysis.
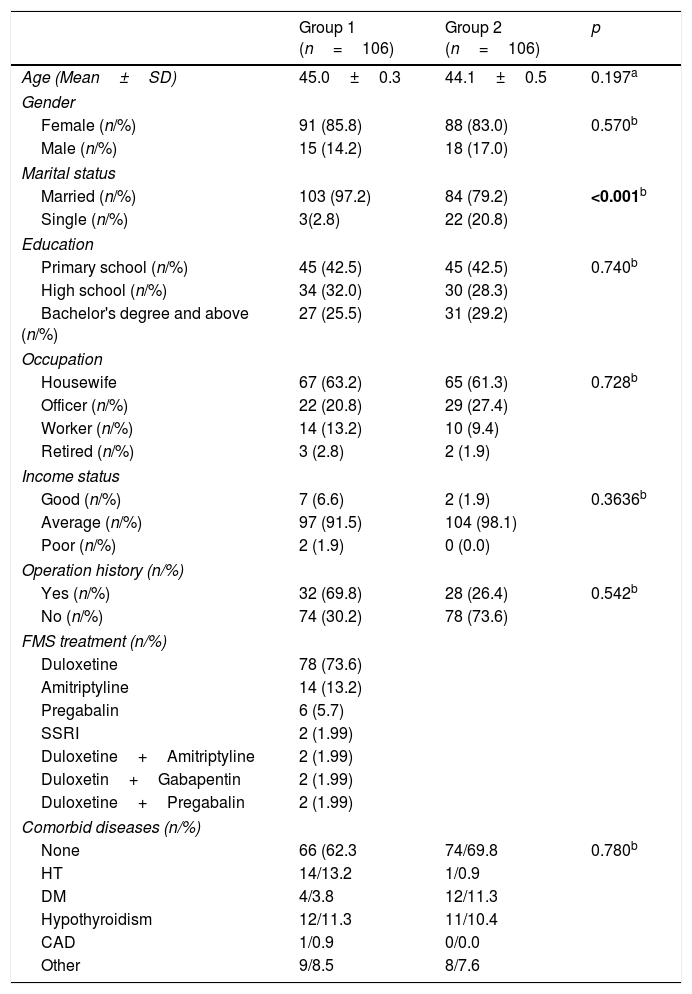
ResultsThe study sample comprised 212 individuals, including 106 patients diagnosed with FMS (Group 1) and 106 healthy controls (Group 2). Table 1 summarizes the sociodemographic and clinical data of the participants. No statistically significant differences were observed between the groups in terms of mean age or gender distribution (p>0.05). However, the proportion of married individuals was notably greater in the FMS group (p<0.001). Educational background, employment status, income level, and residential setting were comparable across both groups, showing no significant differences (p>0.05). The majority of FMS patients were treated with duloxetine (73.6%), while smaller proportions received pregabalin (12.3%) or amitriptyline (8.5%). No significant differences were found between the groups regarding the prevalence of comorbidities such as hypertension, diabetes mellitus, and coronary artery disease (p>0.05) (Table 1).
Demographic and clinical features of the patients in each group.
| Group 1 (n=106) | Group 2 (n=106) | p | |
|---|---|---|---|
| Age (Mean±SD) | 45.0±0.3 | 44.1±0.5 | 0.197a |
| Gender | |||
| Female (n/%) | 91 (85.8) | 88 (83.0) | 0.570b |
| Male (n/%) | 15 (14.2) | 18 (17.0) | |
| Marital status | |||
| Married (n/%) | 103 (97.2) | 84 (79.2) | <0.001b |
| Single (n/%) | 3(2.8) | 22 (20.8) | |
| Education | |||
| Primary school (n/%) | 45 (42.5) | 45 (42.5) | 0.740b |
| High school (n/%) | 34 (32.0) | 30 (28.3) | |
| Bachelor's degree and above (n/%) | 27 (25.5) | 31 (29.2) | |
| Occupation | |||
| Housewife | 67 (63.2) | 65 (61.3) | 0.728b |
| Officer (n/%) | 22 (20.8) | 29 (27.4) | |
| Worker (n/%) | 14 (13.2) | 10 (9.4) | |
| Retired (n/%) | 3 (2.8) | 2 (1.9) | |
| Income status | |||
| Good (n/%) | 7 (6.6) | 2 (1.9) | 0.3636b |
| Average (n/%) | 97 (91.5) | 104 (98.1) | |
| Poor (n/%) | 2 (1.9) | 0 (0.0) | |
| Operation history (n/%) | |||
| Yes (n/%) | 32 (69.8) | 28 (26.4) | 0.542b |
| No (n/%) | 74 (30.2) | 78 (73.6) | |
| FMS treatment (n/%) | |||
| Duloxetine | 78 (73.6) | ||
| Amitriptyline | 14 (13.2) | ||
| Pregabalin | 6 (5.7) | ||
| SSRI | 2 (1.99) | ||
| Duloxetine+Amitriptyline | 2 (1.99) | ||
| Duloxetin+Gabapentin | 2 (1.99) | ||
| Duloxetine+Pregabalin | 2 (1.99) | ||
| Comorbid diseases (n/%) | |||
| None | 66 (62.3 | 74/69.8 | 0.780b |
| HT | 14/13.2 | 1/0.9 | |
| DM | 4/3.8 | 12/11.3 | |
| Hypothyroidism | 12/11.3 | 11/10.4 | |
| CAD | 1/0.9 | 0/0.0 | |
| Other | 9/8.5 | 8/7.6 | |
SD: standard deviation, n: number.
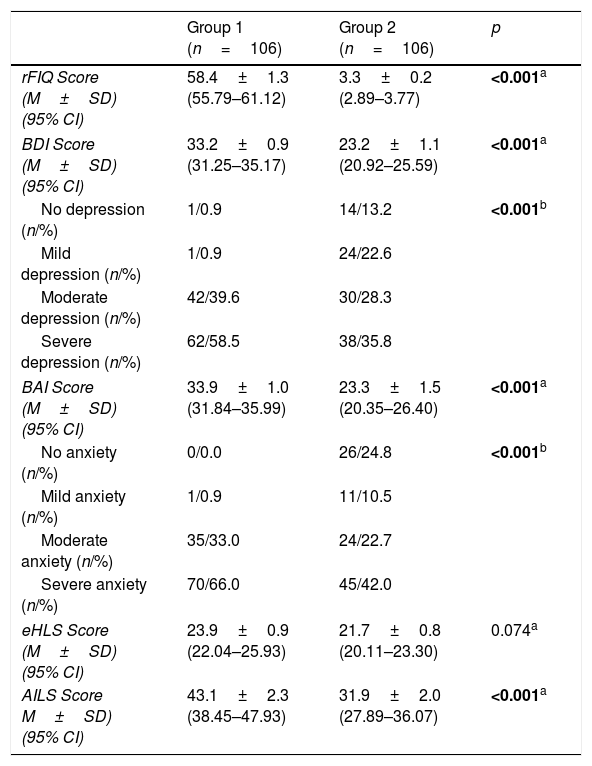
The fibromyalgia group exhibited significantly higher functional impairment, with a mean rFIQ score of 58.4±1.3 compared to 3.3±0.2 in controls (p<0.001). These findings confirm the substantial disease burden experienced by FMS patients, which may influence how they engage with digital and AI-based health information. Similarly, BDI scores were elevated in the fibromyalgia group (33.2±0.9) versus controls (23.2±1.1), with 58.5% of patients experiencing severe depression compared to 35.8% in the control group (p<0.001). Anxiety levels measured by BAI were also higher among fibromyalgia patients (33.9±1.0) than controls (23.3±1.5), with severe anxiety present in 66.0% versus 42.0% of controls (p<0.001). Although the fibromyalgia group had a higher mean eHLS score (23.9±0.9) than controls (21.7±0.8), this difference was not statistically significant (p:0.074). This lack of significance underscores that digital health literacy alone does not account for the higher AI literacy observed in the FMS group. In contrast, AILS scores were significantly greater in the fibromyalgia group (43.1±2.3) compared to controls (31.9±2.0), indicating higher AI literacy among patients (p<0.001). Given that AI literacy constituted the primary focus of the study, this difference represents a key finding of the analysis. Comparison of laboratory parameters and scores between groups is given in Table 2.
Laboratory features, and scores of the patients in each group.
| Group 1 (n=106) | Group 2 (n=106) | p | |
|---|---|---|---|
| rFIQ Score (M±SD) (95% CI) | 58.4±1.3 (55.79–61.12) | 3.3±0.2 (2.89–3.77) | <0.001a |
| BDI Score (M±SD) (95% CI) | 33.2±0.9 (31.25–35.17) | 23.2±1.1 (20.92–25.59) | <0.001a |
| No depression (n/%) | 1/0.9 | 14/13.2 | <0.001b |
| Mild depression (n/%) | 1/0.9 | 24/22.6 | |
| Moderate depression (n/%) | 42/39.6 | 30/28.3 | |
| Severe depression (n/%) | 62/58.5 | 38/35.8 | |
| BAI Score (M±SD) (95% CI) | 33.9±1.0 (31.84–35.99) | 23.3±1.5 (20.35–26.40) | <0.001a |
| No anxiety (n/%) | 0/0.0 | 26/24.8 | <0.001b |
| Mild anxiety (n/%) | 1/0.9 | 11/10.5 | |
| Moderate anxiety (n/%) | 35/33.0 | 24/22.7 | |
| Severe anxiety (n/%) | 70/66.0 | 45/42.0 | |
| eHLS Score (M±SD) (95% CI) | 23.9±0.9 (22.04–25.93) | 21.7±0.8 (20.11–23.30) | 0.074a |
| AILS Score M±SD) (95% CI) | 43.1±2.3 (38.45–47.93) | 31.9±2.0 (27.89–36.07) | <0.001a |
M: mean, SD: standard deviation, n: number, CI: confidence interval, S: score.
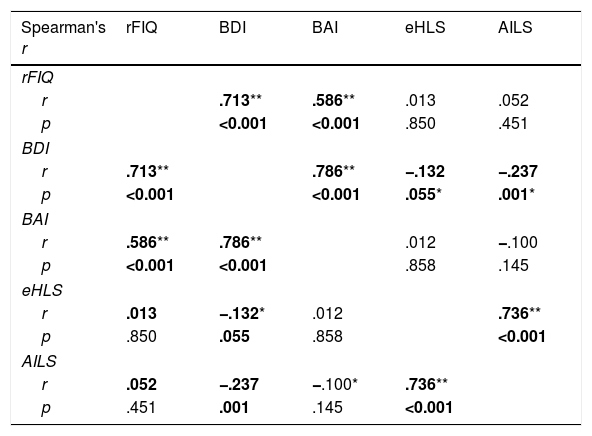
A Pearson correlation analysis showed a strong positive association between rFIQ and BDI (r=0.713, p<0.001) and a moderate correlation with BAI (r=0.586, p<0.001), indicating that increased disease impact was linked to higher depression and anxiety. The analysis revealed no meaningful association between rFIQ scores and either eHLS or AILS scores. This suggests that symptom severity alone does not determine literacy levels, a point further explored in the discussion. BDI and BAI were strongly correlated (r=0.786, p<0.001). BDI scores showed a slight inverse relationship with AILS (r=−0.237, p:0.001), whereas the association with eHLS was near the threshold of statistical significance (r=−0.132, p:0.055). Anxiety scores were not significantly associated with either literacy scale. Notably, eHLS and AILS were strongly and positively correlated (r=0.736, p<0.001), suggesting overlap between digital and AI literacy (Table 3).
Spearman correlation analysis of rFIQ score with Beck Depression Inventory (BDI), Beck Anxiety Inventory (BAI), the E-Health Literacy Scale (eHLS), and the Artificial Intelligence Literacy Scale (AILS) in group 1.
| Spearman's r | rFIQ | BDI | BAI | eHLS | AILS |
|---|---|---|---|---|---|
| rFIQ | |||||
| r | .713** | .586** | .013 | .052 | |
| p | <0.001 | <0.001 | .850 | .451 | |
| BDI | |||||
| r | .713** | .786** | −.132 | −.237 | |
| p | <0.001 | <0.001 | .055* | .001* | |
| BAI | |||||
| r | .586** | .786** | .012 | −.100 | |
| p | <0.001 | <0.001 | .858 | .145 | |
| eHLS | |||||
| r | .013 | −.132* | .012 | .736** | |
| p | .850 | .055 | .858 | <0.001 | |
| AILS | |||||
| r | .052 | −.237 | −.100* | .736** | |
| p | .451 | .001 | .145 | <0.001 | |
M: mean, SD: standard deviation, n: number, S: score, rFIQ: the Revised Fibromyalgia Impact Questionnaire, BDI: Beck Depression Inventory, BAI: Beck Anxiety Inventory, eHLS: E-Health Literacy Scale, AILS: Artificial Intelligence Literacy Scale.
The study enrolled a total of 212 individuals, comprising 106 fibromyalgia patients and 106 healthy controls. While the fibromyalgia group exhibited marginally higher e-HL scores compared to the control group, this difference did not reach statistical significance. Given that this study primarily aimed to evaluate digital and AI literacy, the interpretation of our findings should be framed within this focus. In contrast, AI literacy was significantly higher among patients, suggesting greater familiarity or engagement with AI-related health information. This finding further reinforces the central focus of the study, highlighting AI literacy as a key dimension of patient engagement with emerging health technologies. Although neither eHLS nor AILS scores showed a relationship with the severity of fibromyalgia symptoms, the high degree of concordance between the two measures suggests a close connection between digital literacy and AI literacy.
In this study, most demographic variables such as age, gender, education, and income levels were similar between the fibromyalgia and control groups, with the exception of a higher rate of marriage among patients. The predominance of female participants in the FMS group aligns with existing literature indicating that fibromyalgia predominantly affects women.1,2 Clinically, the elevated mean rFIQ scores point to considerable functional limitations in the patient group, consistent with prior studies emphasizing the disabling effects of the disorder.9,20 Likewise, the significantly increased BDI and BAI scores among patients illustrate the substantial emotional distress commonly linked to fibromyalgia, reinforcing its association with depression and anxiety symptoms.2,6 These clinical features reflect a substantial disease burden, which is relevant when interpreting how patients interact with digital tools, even though symptom severity in our study did not correlate with literacy scores. The higher proportions of participants showing severe psychological symptoms compared to some previous studies may reflect the more pronounced disease burden or chronicity in our sample. However, in contrast to earlier findings that reported correlations between symptom severity and demographic variables such as education and income,9,20 our data did not demonstrate such associations. Importantly, while previous studies linked higher literacy or education with improved functional outcomes or treatment responsiveness, our findings suggest that digital and AI literacy may be influenced by factors beyond symptom severity or burden. This divergence may stem from variations in sample characteristics or differences in access to health services, underscoring the value of considering local and population-specific factors when interpreting FMS outcomes.
Between May and July 2020, health literacy was assessed using EHLS-TR, disease activity with rFIQ, and pain intensity with Numerical Rating Scale (NRS) in 32 female FM patients (mean age 46.2±8.8) and 27 healthy female controls (mean age 41.7±12.6). EHLS-TR scores were significantly lower in the FM group compared to controls. In the FM group, EHLS-TR scores showed a significant negative correlation with age and positive correlations with education and income levels.9 The relationship between complementary and alternative treatments (CAM) and HL was evaluated in 160 women diagnosed with FMS in 2021; an open-ended questionnaire including CAM preferences, visual analog scale (VAS) for pain level, rFIQ for disease impact and HLS-EU-Q47 for HL were used and patients were divided into two groups as CAM users and non-users. The overall HL score was 30.94±8.40, indicating a problematic/limited level of health literacy, with no significant variation observed between CAM users and non-users.10 The relationship between HL and medication adherence (IA) and disease activity was examined in 142 FMS patients who had been receiving treatment for at least six months in 2021; Visual VAS, FIQ, HLS-EU-Q47 and Morisky 8-Item Medication Adherence Scale were applied to the patients; no statistically significant difference was found between the HLS-EU-Q47 scale and the Morisky Medication Adherence Scale.8 A rehabilitation program, cognitive therapy and kinesiotherapy were applied to 128 patients diagnosed with FMS in order to determine whether different aspects of the disease change according to the level of education and literacy of the patients when the same treatment is applied in 2024. The patients were divided into four groups according to their level of education, and were evaluated 3 times before, after and 3 months after treatment for 28 weeks. Significant improvements were seen in the SF-12 quality of life in the FIQ score after treatment in patients with higher levels of education; they reported that higher education and HL when combined with non-pharmacological treatments, improved fibromyalgia management and functional outcomes.20
In this study, although eHLS scores were slightly higher in fibromyalgia patients than in healthy individuals, the difference was not statistically significant. This finding supports the results of Karlıbel et al.,10 who also reported limited HL in fibromyalgia patients and no significant differences based on CAM use. Similarly, Aksoy et al.8 found no clear link between HL and medication adherence, which is consistent with our observation that eHLS was not correlated with disease severity or symptom burden. However, unlike the findings of Büyükşireci and Demirsoy,9 who reported significantly lower HL among FMS patients and a strong relationship with education and income level, our study found no such associations, possibly due to the more balanced sociodemographic distribution in our sample. Additionally, while the Romanian study by Amzolini et al.,20 emphasized improved treatment outcomes in patients with higher education and literacy, our results showed no direct relationship between eHLS and functional impairment, suggesting that literacy alone may not predict clinical status in the absence of structured interventions. This aligns with broader evidence indicating that health literacy, disease activity, and quality of life do not always show linear associations, particularly in chronic pain disorders where psychosocial factors modulate functional outcomes. Notably, our study is the first to assess both eHLS and AILS together in FMS, revealing a strong correlation between them and highlighting the importance of considering both dimensions in digital health strategies. Supporting our eHLS findings, this review details how digital health technologies facilitate patient engagement and disease self-management in rheumatic diseases while also identifying literacy gaps as a key barrier.21
There is no study in the literature evaluating the AILS in FMS. Various studies have addressed FMS in the context of AI. The knowledge levels of 26 physicians on Medical Attitudes Toward the Use of AI in Fibromyalgia were measured with a 21-item anonymous survey at a workshop organized within the scope of the ATLAS 2024 congress; It was stated that although they had high clinical experience, they did not have sufficient knowledge about AI and felt unprepared to use this technology in FM management.22 The quality, readability, and complexity of responses generated by ChatGPT 3.5 using the keywords “fibromyalgia” and “fibromyalgia treatment” identified via Google Trends were evaluated by various measures in 2025; it was found that general fibromyalgia information was more readable, while treatment-related content was more complex.23 A detailed, retrospective and non-invasive analysis was conducted on 400 million documents and 714,000 fibromyalgia-labeled documents worldwide between May 2019 and April 2021 with AI to Understand the Lives of Fibromyalgia Patients in 2025; It was reported that the most frequently reported triggers were stress, anxiety and various foods, Arthritis and irritable bowel syndrome (IBS) were the most common comorbidities, and that there were situations such as inadequate recognition of patients’ diseases in health services, underestimation of symptoms and unmet care needs.24 Recent reviews demonstrate that AI including machine learning and NLP is being successfully applied at multiple stages of chronic pain management, supporting our finding that fibromyalgia patients can benefit from AI-driven interventions.25 Emerging AI models such as transformer-based video analysis frameworks show promise for objective pain estimation, suggesting future directions for AI literacy development in fibromyalgia technology applications.26
To our knowledge, this is the first study to assess AI literacy in fibromyalgia patients using a validated scale (AILS). The novelty of evaluating AI literacy directly aligns with the evolving role of AI-based systems in chronic pain management and strengthens the relevance of our findings. Our findings demonstrated that individuals with fibromyalgia had significantly higher AI literacy levels compared to healthy controls. This result diverges from the study by Cascella et al.,22 where experienced physicians reported feeling inadequately prepared to apply AI in fibromyalgia care, suggesting that patients may be more open to or exposed to AI-related health information than clinicians anticipate. Additionally, the study by Pasin et al.,23 highlighted that AI-generated responses on fibromyalgia treatment were often complex, potentially requiring advanced literacy skills, which aligns with the higher AILS scores observed in our patient group. The large-scale analysis conducted by Bell et al.,24 also supports the relevance of AI in understanding patient experiences, further emphasizing the growing presence of AI-based tools in the daily lives of those living with chronic conditions. The strong correlation we observed between eHLS and AILS underscores the interconnectedness of digital and AI literacy, suggesting that individuals proficient in navigating online health information may also be more capable of engaging with AI-driven technologies. The strong correlation between AILS and eHLS further suggests that digital behavior patterns in FMS patients may reflect an adaptive coping strategy shaped by disease burden and frequent healthcare encounters. These findings underscore the importance of incorporating AI and digital literacy into patient education, which may enhance self-management and engagement with digital tools in FMS care. Moreover, leaders in digital rheumatology have highlighted the rapid integration of digital health and AI tools into clinical practice, underscoring the timeliness and relevance of assessing AI literacy among fibromyalgia patients.27 Furthermore, comprehensive reviews argue that methodological rigor in assessing AI literacy is warranted due to AI's expanding role in chronic pain treatment strategies.28 This study adds to the existing literature by being the first to assess AI and e-health literacy in fibromyalgia within the scope of Rheumatology International, providing insights for future digital health integration in rheumatology. Future studies should additionally evaluate quality of life, treatment adherence, overall disease burden, and disease severity to better determine the real-world clinical benefits of enhanced digital and AI literacy in fibromyalgia.
This study has several limitations. Its cross-sectional design does not allow for causal inferences. Participants were recruited from a single tertiary center, potentially limiting generalizability. Furthermore, AI literacy was assessed through self-report rather than real-time interaction with AI systems, which may not fully capture functional competence. Additionally, the cross-sectional nature of our data prevents evaluating how changes in disease activity or quality of life may influence literacy over time. Additionally, the sample size although statistically adequate was relatively limited, the number of variables assessed was restricted, and the study population was drawn from a single regional center, which may limit generalizability.
ConclusionA major strength of this study is the inclusion of both e-health and AI literacy assessments in a single framework. This dual focus directly responds to the increasing integration of AI systems into digital health platforms, underscoring the necessity of evaluating both competencies together. To our knowledge, this is the first study to use AILS in an FMS population, offering a novel perspective on how patients engage with emerging technologies. The identification of a strong correlation between eHLS and AILS highlights the evolving role of digital competencies in chronic disease management. Overall, this study highlights the growing relevance of AI and digital literacy in the management of fibromyalgia and provides a foundation for future intervention-based research in this evolving domain. Future research should explore longitudinal changes in digital literacy following targeted interventions and evaluate how AI literacy affects clinical decision-making and treatment adherence in fibromyalgia populations.
Authors’ contributionsAll authors meet the ICMJE authorship criteria. GDK, ÖB, and ŞG contributed to study conception and design. Data collection and analysis were performed by GDK and ŞG. GDK drafted the manuscript. All authors critically revised the manuscript for important intellectual content. All authors take full responsibility for the integrity and accuracy of all aspects of the work.
Ethical approvalThe study protocol was approved by Bozok University Non-invasive Clinical Research Ethics Committee (2024-GOKAEK-2411_2024.10.16_160) before study. All procedures performed in studies involving human were in accordance with the ethical standards of the institutional research committee (Bozok University Non-invasive Clinical Research Ethics Committee and with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards.
Informed consentWritten and verbal informed consent was obtained from the patient and control group participants.
Conference presentationNot previously presented at any conference.
Clinical trial registrationPatient enrollment start date: 16/12/2024, and ClinicalTrials.gov registration ID: NCT07020845.
Generative AIPortions of the language editing was supported by OpenAI's ChatGPT. All AI-generated content was critically reviewed, edited, and approved by the authors
FundingThe authors declare that no funds, grants or other support were received during the preparation of this manuscript.
Conflict of interestsAll authors declare that they have no conflicts of interest.
Data availabilityThe datasets generated during and/or analyzed during the current study are available from the corresponding author on reasonable request.
None.




