




To describe and compare the health situation of rheumatoid arthritis (RA) patients from the qom community in the cities of Presidencia Roque Sáenz Peña (PRSP, Chaco Province) and Rosario (Santa Fe Province), focusing on access to the healthcare system and its limitations.
MethodsA sequential mixed-methods approach was used. Quantitative phase: implementation of the Community Oriented Program for Control of Rheumatic Diseases (COPCORD) methodology. Qualitative phase: ethnographic approach incorporating the concept of “healthcare pilgrimage”.
ResultsParticipants living in Rosario reported a higher intensity of pain (202 [42.9%] vs. 14 [11.0%], P < .0001), associated with a greater proportion of functional limitation according to the HAQ-DI score ≥0.8 (302 [64.1%] vs. 39 [30.2%], P < .0001). Among the diagnoses in PRSP, osteoarthritis was more prevalent than in Rosario (49 [10.1%] vs. 67 [4.0%], P < .0001), while RA prevalence was the same in both cities (12 [2.4%] vs. 40 [2.4%], P = .991). Three main topics emerged from the ethnographic analysis: pilgrimage within the healthcare system, barriers to specialized care, and access to treatment.
ConclusionRA patients in both cities face significant challenges in navigating the healthcare system, underscoring their vulnerability. It is essential to adopt care models that integrate local knowledge and consider patients’ mobility trajectories, ensuring access to and continuity of the treatments prescribed.
Describir y comparar la situación de salud de pacientes con artritis reumatoidea (AR) de la comunidad qom de las ciudades de Presidencia Roque Sáenz Peña (PRSP, Provincia de Chaco) y Rosario (Provincia de Santa Fe) en relación al acceso al sistema de salud y sus limitaciones.
MetodologíaMetodología mixta (cuanti-cualitativo) de manera secuencial. Fase cuantitativa: aplicación de la metodología Community Oriented Program for Control of Rheumatic Diseases (COPCORD). Fase cualitativa: abordaje etnográfico, incorporando el concepto de peregrinaje.
ResultadosLos individuos residentes en Rosario describieron una intensidad mayor de dolor (202 (42.9%) vs 14 (11.0%), P < .0001), asociada a una mayor proporción de limitación funcional medida a través del HAQ-DI score ≥ 0.8 (302 (64.1%) vs 39(30.2%), P < .0001). Dentro de los diagnósticos realizados en PRSP, la osteoartritis fue más prevalente en comparación con Rosario (49 (10.1%) vs 67 (4.0%), P < .0001) y AR fue igual en ambas ciudades (12 (2.4%) vs 40 (2.4%), P = .991). Se identificaron tres tópicos en el análisis etnográfico: peregrinación dentro del sistema de salud, limitación a la atención especializada y a los tratamientos.
ConclusiónLos pacientes con AR de ambas ciudades se enfrentan a la complejidad del sistema de salud, remarcando su vulnerabilidad. Es prioritario la adopción de modelos de atención que integren sus saberes, tendiendo en cuenta sus trayectorias de movilidad, garantizando el acceso y continuidad de los tratamientos pautados.
Chronic rheumatic and musculoskeletal diseases are a broad group of conditions affecting approximately 10% of the world's population, generating a significant impact at both the individual and collective levels, with marked functional limitations not only in individual and family life, but also in social and workingl life.1
The Latin American Group for the Study of Rheumatic Diseases in Indigenous Peoples (GLADERPO) has worked since its formation in 2009 with various communities in Argentina, Mexico, Ecuador, Colombia, and Venezuela.2–8 The use of the Community-Oriented Programme for Control of Rheumatic Diseases (COPCORD) methodology3,4,7–9 has enabled the detection of a high number of individuals with musculoskeletal involvement in general and, above all, a high prevalence of rheumatoid arthritis (RA). RA is an aggressive disease, with a high number of familial cases and marked functional limitations.10
From a qualitative perspective, we have described the barriers these communities face in accessing the healthcare system in general, and specialised care in particular.11 One concept that could help understand this complex situation regarding access to care is the “health pilgrimage”. This refers to the prolonged and often erratic journey undertaken by patients and families in search of diagnosis and treatment, along which they face multiple obstacles.12
GLADERPO has worked in an interdisciplinary manner with the Qom community and primary care professionals in the city of Rosario since 2013. The main objectives have been to incorporate and raise awareness within the community at different stages of the healthcare process and access to the healthcare system, fostering competence in navigating the system and emphasizing the importance of detection, treatment, and follow-up for these conditions, through culturally appropriate and respectful educational strategies.13
Essentially GLADERPO has continued documenting the health situation of these communities, who actively move between the provinces of Santa Fe and Chaco, their ancestral homeland. Thus, since 2019, work has been underway with the Qom community residing in the city of Presidencia Roque Sáenz Peña (Chaco province). The initial stages of this work focused on describing the health system, the barriers to care, and their needs.14 Later, an audiovisual educational strategy was developed to ensure continuity of care during the COVID-19 pandemic.13 Our working hypothesis has been that the prevalence of rheumatoid arthritis (RA) and the health status of these communities may differ between the two cities due to their active movement between the two provinces.
Based on the above, this study aims to describe and compare the health status of rheumatoid arthritis (RA) patients from the Qom community in the cities of Presidencia Roque Sáenz Peña (Chaco Province) and Rosario (Santa Fe Province) in relation to their access to the healthcare system and its limitations, using a mixed-method (quantitative-qualitative) approach.
Material and methodsThis was a sequential mixed-methods study, beginning with a quantitative phase followed by a qualitative phase.
PopulationIndividuals aged 18 years or older, who self-identified as Qom and resided for more than six months in the city of Rosario and in Presidencia Roque Sáenz Peña (PRSP), were invited to participate. A census was conducted concurrently with the implementation of the COPCORD instrument, administered in participants' homes with the support of bilingual facilitators/translators (health workers from the community or community leaders).
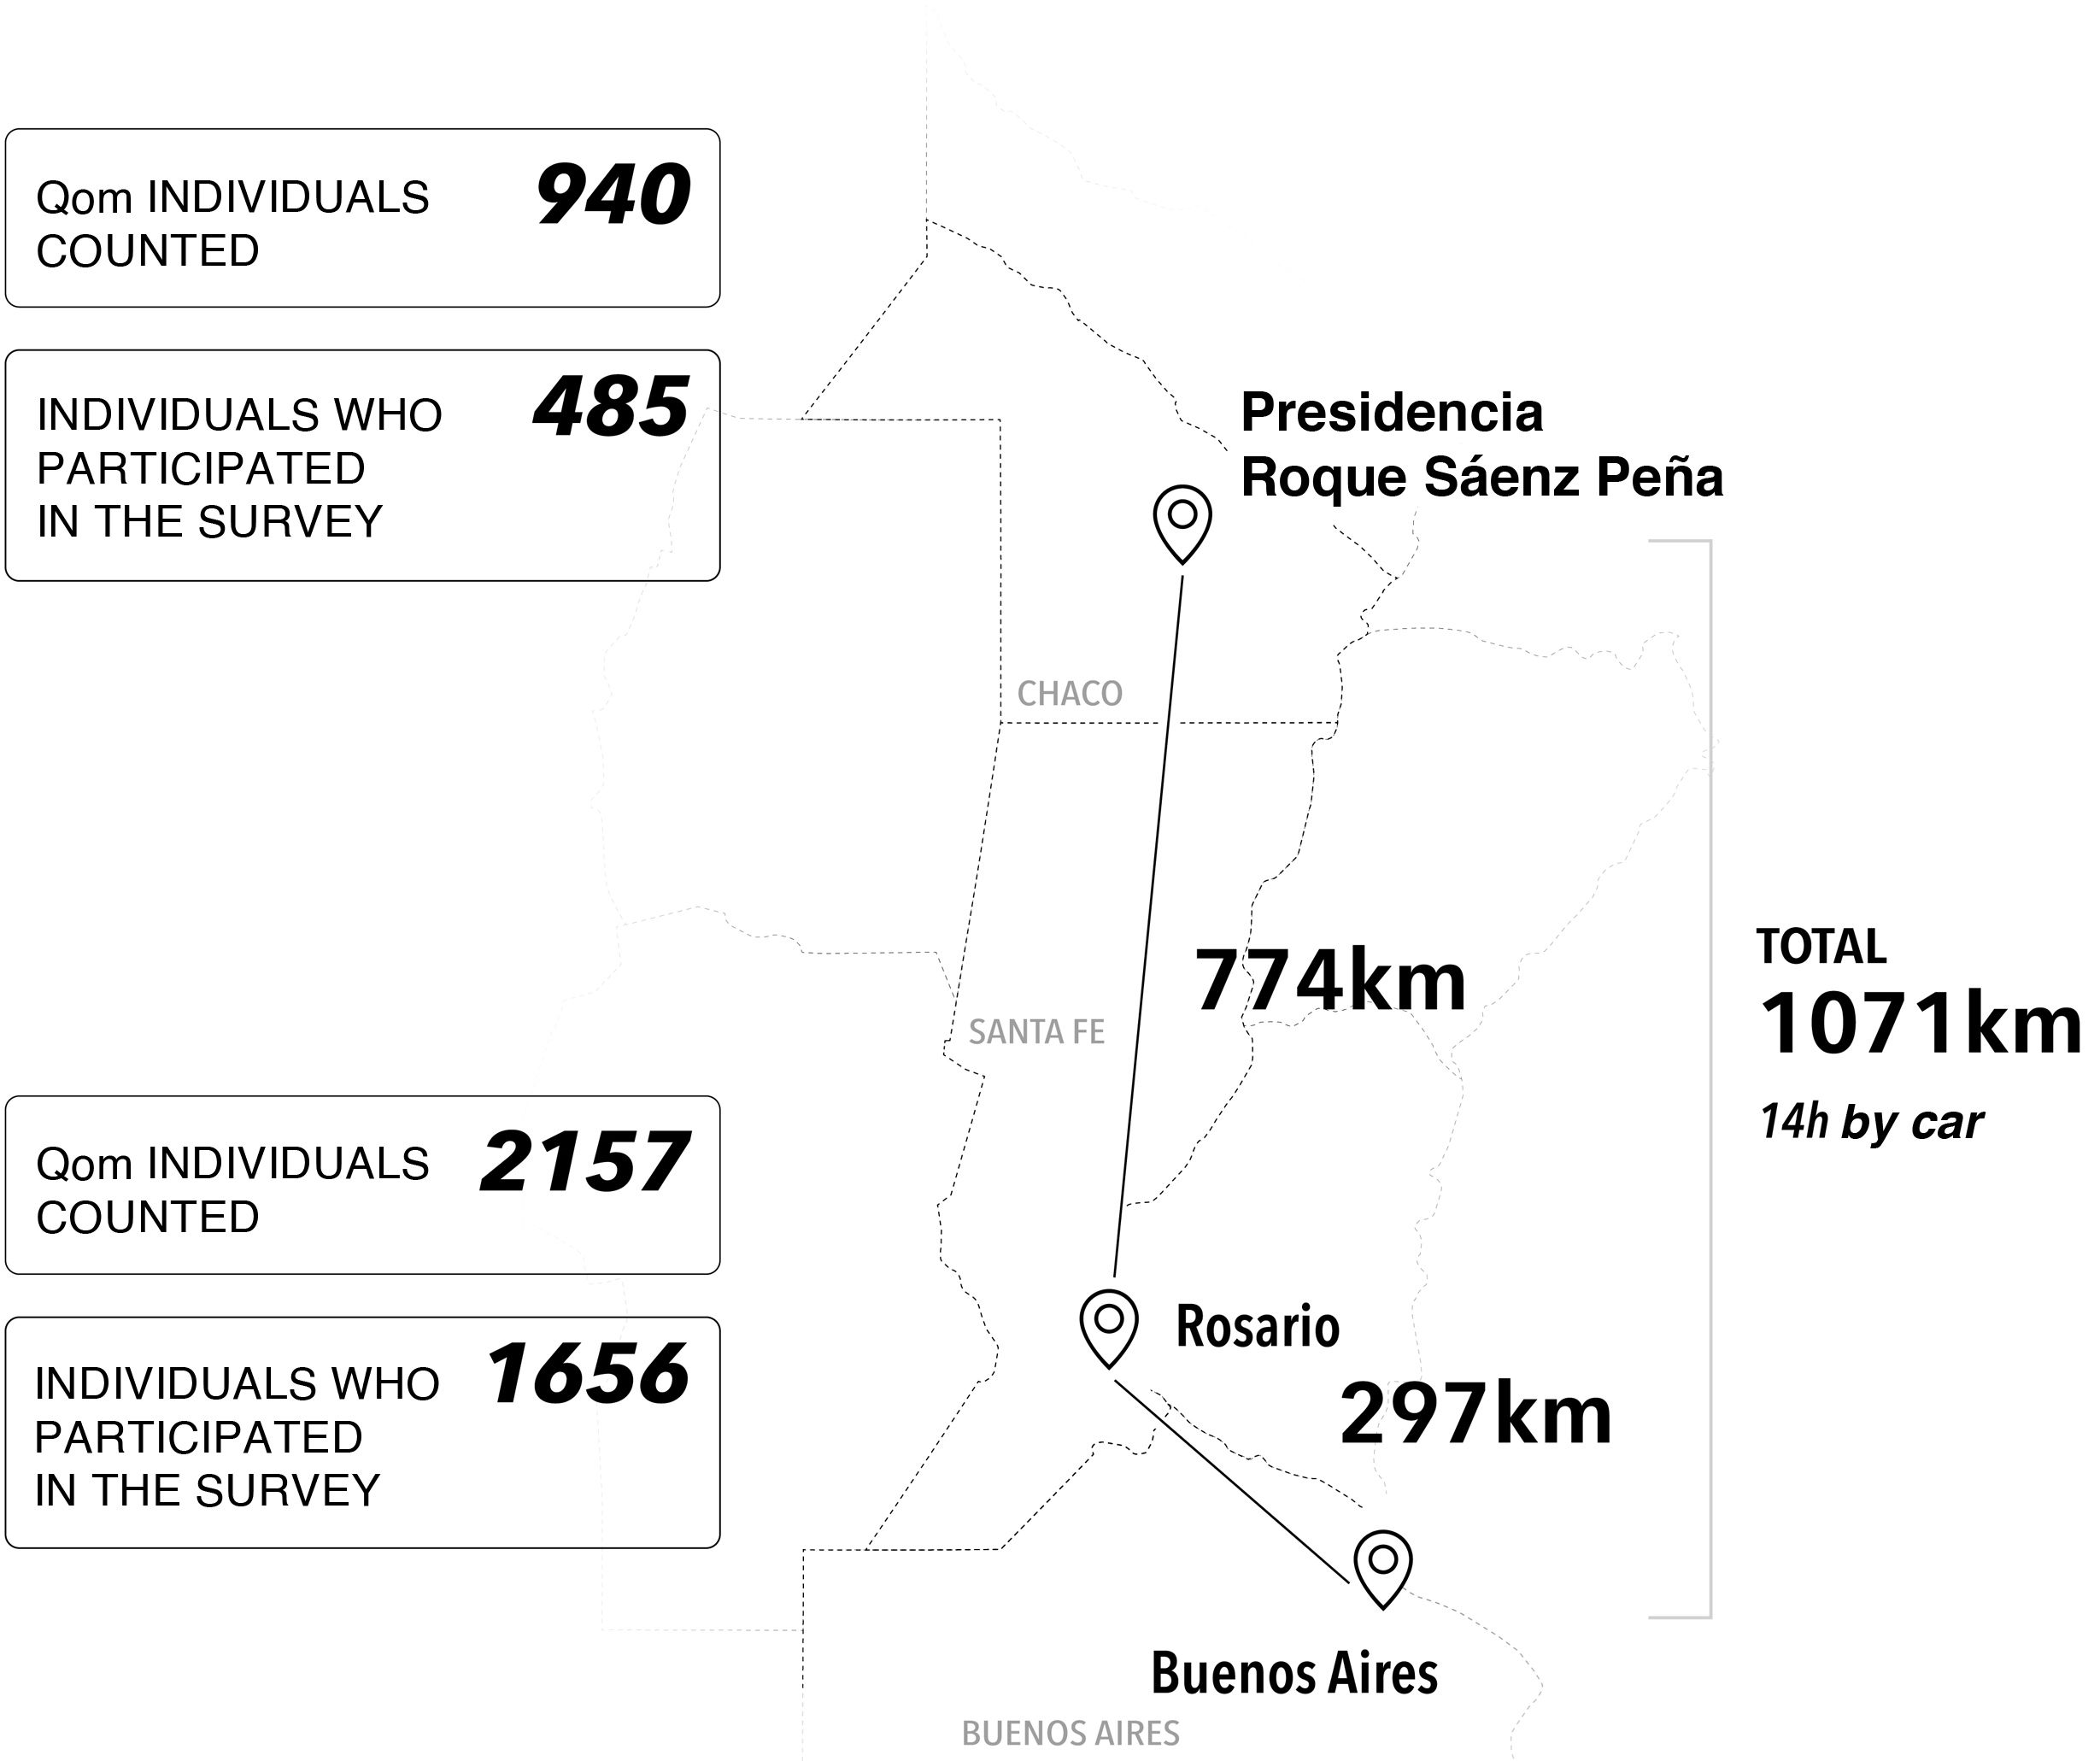
The Qom community experiences constant movement between their home province of Chaco and the neighbouring province of Santa Fe (Fig. 1). The community travels for various reasons, including work, family visits, and seeking healthcare.

Map of the provinces of Santa Fe and Chaco. The map shows the distances travelled by members of the Qom community between the two provinces, as well as the total distance to the capital city. It also shows the number of people counted and surveyed in each of the two cities during this study.
Geographically, the city of Rosario is located 306 km north of the nation's capital, with a population of over 1,190,000. The city of PRSP is located 1077 km north of the capital of Argentina and 744 km from Rosario, with a population of over 89,882, making it the second most populous city in the province of Chaco.
Study descriptionQuantitative phaseA cross-sectional, descriptive, community-based epidemiological study was conducted in the cities of PRSP and Rosario. Participants were individuals over 18 years of age who self-identified as belonging to the Qom people.
The COPCORD methodology was used, which consists of a screening strategy using a brief questionnaire that inquires about the presence of joint pain, stiffness, or inflammation in recent months, as well as self-reported comorbidities and work activity, including physically demanding work. This questionnaire was cross-culturally validated in the Qom population.2,4,10
Functional capacity was assessed using the Health Assessment Questionnaire Disability Index (HAQ-DI), a 10-item tool that measures performance in activities of daily living. The scale is scored from 0 to 3 (0 = no difficulty; 1 = some difficulty; 2 = great difficulty; 3 = cannot perform). The total score was categorised using a cut-off point ≥ .8, indicative of disability. This threshold was previously established by the same group of researchers.15
This methodology has proven to be a useful screening method, with a sensitivity of 96.1%, specificity of 53.6%, a positive likelihood ratio (LR+) of 2.0, and an area under the ROC curve of .74 (95% CI: .67–.81). It has also demonstrated structural validity, especially for the detection of RA.16
The definitive diagnosis was obtained after evaluation by a rheumatologist, particularly to identify patients who met the 2010 ACR/EULAR criteria for RA.17
Qualitative phaseAn ethnographic study was conducted to describe RA patients' perceptions of access to the healthcare system and its limitations. Data collection techniques included informal conversations or co-presence situations, semi-structured interviews, and observations recorded in a field notebook.18 Interview and observation guides were used. The aspects included were: access to the health system and its barriers and facilitators (Appendix B, Annex 1). Theoretical concepts such as health trajectories and the “health pilgrimage” were incorporated,19 understood as the fragmented and repeated journeys that patients undertake in their search for diagnosis and treatment. In addition, interviews were conducted with health workers directly involved in community care who expressed their willingness to participate in the study.
AnalysisQuantitative phaseA descriptive analysis of the variables was performed. For continuous variables, measures of central tendency and dispersion were reported. For categorical variables, absolute and relative frequencies were reported. The results were compared with those obtained in a previous study conducted in the city of Rosario using the same methodology.4 The comparison between groups was performed using the Student's t-test or, if the assumptions of normality were not met, the Wilcoxon test for continuous variables, and the Chi-square or Fisher's exact test for categorical variables. A significance level of .05 was established. Statistical processing was performed using IBM SPSS® Statistics software, version 22 (standard edition).
Qualitative phaseThe dataset (interviews and ethnographic records) was processed using open coding. Trajectories were reconstructed through the participants' narratives and the observations of the anthropological team, followed by a thematic analysis. The criterion of information saturation was used to define the richness and depth of the themes.18 Furthermore, a triangulation process of data, sources, and analysts20 was implemented to compare information from different participants, techniques, and disciplinary perspectives, thus strengthening the validity and reliability of the analysis.
Ethical aspectsIn the city of Rosario, the study was approved for implementation on December 22, 2010, by the Research Ethics Committee of the Rosario Municipal Health Secretariat (resolution number 1659/2009), with the endorsement of the Ministry of Health (resolutions 1619/2010 and 0127/2011). The study was registered (registration order number 13) with the Provincial Bioethics Committee of the Province of Santa Fe on July 5, 2012. In the city of Presidencia Roque Sáenz Peña, it was approved by the Ethics Committee of the Hospital 4 de Junio “Dr. Ramón Carrillo” under registration number 0026/19. Prior informed consent was obtained from community representatives to conduct the study.21 In addition, each participant provided their individual informed consent to participate in the study. The consent process was supported by bilingual facilitators-translators in Spanish or Qom, according to the participant's preference.
ResultsThis paper describes, in context, the sociodemographic characteristics, pain, disability, and rheumatic diseases. The most prevalent conditions in both populations correspond to the quantitative phase of the study (Tables 1–3). From this phase, patients meeting the criteria for rheumatoid arthritis (RA) were identified, either with a recent diagnosis established during this study or with a previously confirmed diagnosis in both cities. Patients identified with RA were subsequently included in the qualitative phase, with the aim of documenting the journey through the healthcare system of individuals with RA detected in the community study.
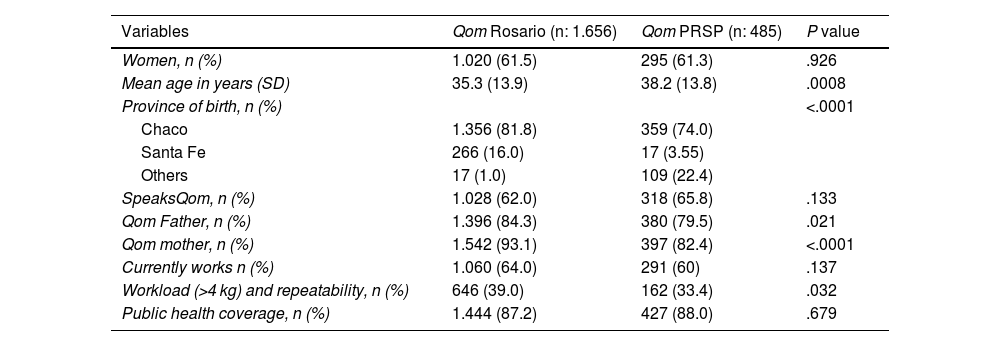
Comparison between the Qom communities surveyed in the city of Rosario and Presidencia Roque Sáenz Peña. Sociodemographic Data.
| Variables | Qom Rosario (n: 1.656) | Qom PRSP (n: 485) | P value |
|---|---|---|---|
| Women, n (%) | 1.020 (61.5) | 295 (61.3) | .926 |
| Mean age in years (SD) | 35.3 (13.9) | 38.2 (13.8) | .0008 |
| Province of birth, n (%) | <.0001 | ||
| Chaco | 1.356 (81.8) | 359 (74.0) | |
| Santa Fe | 266 (16.0) | 17 (3.55) | |
| Others | 17 (1.0) | 109 (22.4) | |
| SpeaksQom, n (%) | 1.028 (62.0) | 318 (65.8) | .133 |
| Qom Father, n (%) | 1.396 (84.3) | 380 (79.5) | .021 |
| Qom mother, n (%) | 1.542 (93.1) | 397 (82.4) | <.0001 |
| Currently works n (%) | 1.060 (64.0) | 291 (60) | .137 |
| Workload (>4 kg) and repeatability, n (%) | 646 (39.0) | 162 (33.4) | .032 |
| Public health coverage, n (%) | 1.444 (87.2) | 427 (88.0) | .679 |
PRSP: Presidencia Roque Sáenz Peña: SD: standard deviation.
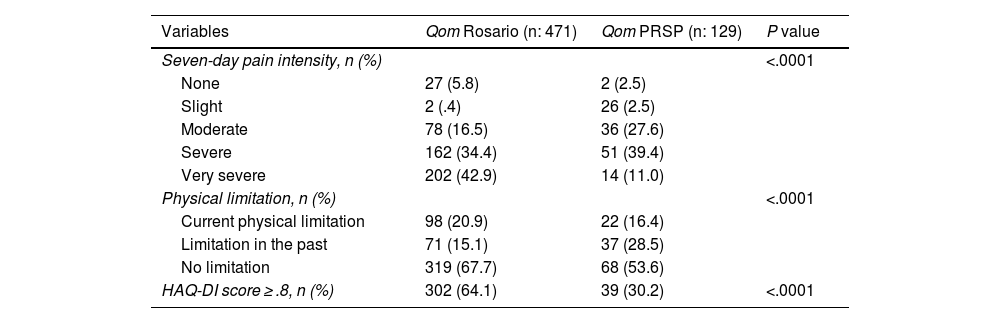
Comparison between the Qom communities surveyed in the city of Rosario and Presidencia Roque Sáenz Peña.Pain characteristics in the last 7 days.
| Variables | Qom Rosario (n: 471) | Qom PRSP (n: 129) | P value |
|---|---|---|---|
| Seven-day pain intensity, n (%) | <.0001 | ||
| None | 27 (5.8) | 2 (2.5) | |
| Slight | 2 (.4) | 26 (2.5) | |
| Moderate | 78 (16.5) | 36 (27.6) | |
| Severe | 162 (34.4) | 51 (39.4) | |
| Very severe | 202 (42.9) | 14 (11.0) | |
| Physical limitation, n (%) | <.0001 | ||
| Current physical limitation | 98 (20.9) | 22 (16.4) | |
| Limitation in the past | 71 (15.1) | 37 (28.5) | |
| No limitation | 319 (67.7) | 68 (53.6) | |
| HAQ-DI score ≥ .8, n (%) | 302 (64.1) | 39 (30.2) | <.0001 |
HAQ-DI score: Assessment Questionnarie Disability Index; PRSP: Presidencia Roque Sáenz Peña.
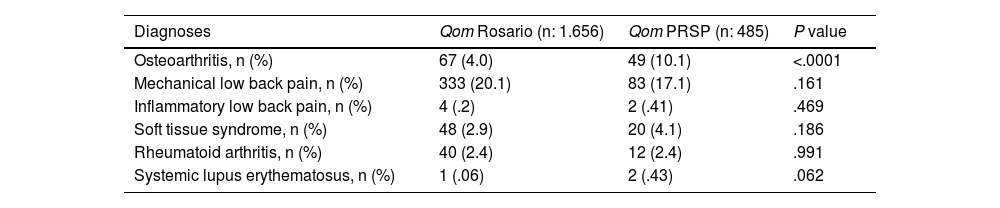
Comparison between the Qom communities surveyed in the city of Rosario and Presidencia Roque Sáenz Peña. Diagnosis after rheumatological evaluation.
| Diagnoses | Qom Rosario (n: 1.656) | Qom PRSP (n: 485) | P value |
|---|---|---|---|
| Osteoarthritis, n (%) | 67 (4.0) | 49 (10.1) | <.0001 |
| Mechanical low back pain, n (%) | 333 (20.1) | 83 (17.1) | .161 |
| Inflammatory low back pain, n (%) | 4 (.2) | 2 (.41) | .469 |
| Soft tissue syndrome, n (%) | 48 (2.9) | 20 (4.1) | .186 |
| Rheumatoid arthritis, n (%) | 40 (2.4) | 12 (2.4) | .991 |
| Systemic lupus erythematosus, n (%) | 1 (.06) | 2 (.43) | .062 |
PRSP: Presidencia Roque Sáenz Peña.
The healthcare model in the city of Rosario is based on the Primary Health Care strategy. Its organisation is based on interconnected networks across different care settings. It features three levels of care: a first level strategically located in the city's neighbourhoods where patients and their families receive follow-up care; a second level, comprising medical specialties, located in the city centre; and a third level consisting of various hospitals. While its administration is municipal, it is linked to the provincial and national systems.22
In the city of PRSP, the public health system is provincially administered and centralised by the Ministry of Public Health (headquartered in the provincial capital). This system is organised into eight health regions. Specifically, the city of PRSP is the seat of Health Region 7. Primary healthcare centres are located in neighbourhoods far from the city centre, and there is only one high-complexity hospital located in the city centre.23
Quantitative phaseIn the city of PRSP, a total of 940 individuals aged 18 years and over, who self-identified as Qom, participated in the study. Of these, 485 were surveyed (51.5%), 58 (3.4%) declined to answer, and 397 (42.2%) were considered absent after repeated home visits. The average length of residence in the neighbourhood was 15.2 years (SD: 13.3), and the average level of education was 6.26 years (SD: 4.56). In the city of Rosario, the census population consisted of 2157 individuals aged 18 years and over who resided permanently. Of these, 1759 (81.5%) participated in the epidemiological study, 103 in the pilot study, and 1656 in the main study. A total of 322 (14.9%) individuals were considered absent, and 76 (3.5%) declined to participate.
The comparison between the two communities regarding the sociodemographic data of the surveyed populations is detailed in Table 1. Individuals residing in PRSP had a higher mean age at the time of the survey (38.2 [SD: 13.8] vs. 35.3 [SD: 13.9] years; P = .0008). Unlike individuals residing in Rosario, where the majority were born in the province of Chaco, PRSP residents reported other provinces, such as Formosa, as their place of birth (109 [22.4%] vs. 17 [1.0%]; P < .0001).
The most frequently self-reported comorbidities were: hypertension (14.8%), Chagas disease (11.5%), tuberculosis (4.95%), and type 2 diabetes (4.12%). Residents of PRSP reported a lower percentage of parents belonging to the Qom community. Regarding their work, they reported a lower percentage of heavy labour compared to residents of Rosario (162 [33.4%] vs. 646 [39.0%]; P = .032).
A total of 129 (26.5%) surveyed individuals residing in the city of PRSP reported pain in the last 7 days. Individuals residing in Rosario reported greater pain intensity (202 [42.9%] vs. 14 [11.0%]; P < .0001), associated with a higher proportion of HAQ-DI scores ≥ .8 (302 [64.1%] vs. 39 [30.2%]; P < .0001) (Table 2).
Among the diagnoses made by specialist physicians in the city of PRSP, osteoarthritis was more prevalent compared to Rosario (49 [10.1%] vs. 67 [4.0%]; P < .0001). The prevalence of RA was the same in both cities (12 [2.4%] vs. 40 [2.4%]; P = .991), indicating that a large percentage of patients were not receiving treatment and that most had been living with RA for years. Similarly, none of the identified patients had travelled to Rosario “for health reasons” (Table 3).
Qualitative phaseFollowing the analysis of interviews conducted with rheumatoid arthritis (RA) patients and healthcare workers directly involved with the communities, three central themes were identified in the ethnographic analysis: the patient care pathway within the healthcare system, specialised care, and limitations in access to care:
Patient care pathway within the healthcare systemAt Rosario, patients diagnosed with a chronic disease enter the healthcare system through their primary care centre, based on their geographic location. This primary care centre is responsible for scheduling appointments with specialists at the secondary care level through a unified appointment system. “(…) Here you always have an appointment (referring to the primary care level). My doctor scheduled an appointment for me with the rheumatologist at CEMAR (a specialised care centre in Rosario, secondary care level)… But it's hard to get there… If you arrive late, they won't see you (…)” (woman, 46 years old, with RA for 13 years). “(…) Appointments with specialists are requested well in advance, patients get lost in the process, and there is a high rate of no-shows (…)” (Administrative worker at the primary care centre in Rosario, 10 years working in the health system).
In contrast, in the city of PRSP, when a referral to a specialist at the hospital is necessary, the patient must schedule their own appointment by going to the hospital in person to request it. “(…) It’s very difficult to get appointments with specialists at the hospital…people go in person, sometimes they spend the night there just to get an appointment (…)” (Nurse at the primary care centre, Barrio Nalá, PRSP). “(…) We don’t manage hospital appointments; I suggest patients go and be patient (…)” (Director of the primary care centre, Barrio Nalá, PRSP).
In Rosario, as already mentioned, specialised care is found at the secondary level of care. Treatment initiated by a specialist can be continued at the primary care level, depending on its complexity. Professionals consult with each other through a recently implemented unified electronic health record system. Access to medication is free; however, high-cost medications require a specific procedure for access. Specialised medications are available at health centres and can be dispensed to patients after evaluation by a specialist and with their specific prescription. “For some years now, after much work, patients have had their medication available at the health centre. This allows for spacing out specialist appointments and facilitates continuity of care for the patient.” (Administrative worker at a primary care centre in Rosario, 10 years working in the health system). “My doctor is at the health centre; it’s very difficult for us to get to CEMAR (a specialised care centre in Rosario, secondary level). I haven’t seen a rheumatologist in a long time.” (Woman, 48 years old, with rheumatoid arthritis for 20 years
In the city of PRSP, each healthcare provider has its own medical records. There is no connection between primary care and the hospital. Patients must manage their own appointments and often even purchase their own medications. There is the role of community health workers, who are members of the community trained in health promotion and prevention and who assist patients throughout the process. The hospital also houses the Indigenous Social Assistance Service (SASOI), which was designed to act as a link between the community and the hospital. “At the hospital, doctors won’t see you without an appointment…” (woman, 50 years old, with rheumatoid arthritis for 15 years, Nalá neighbourhood, PRSP). “There are times when there are medication shortages, but generally, patients can continue their treatments. The difficult part of continuing treatment is getting the prescription for…yes, that’s where it gets complicated…” (physician at the local PRSP hospital). “(…) Patients don’t know the hospital rules, they don’t know the role of the people at SASOI… We always go our separate ways and we do a lot of work through favours, outside the formal hospital circuit (…)” (Social worker at the primary care centre, Barrio Nalá, PRSP).
In Rosario, the main barriers are: the distance between primary care centres and secondary care facilities, the lack of available appointments for some medical specialties, and the limited capacity of the transportation system to connect some areas of the city. Another important point to highlight is the constant turnover of professionals within the healthcare system, especially in primary care centres, the lack of cultural competence among professionals, and a lack of information regarding the culture of the population they serve. “Look, I really don’t know. Because they gave me four pills, but I don’t know which pill is for Chagas disease and which one is for rheumatoid arthritis. I’ve seen many doctors… The doctors at the health centre change a lot. I went to CEMAR once; it’s difficult to get there by bus…” (male, 55 years old, with rheumatoid arthritis for 18 years). “(…) No one explained the Qom culture to us; you learn by doing… The patients are different, and it’s very difficult to make them understand you (…)” (Administrative worker at the primary care centre in Rosario, 10 years working in the health system).
In the city of PRSP, the main barriers we identified are shared by the community in Rosario, but there are additional ones related to the community’s limited language skills when navigating the health system and the bureaucratic nature of the system, which makes it exclusionary for this community, despite having tools like SASOI. “(…) The reality is that they always say that when they are from Indigenous communities, they are not treated, they are treated poorly, they are not understood; it’s a reality, it happens (…)” (Social worker at the primary care centre, Barrio Nalá, PRSP). “When I go to the hospital, it’s difficult to get an appointment, and sometimes they don’t want to see us because sometimes they get along well with our race, and sometimes they don’t.” (Man, 48 years old, with rheumatoid arthritis for 8 years, Barrio Nalá, PRSP). “To get an appointment at the hospital, the person absolutely has to go to the Statistics office to make the appointment in person, so that is a barrier, because they might not have a way of getting here, it’s too far to walk.” (Social worker at the primary care centre, Barrio Nalá, PRSP). “(…) You have to know how to talk to the patient, especially if they are elderly, as it's difficult to convince them, to talk to them, especially in the Qom language, because the nurse and the doctor can't speak it. But we are there as intermediaries, so to speak, to be able to access and talk to that family, many of whom don't speak Spanish because they don't understand it (…)” (man, 60 years old, 15 years working as a community health worker, Nalá neighbourhood, PRSP).
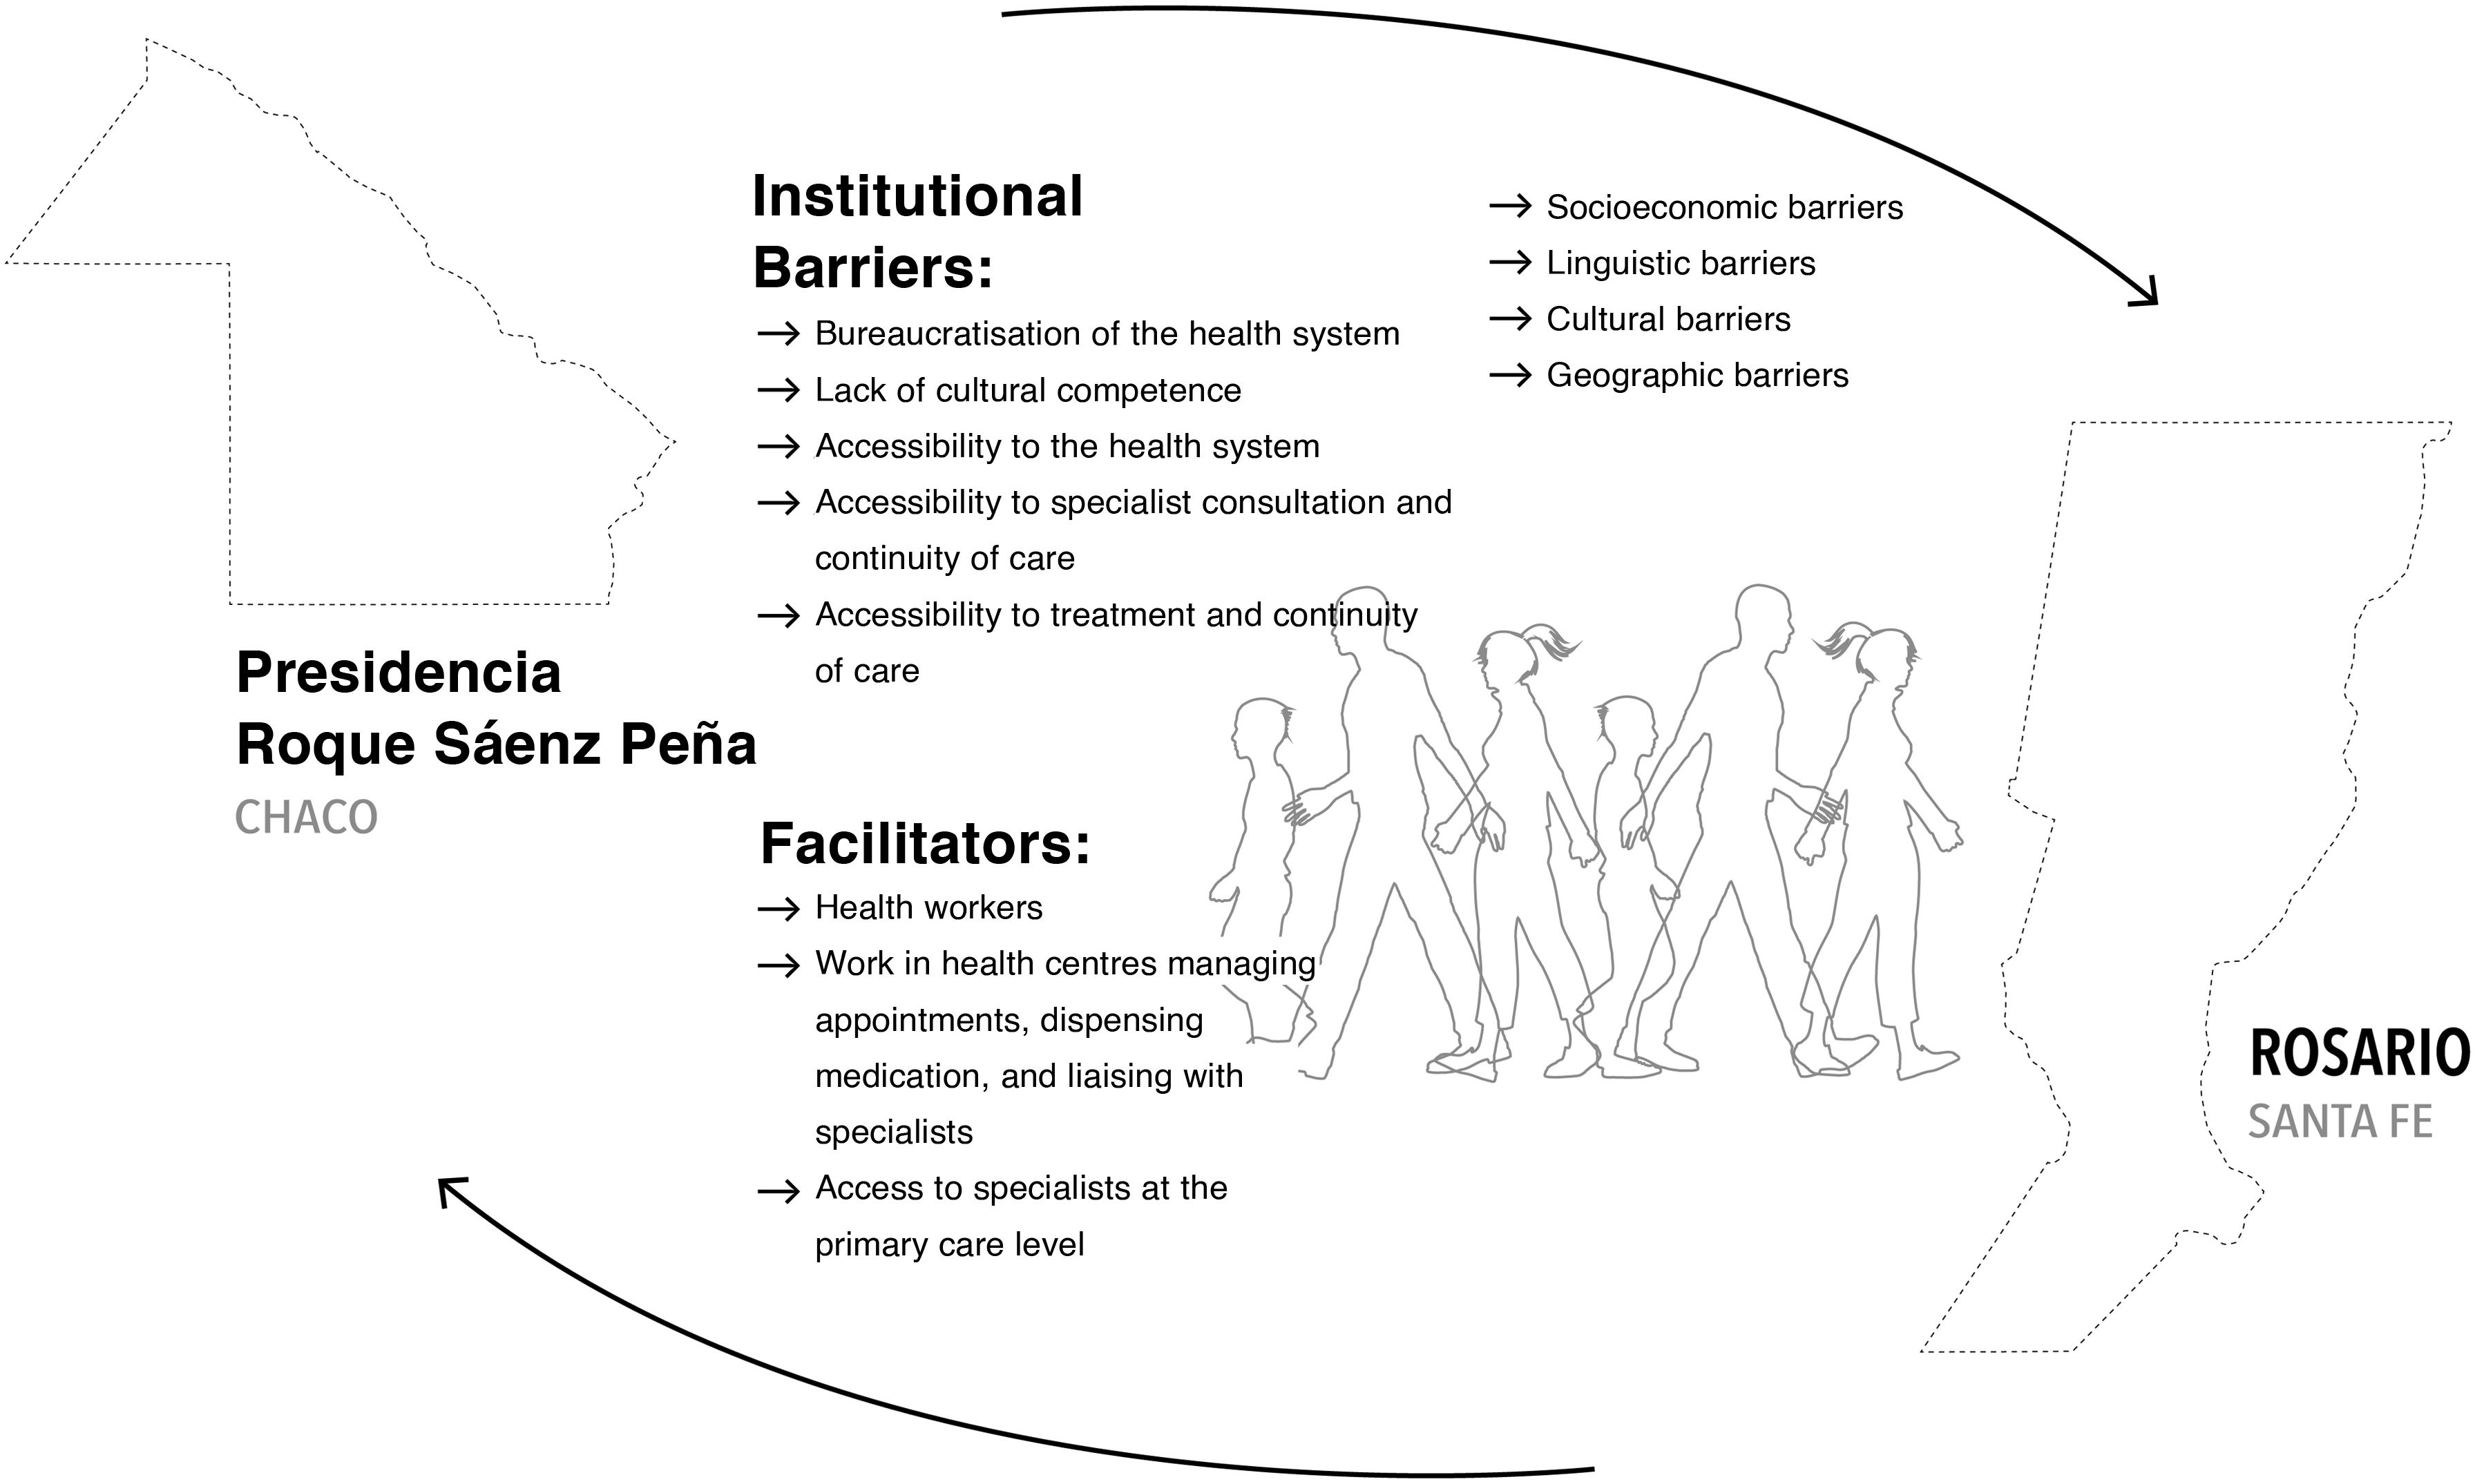
Within the framework of the qualitative analysis, a diagram (Fig. 2) was developed by the authors as an interpretive synthesis of the data obtained from the interviews and observations, based on the concept of “medical pilgrimage.” This provided a summary of the main barriers and facilitators identified, which was organised around the patient as the central focus. While the barriers were similar in both cities, in PRSP there were added barriers relating to linguistic aspects and the lack of medication dispensing at the hospital. In Rosario, on the other hand, achievements related to the incorporation of specialised consultations at the first level of care and the provision of treatments from primary care centres were highlighted.
Discussion
This study describes the complexities of access to the healthcare system faced by rheumatoid arthritis (RA) patients residing in Rosario and in PRSP. The mixed-method approach (quantitative and qualitative) presents the reality from two distinct but complementary perspectives.
The main differences between the individuals from PRSP and those from Rosario are the older age of the former group, perhaps associated with a higher frequency of osteoarthritis.4 Another point to highlight is that they had better pain tolerance and less functional limitation than those living in Rosario. This could be due to the stressful situations experienced by migrants in more urban contexts and perhaps associated with the higher proportion centred on patients in Rosario working physically demanding jobs.4,10,11 RA had the same prevalence in both locations. None of the identified patients had travelled to Rosario seeking treatment for their RA, and few patients were currently receiving adequate treatment.
The challenges in healthcare access for the Qom population in both Rosario and PRSP are consistent with findings from other studies of Indigenous populations in other parts of Latin America,24,25 as well as in other regions outside of Latin America.26,27
Regarding the healthcare system, some of the most relevant aspects to highlight are: the fragmentation between primary and specialised care; limited access to treatments recommended in therapeutic guidelines; ethnic discrimination; language barriers; and the fragility of the social support network, which restricts the possibility of adequate follow-up and care.
These findings can be understood through the concept of “health pilgrimage,” defined as the extensive, non-linear, and often uncertain journey that patients undertake to obtain care. This pilgrimage is not only physical but also institutional, within a healthcare system that is not always accessible.28,29 The patient journey can be used as a methodological tool to identify delays in care, compare experiences among patient groups, evaluate the quality of care, and ultimately, improve health systems. It places the individual at the centre, seeking to understand and improve both the patient experience and the systems they navigate.18,28,29 This concept has been developed to describe how patients “traverse” multiple institutions, spaces, actors, and obstacles before achieving, in the best-case scenario, an appropriate diagnosis and sustained access to treatment.18,8,29 Unlike linear access, these trajectories are marked by discontinuities, rejections, transfers, bureaucratic requirements, and language barriers, among other factors. Previous experiences in Latin America addressing this concept exist.12
It is essential to emphasize a mixed-method approach, allowing for triangulation of information to detect consistencies and contradictions the data show and what the actors report. This methodology is valuable in contexts of inequality.30
To conclude, the comparison developed in this research between Rosario and PRSP is essential because it allows for a contrast between two distinct socio-health realities: one urban and more centralised (Rosario) and the other peripheral with a strong indigenous component (PRSP). The analysis reveals both common factors and specific differences in access to and delivery of care. Furthermore, the use of a mixed-method approach and the concept of “health pilgrimage” provides a robust analytical framework for understanding how patients' trajectories are conditioned by structural inequalities. Finally, this study generates valuable evidence for the design of more inclusive and culturally sensitive health policies in Latin America and contributes to the scientific output that GLADERPO has been developing since its inception, strengthening the regional understanding of barriers and facilitators to health access for vulnerable populations.10,23,31
Among the strengths of this study is its mixed-method design, which integrates quantitative and qualitative data and enables triangulation of information to compare perceptions and results. This methodological approach provides a broader and deeper understanding of the problem, highlighting that, despite differences between provinces, common obstacles persist, such as the centralisation of the health system, lack of information, language barriers, and limited cultural competence. At the same time, the analysis identified positive experiences, among which the role of Qom health workers in PRSP (Public Health Rehabilitation Programme), the importance of community networks, and the implementation of local policies that have contributed to improved care, particularly in Rosario, stand out.
Among the limitations of this study are, firstly, the high proportion of people who chose not to participate in PRSP, which may have affected the representativeness of the results. Secondly, the lack of a detailed clinical identification of RA patients in PRSP hinders direct comparison with the data collected in Rosario. Furthermore, the qualitative nature of the study, while providing a wealth of interpretive insights, limits the possibility of generalising the findings to the entire Qom population. Finally, institutional variability should be noted, as differences in the organisation of provincial health systems could affect comparability between the studied contexts.
ConclusionsThis study describes the various barriers that RA patients in both provinces face in accessing the health system and maintaining their treatments. It reinforces the need to adopt intercultural care models that not only integrate medical and community knowledge but also guarantee continuity, accessibility, and respect for the rights of Indigenous communities. In turn, public policies sensitive to the mobility trajectories of these populations are needed, as they are often forced to migrate or relocate in search of care and a better future for themselves and their families, thus exacerbating their vulnerability.
FundingThe authors declare that they received no funding for this work.
The authors have no conflict of interests to declare.
Florencio Diaz (member of the Qom community and leader); Registered Nurse Cecilia González, Fabiana González, Ana Ojeda, César Canteros; Dr. Gabriela Saccani; Social Worker Analia Martinez. To the health workers: Francisca Romero, Dario Notagay, Griselda Notagay, Laura Gomez, Daniel Jara, Lisandra Romero, Rolando/Ricardo Chara, Ángela Saravia, Juan Gómez, and Anselmo Domingo. Members of SASOI: Francisco Honeri and Uriel Femenías. To the Nala Health Centre, the June 4th Hospital "Dr. Ramón Carrillo" in the city of PRSP, students and faculty of the Medical School at the National University of Chaco Austral, and the general community of both cities. To Leonardo Grasso for the design and illustration of the figures, and to Karen Roberts for the data analysis.
Barberis Axel, Rios Yamila, Bobadilla Gillard Ruth, Riedmaier Ileana, Cisneros Rodriguez Angeles, Aguada Nahuel, Parras Aldana, Noelia Virasoro, Rodriguez Sergio, Alejandro Garcia, Belen Diaz, Flores M. del Rosario, Araujo Aldan y Francovich Liza.
The following is Supplementary data to this article:





