



Rheumatoid arthritis is associated with an increased risk of chronic kidney disease, which complicates the safe use of disease-modifying antirheumatic drugs (DMARDs), particularly in patients with severe renal impairment. Our aim was to describe treatment patterns and clinical outcomes in this population.
MethodsDescriptive study of a cohort of RA patients with an estimated glomerular filtration rate (eGFR) <30 ml/min/1.73 m2, managed in a comprehensive care program between 2022 to 2024. Clinical, therapeutic, and safety data were collected.
ResultsA total of 38 patients were identified, most of whom were elderly women with a high burden of comorbidities. Leflunomide was the most frequently used conventional synthetic DMARD. Biologic therapy was used in 42% of cases, with rituximab being the most commonly prescribed agent. Most patients achieved remission or low disease activity, with no serious adverse events reported.
ConclusionsThese findings provide real-world evidence on the effectiveness and safety of DMARDs in a population often excluded from clinical trials, underscoring the need for prospective studies to inform long-term therapeutic decisions.
La artritis reumatoide se asocia con un mayor riesgo de enfermedad renal crónica, lo que dificulta el uso seguro de DMARDs, especialmente en pacientes con deterioro grave de la función renal. Nuestro objetivo es describir el tratamiento y desenlaces clínicos en esta población.
MétodosEstudio descriptivo de una cohorte de pacientes con AR y tasa de filtración glomerular estimada (TFGe) <30 ml/min/1,73 m2, atendidos entre 2022 y 2024 en un programa de atención integral. Se recopilaron datos clínicos, terapéuticos y de seguridad.
ResultadosSe identificaron 38 pacientes, la mayoría eran mujeres de edad avanzada con alta carga de comorbilidades. La leflunomida fue el DMARD sintético más utilizado. El 42% recibió terapia biológica, siendo rituximab el más prescrito. La mayoría alcanzó remisión o baja actividad de la enfermedad, sin eventos adversos graves registrados.
ConclusionesEstos hallazgos aportan evidencia de vida real sobre la efectividad y seguridad de los DMARDs en un escenario poco estudiado, resaltando la necesidad de estudios prospectivos para guiar decisiones terapéuticas a largo plazo.
Patients with rheumatoid arthritis (RA) are at increased risk of developing chronic kidney disease (CKD).1 Factors such as systemic inflammation, disease activity, endothelial dysfunction, the presence of comorbidities, and chronic use of non-steroidal anti-inflammatory drugs can all contribute to the deterioration of glomerular function and the development of CKD.2 This deterioration limits the use of disease-modifying antirheumatic drugs (DMARDs), particularly those requiring renal clearance, which makes treatment challenging in this scenario.
Patients with RA and CKD and a severely reduced glomerular filtration rate are often excluded from clinical trials due to the increased potential risk of adverse events. Consequently, there is limited information regarding the effectiveness and safety of DMARDs in this context, emphasising the necessity of generating real-world evidence concerning their use and outcomes in this population.1 Greater scientific evidence would enable therapeutic interventions and the risk/benefit profile of DMARDs to be optimised, minimising the impact of possible complications. The objective of this study is to describe the treatment and clinical outcomes of patients with severely reduced estimated glomerular filtration rate (eGFR) in a cohort of RA patients in Colombia.
Material and methodsThis is a descriptive cohort study, nested within a population with rheumatoid arthritis (RA), focusing on patients with impaired glomerular function. These patients were followed between November 2022 and February 2024 at Medicarte, a multicentre institution specialising in immune-mediated diseases in Colombia. They were part of a comprehensive care programme that included periodic follow-up with a rheumatologist, support from a pharmacist, and medication dispensing, among other services.
Patients over 18 years of age were included if they had been diagnosed with RA according to the ACR-EULAR criteria,3 were being treated with synthetic DMARDs, biological DMARDs, or JAK inhibitors (JAKis) for at least 3 months, and had severe glomerular function impairment, defined as an eGFR <30 ml/min/1.73 m2 for at least 3 months. GFR was estimated using the CKD-EPI equation,4 and stages 4 and 5 were defined according to the KDIGO guidelines.5
Disease activity was assessed using DAS28-PCR, with the following cut-off points defined: remission (<2.6); low activity (≥2.6 and <3.2); moderate activity (≥3.2 and ≤5.1); and high activity (>5.1). The HAQ questionnaire was used to evaluate functional capacity and disability.
Clinical follow-up was performed according to disease activity: every 6 months in remission, every 3 months in low or moderate activity, and more frequently in selected cases. Quantitative variables are described using the median and interquartile range (IQR), while qualitative variables are described using frequencies and percentages. Data on adverse drug reactions, hospitalisations, and death were collected. R software version 4.4.2 (2024-10-31 ucrt) was used for the analyses. The authors adhered to the 2024 Declaration of Helsinki6 and Resolution 8430 of 1993 of the Colombian Ministry of Health.7 The research study was classified as risk-free and approved by the Medicarte Research Committee through Act No. 169 of 2025.
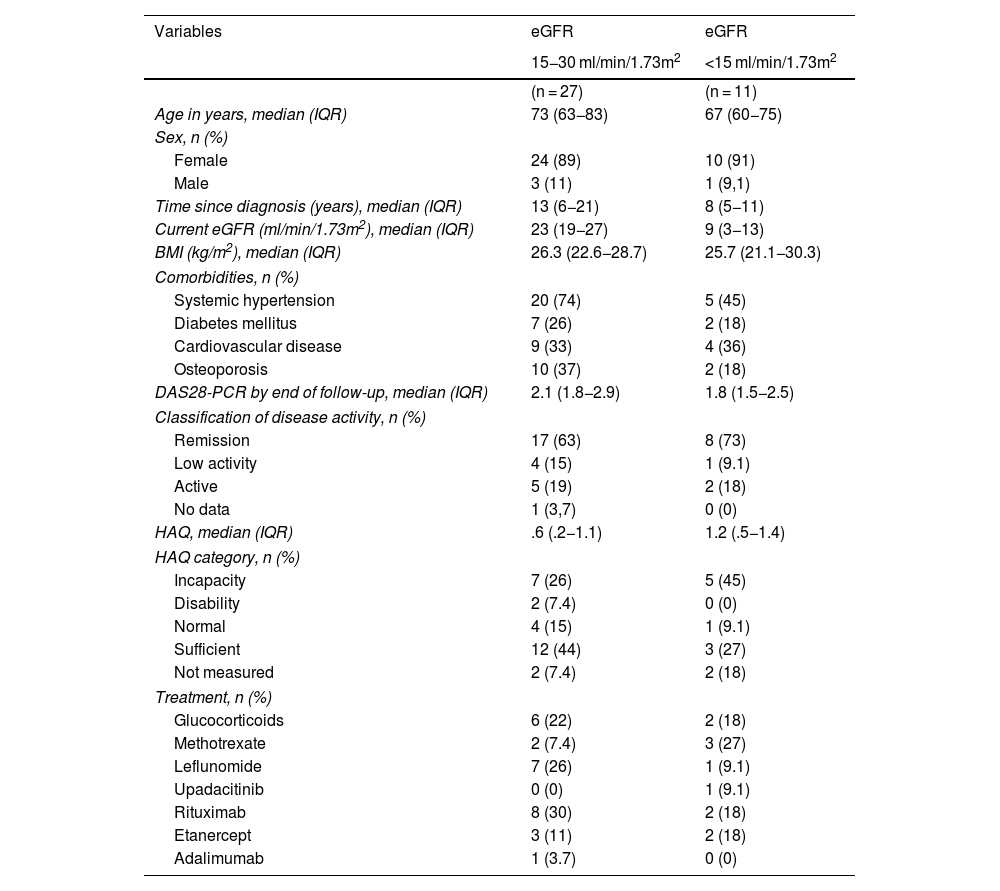
ResultsOf the 8,274 patients diagnosed with RA included in the cohort, 38 cases were identified with an eGFR <30 ml/min/1.73 m2, corresponding to a prevalence of stage 4 and 5 CKD of 4.6 per 1,000 patients with RA (see Table 1). Of these cases, 89.5% (n = 34) were female, with a median age of 70 years (IQR: 63–80 years). The age at the time of RA diagnosis was 59.2 years (IQR: 49.8–68.6) and the time since diagnosis was 10.2 years (IQR: 5.2–18.9). The median follow-up in the programme was 3.7 years (CI: 0.7–6.6), with a median of 4 annual rheumatology consultations (IQR: 3–6).
Clinical characteristics of patient with eGFR<30 ml/min/1.73m2.
| Variables | eGFR | eGFR |
|---|---|---|
| 15−30 ml/min/1.73m2 | <15 ml/min/1.73m2 | |
| (n = 27) | (n = 11) | |
| Age in years, median (IQR) | 73 (63−83) | 67 (60−75) |
| Sex, n (%) | ||
| Female | 24 (89) | 10 (91) |
| Male | 3 (11) | 1 (9,1) |
| Time since diagnosis (years), median (IQR) | 13 (6−21) | 8 (5−11) |
| Current eGFR (ml/min/1.73m2), median (IQR) | 23 (19−27) | 9 (3−13) |
| BMI (kg/m2), median (IQR) | 26.3 (22.6−28.7) | 25.7 (21.1−30.3) |
| Comorbidities, n (%) | ||
| Systemic hypertension | 20 (74) | 5 (45) |
| Diabetes mellitus | 7 (26) | 2 (18) |
| Cardiovascular disease | 9 (33) | 4 (36) |
| Osteoporosis | 10 (37) | 2 (18) |
| DAS28-PCR by end of follow-up, median (IQR) | 2.1 (1.8−2.9) | 1.8 (1.5−2.5) |
| Classification of disease activity, n (%) | ||
| Remission | 17 (63) | 8 (73) |
| Low activity | 4 (15) | 1 (9.1) |
| Active | 5 (19) | 2 (18) |
| No data | 1 (3,7) | 0 (0) |
| HAQ, median (IQR) | .6 (.2−1.1) | 1.2 (.5−1.4) |
| HAQ category, n (%) | ||
| Incapacity | 7 (26) | 5 (45) |
| Disability | 2 (7.4) | 0 (0) |
| Normal | 4 (15) | 1 (9.1) |
| Sufficient | 12 (44) | 3 (27) |
| Not measured | 2 (7.4) | 2 (18) |
| Treatment, n (%) | ||
| Glucocorticoids | 6 (22) | 2 (18) |
| Methotrexate | 2 (7.4) | 3 (27) |
| Leflunomide | 7 (26) | 1 (9.1) |
| Upadacitinib | 0 (0) | 1 (9.1) |
| Rituximab | 8 (30) | 2 (18) |
| Etanercept | 3 (11) | 2 (18) |
| Adalimumab | 1 (3.7) | 0 (0) |
With regard to comorbidities, 65.7% (n = 25) had systemic arterial hypertension, 34.2% (n = 13) had cardiovascular disease, 31.5% (n = 12) had osteoporosis, 18.4% (n= = 7) diabetes mellitus, and 7.8% (n = 3) Sjögren's syndrome. In terms of treatment, the most commonly used synthetic DMARD was leflunomide, specifically in 23.5% of cases (n = 8).
At the start of follow-up, the median serum creatinine was 1.9 mg/dl (IQR: 1.5–2.7) and the median eGFR was 24.5 ml/min/1.73 m2 (IQR: 18.3–29.05). At the end of the follow-up period, the median creatinine was 2.4 mg/dl (IQR: 1.9–3.1) and the median eGFR was 20.4 ml/min/1.73 m2 (IQR: 14.2–24.6). Despite the deterioration in eGFR, five patients who were actively prescribed low-dose methotrexate were identified. The medication was discontinued in all cases, and the pharmacovigilance programme was activated with follow-up by the pharmaceutical chemist.
Biological DMARDs were widely used in 42% (n = 16) of patients. Rituximab was the most frequently prescribed, in 29.4% (n = 10), followed by etanercept (13.1%, n = 5) and adalimumab (2.6%, n = 1).
By the end of follow-up, most patients were in remission with low disease activity, with a median DAS28-CRP of 2.1 (IQR: 1.6–2.9).
During the observation period, a single non-serious adverse event (fever) was recorded following rituximab infusion. No adverse reactions related to the use of other medications were documented. Similarly, there were no deaths, emergency department visits, hospitalisations or joint replacement procedures during follow-up.
DiscussionThis study describes the clinical characteristics, comorbidities, treatments, and outcomes of a cohort of patients with rheumatoid arthritis (RA) and chronic kidney disease (CKD) with moderate to severe glomerular function impairment, a scenario which is often excluded from clinical trials.
Most patients were elderly women with a long disease history and a high prevalence of comorbidities, particularly systemic hypertension and cardiovascular disease. During follow-up, the majority achieved therapeutic goals of remission or low disease activity, with no serious adverse events recorded.
In our cohort, leflunomide was the most commonly used synthetic DMARD, establishing itself as an effective and safe treatment option. Its active metabolite, teriflunomide, is not cleared by the kidneys, making it suitable for patients with deteriorating glomerular function. The available literature reports cases of leflunomide use in patients with an eGFR < 30 ml/min/1.73 m2, including those requiring renal replacement therapy. This demonstrates the drug's effectiveness without a significant increase in adverse effects.8,9 On the other hand, methotrexate use is limited in this population due to the increased risk of toxicity.10 However, our cohort included cases of active methotrexate prescription, possibly due to eGFR impairment after the initial rheumatology consultation. This finding highlights the importance of systematic pharmacovigilance and periodic monitoring of renal function in patients with RA. It also emphasises the need for timely interventions, such as dose adjustment or discontinuation of DMARDs, in cases of deterioration.
Biological DMARDs were commonly used in our cohort, with nearly half of patients receiving one of these therapies. This proportion exceeds that reported in the Colombian national cohort, which includes patients with both early- and late-stage RA,11 and could be explained by the pharmacokinetic advantage offered by biological DMARDs. As they do not require renal metabolism, they are a therapeutic option in cases of severe GFR decline. In our cohort, rituximab was the most frequently used, followed by etanercept and adalimumab. This differs from the pattern reported in other international cohorts, where tumour necrosis factor inhibitors predominate, followed by tocilizumab and abatacept.12 One possible explanation for the widespread use of rituximab in our setting is its favourable risk/benefit profile and its spaced administration regimen, which promotes greater adherence in our population.
Although no cases of tocilizumab use were documented in our cohort, real-world studies have reported its effectiveness and safety in this context, with a higher retention rate than tumour necrosis factor inhibitors and JAKis.12,13
With regard to JAKis, one patient undergoing treatment with upadacitinib was identified. Unlike other JAKis, such as tofacitinib14 and baricitinib,15 which are partially eliminated by the kidneys and require a dose adjustment in cases of severe eGFR impairment, the serum levels of upadacitinib remain stable in the event of a moderate to severe decline in eGFR. This positions upadacitinib as a potential therapeutic alternative in this clinical context. However, a lower JAKi retention rate has been reported in patients with eGFR <30 ml/min/1.73 m2, compared to tumour necrosis factor inhibitors, interleukin-6 receptor antagonists and co-stimulation inhibitors. This is a key aspect that must be carefully considered when making the most appropriate therapeutic decision in this population.13
This study has limitations. The small sample size and descriptive design limit the extrapolation of the findings. The retrospective nature of the study prevents the reduction of various biases. In addition, adverse events may be underestimated as they depend on clinical reporting and are subject to recall bias.
ConclusionTreating RA in patients with CKD poses a clinical challenge. Despite the limited therapeutic options available and the lack of information, our findings show that patients with RA and moderate to severe renal impairment can achieve adequate disease activity control without an increase in adverse events. However, there is a lack of data on the use of DMARDs in this population, and therefore prospective studies are needed to compare different therapeutic strategies and evaluate longer-term outcomes in terms of effectiveness and safety.
Protection of people and animalsThe authors declare that no experiments on humans or animals were conducted for this research study.
FundingThis research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
The authors have no conflict of interests to declare.
The authors would like to thank Natalia Duque Zapata for reviewing the document and for her valuable comments, which contributed significantly to its improvement.




